Related Experiment Video
Updated: Jul 7, 2026
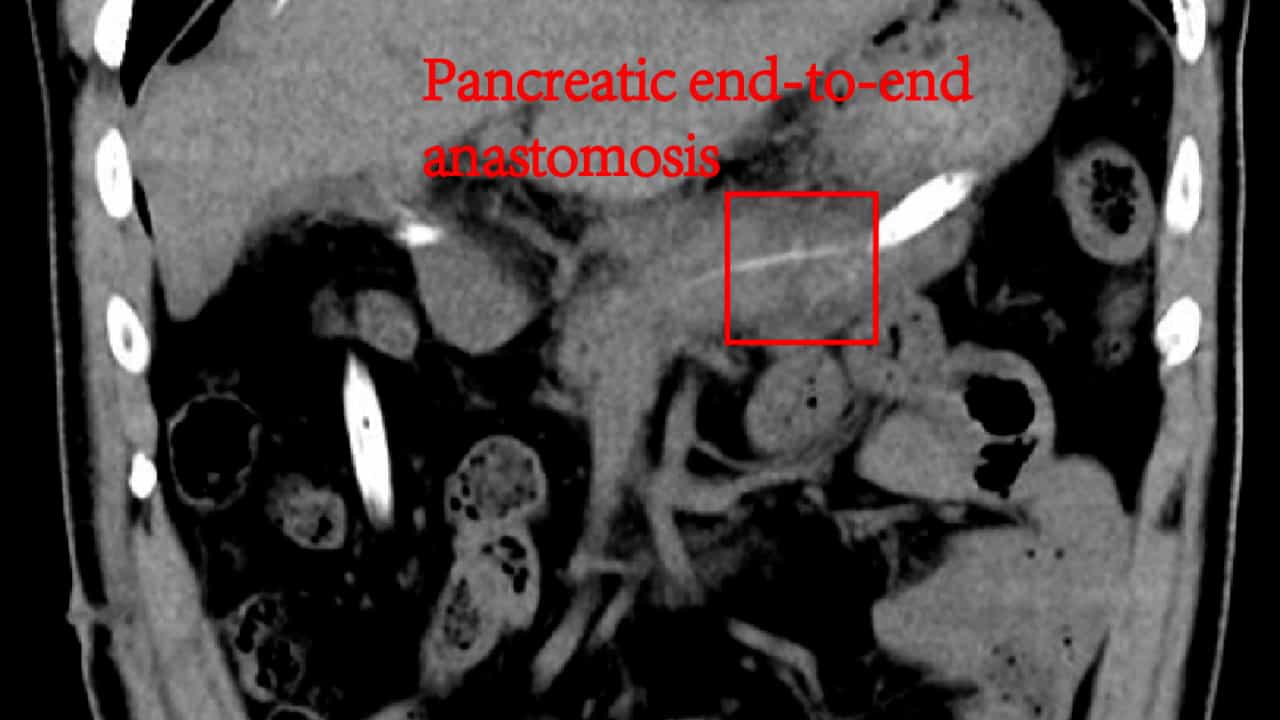

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Exocrine pancreas disfunction in severely traumatised patients and early enteral nutrition
Metin Senkal1, Bülent Ceylan, Thomas Deska
1Department of General Surgery, Marien Hospital Witten, Germany. m.senkal@t-online.de

Insights
Severely traumatized patients can experience initial exocrine pancreatic insufficiency. Early enteral nutrition with polymeric diets may improve pancreatic function in critically ill patients.
Area of Science:
- Critical care medicine
- Gastroenterology
- Trauma surgery
Background:
- Exocrine pancreatic insufficiency (EPI) is a concern in critically ill patients.
- Enteral nutrition is crucial for trauma patients but can impact pancreatic function.
- Fecal elastase-1 concentration is a marker for exocrine pancreatic function.
Purpose of the Study:
- To investigate the incidence and progression of exocrine pancreatic insufficiency in severely traumatized patients receiving early enteral nutrition.
- To assess the impact of early enteral nutrition on fecal elastase-1 levels in critically ill trauma patients.
Main Methods:
- Prospective study of 18 critically ill trauma patients.
- Fecal elastase-1 levels measured using ELISA in stool samples from the first and second bowel movements after initiating enteral nutrition.
- Early enteral nutrition initiated 24-36 hours post-admission with a high-molecular-weight diet via naso-duodenal tube.
Main Results:
- No significant feeding-associated complications or diarrhea were observed.
- 55.6% of patients showed decreased fecal elastase-1 levels in the initial stool sample, indicating pancreatic dysfunction.
- Fecal elastase-1 levels improved by the second stool passage, with only 38.9% of patients showing decreased concentrations (p<0.01).
Conclusions:
- Initial exocrine pancreatic insufficiency is suggested in severely traumatized and critically ill patients.
- Early enteral nutrition with polymeric diets appears to improve pancreatic function in this patient group.
- Further research is needed to define the clinical implications of early post-traumatic exocrine pancreatic dysfunction.
Background:
We investigated exocrine pancreatic insufficiency in severely traumatised patients with enteral nutrition using the fecal elastase-1 concentration.
Methods:
The fecal elastase-1 levels of critically ill patients after major trauma (n=18) were determined in a prospective study. Early enteral nutrition was started with a high molecular diet via a naso-duodenal tube, starting 24-36 hours after admission to the intensive care unit. Enteral feeding was administered continuously starting with 20 mL/h (1 kcal/mL) and advanced gradually to 80 mL/h in the next days. Stool samples from the first and second stool after beginning of the enteral nutrition were taken for determination of the fecal elastase-1. For elastase-1 analysis in a sandwich-type enzyme immunoassay (ELISA), a sample of approximately 1 g stool was taken from the first and second stool after beginning of the enteral nutrition. Elastase-1 concentration of >200 microg/g was considered as normal, whereas <100 microg/g elastase-1 was significantly low indicating a severe exocrine pancreas dysfunction.
Results:
All patients were fed enterally without relevant feeding-associated complications and no diarrhoea occurred in any patient. In the initial stool passage, 55.6% of the patients had moderately or severely decreased elastase-1 concentrations. In the second stool passage, only 38.9% of the patients showed a decrease in the elastase-1 concentration (p<0.01). The average elastase-concentration in the first stool sample was 268.4 microg/g (median: 162.1 microg/g) and in the second sample 333.8 microg/g (median: 520.2 microg/g).
Conclusion:
The data of this study suggests that initial exocrine pancreas insufficiency may occur in severely traumatised and critically ill patients, which improves under early enteral nutrition with polymeric enteral diets. The clinical consequences of exocrine pancreatic dysfunction in the early posttraumatic situation have to be defined.
Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Chronic Pancreatitis I: Introduction