Related Experiment Video
Updated: Jul 7, 2026


Demonstrating a Linear Relationship Between Vascular Endothelial Growth Factor and Luteinizing Hormone in Kidney Cortex Extracts
Published on: January 22, 2020
Luteinizing hormone and follicle-stimulating hormone levels in extreme prematurity: development of reference
Ronda F Greaves1, Rodney W Hunt, Angela S Chiriano
1Royal Children's Hospital, Complex Biochemistry Department, Parkville, Victoria 3052, Australia. ronda.greaves@rch.org.au

Insights
This study establishes new reference intervals for luteinizing hormone (LH) and follicle-stimulating hormone (FSH) in extremely premature infants. These findings aid in the accurate interpretation of early infant hormone levels, crucial for clinical decisions.
Area of Science:
- Pediatric Endocrinology
- Neonatal Physiology
- Reproductive Hormones
Background:
- Pediatric reference intervals for hormones are challenging to establish and often outdated.
- Accurate interpretation of gonadotropins (LH and FSH) is vital for diagnosing conditions like ambiguous genitalia in neonates.
Purpose of the Study:
- To develop novel reference intervals for luteinizing hormone (LH) and follicle-stimulating hormone (FSH).
- To provide age-specific hormone ranges for infants born between 24 and 29 weeks' gestation.
Main Methods:
- Collected blood samples from 82 premature infants (born <30 weeks gestation) within the first 43 days of life.
- Analyzed luteinizing hormone (LH) and follicle-stimulating hormone (FSH) levels using automated immunochemiluminometric immunoassays.
Main Results:
- Established distinct LH and FSH ranges for male and female infants in the first 6 weeks post-birth.
- Observed significant differences in LH/FSH ratios between male (0.3–9.4) and female (<0.5) premature infants.
Conclusions:
- The study provides crucial guidance for interpreting LH and FSH levels in extremely premature neonates.
- Availability of these age-appropriate reference intervals is essential for timely and accurate clinical biochemical assessments.
Objectives:
Establishing pediatric reference intervals has always been challenging, with most ranges used in pediatric laboratories developed over many years. The clinical interpretation of gonadotropins is important in the context of ambiguous genitalia. The aim of this study was to develop reference intervals for luteinizing hormone and follicle-stimulating hormone in infants born between 24 and 29 weeks' gestation.
Methods:
Samples were collected at 0 to 43 days after birth from 82 premature infants born <30 weeks' gestation for analysis of luteinizing hormone and follicle-stimulating hormone by automated immunochemiluminometric immunoassays.
Results:
The 43 male infants demonstrated a range of luteinizing hormone levels from 0.1 to 13.4 IU/L and of follicle-stimulating hormone levels from 0.3 to 4.6 IU/L. The 39 female infants demonstrated a range of luteinizing hormone levels from 0.2 to 54.4 IU/L and of follicle-stimulating hormone levels from 1.2 to 167.0 IU/L. The ratio of luteinizing hormone/follicle-stimulating hormone levels differed with males, ranging from 0.3 to 9.4, and females, at <0.5.
Conclusion:
These data provide guidance for the interpretation of luteinizing hormone and follicle-stimulating hormone levels for the first 6 weeks of life in extremely premature infants born between 24 and 29 weeks' gestation. The availability of age-appropriate reference intervals is essential for correct and timely interpretation of biochemical results to the clinician.

Related Concept Videos
 01:27
Ovarian Cycle
 01:24
Gonadal and Placental Hormones
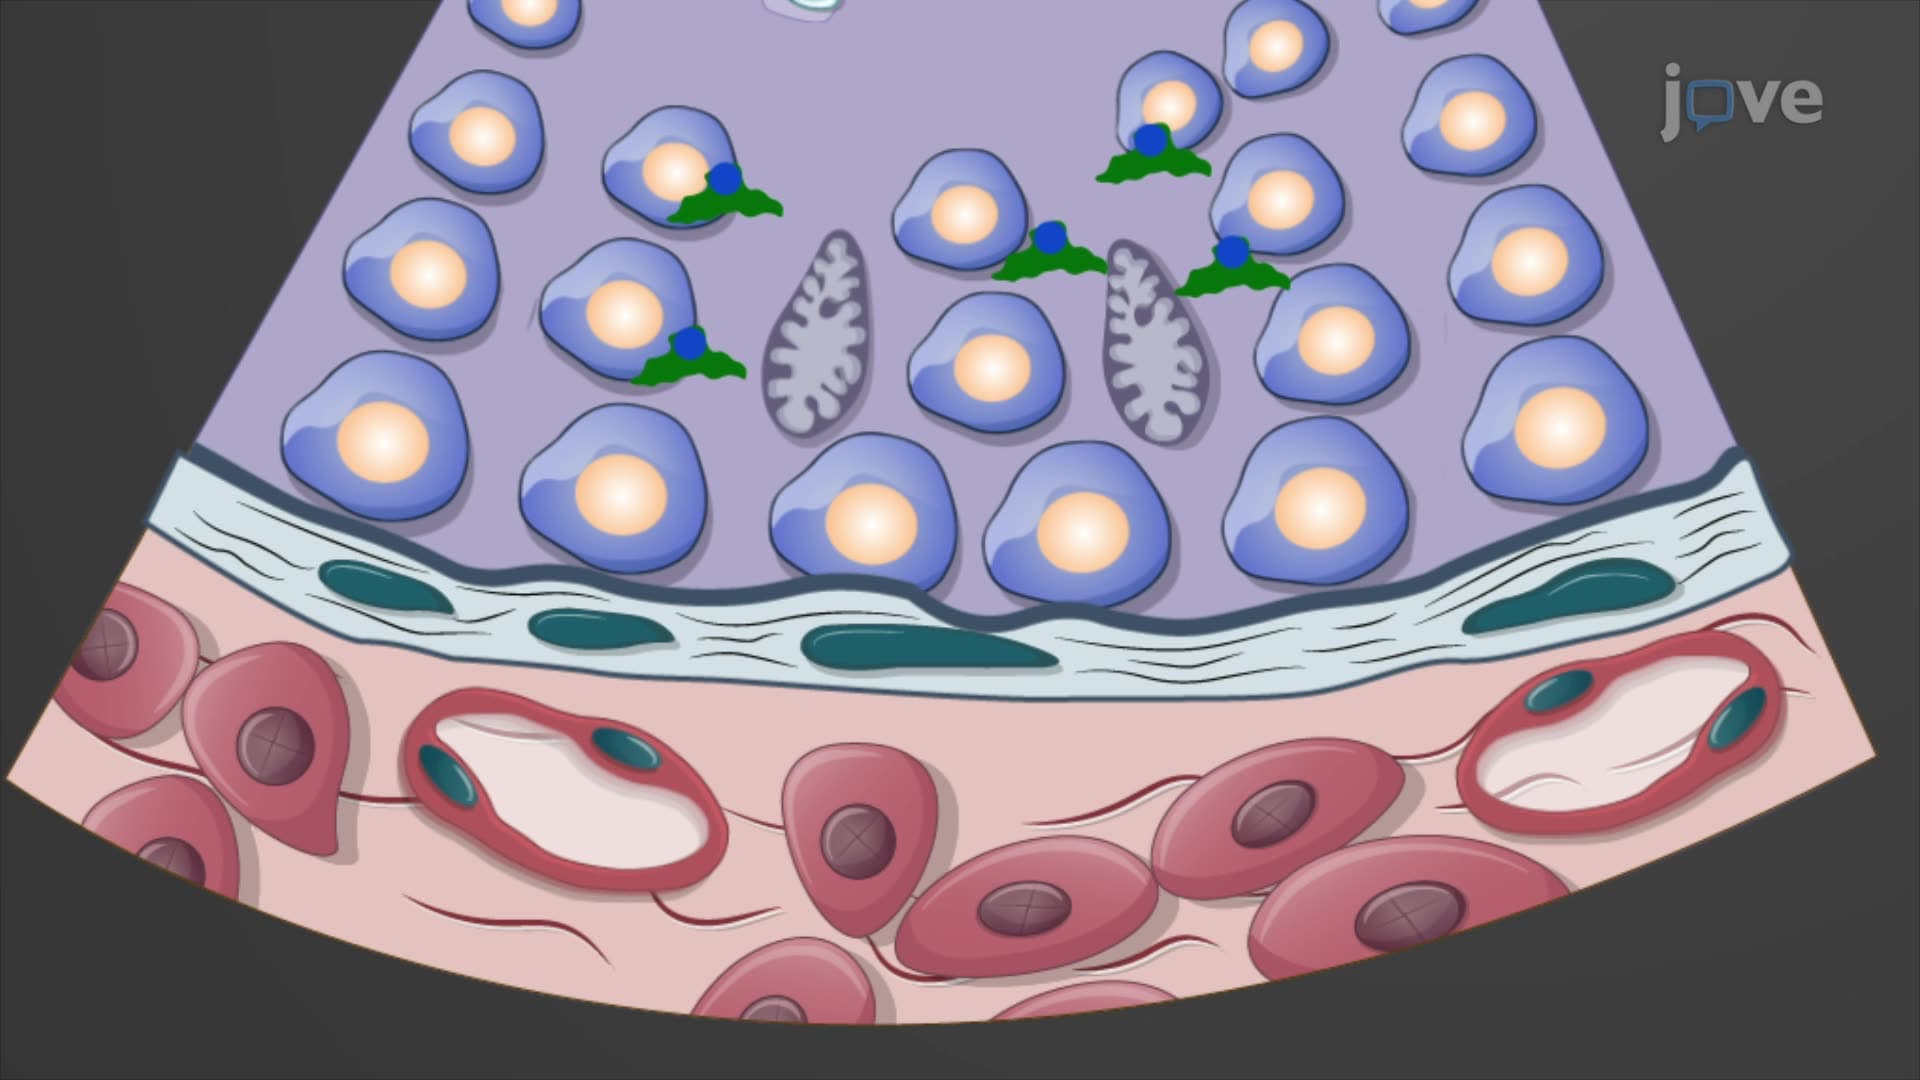
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:26
Testosterone: Functions and Regulation
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...