Related Experiment Video
Updated: Jul 6, 2026


Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
[Monitoring airway gas in pediatric anesthesia: an experimental model for endotracheal gas measurement]
J M Calvo Vecino1, A Abad Gurumeta, C Gil Lapetra
1Servicio de Anestesiología y Reanimación, Hospital Infantil Universitario Niño Jesús, Madrid. joscalvo@ya.com

Insights
Intratracheal gas monitoring during pediatric anesthesia differs from extratracheal measurements. Endotracheal probes provide distinct values for oxygen, nitrous oxide, and sevoflurane fractions compared to external sensors.
Area of Science:
- Anesthesiology
- Respiratory Physiology
- Medical Device Technology
Background:
- Development of an endotracheal probe for precise measurement of inspired and expired gas fractions in pediatric general anesthesia.
- Addressing the need for accurate gas monitoring during mechanical ventilation in children.
Purpose of the Study:
- To compare gas fraction measurements obtained via intratracheal (endotracheal) versus extratracheal (external) monitoring.
- Evaluate the accuracy and differences between two distinct gas monitoring techniques.
Main Methods:
- Inclusion of ASA 1 pediatric patients (7-12 years) undergoing inhaled anesthesia and mechanical ventilation.
- Simultaneous recording of inspired/expired oxygen, nitric oxide (N2O), and sevoflurane fractions, alongside PaCO2 and end-tidal carbon dioxide (ETCO2), using both intratracheal and extratracheal sensors.
- Statistical analysis including t-tests, Pearson correlation, and regression models to compare measurements.
Main Results:
- Endotracheal end-tidal carbon dioxide (ETCO2) measurements were significantly higher than extratracheal, but closely correlated with PaCO2.
- Intratracheal measurements showed higher inspired/expired gradients for oxygen and N2O compared to extratracheal.
- Extratracheal measurements yielded higher sevoflurane gradients, with both gas types reaching measurement equality over time.
Conclusions:
- Intratracheal and extratracheal methods yield significantly different measurements for inspired and expired gas fractions.
- The placement of gas monitoring (intratracheal vs. extratracheal) impacts the accuracy and interpretation of anesthetic gas data.
- Further research may be needed to establish clinical relevance and optimal use of each monitoring technique.
Background:
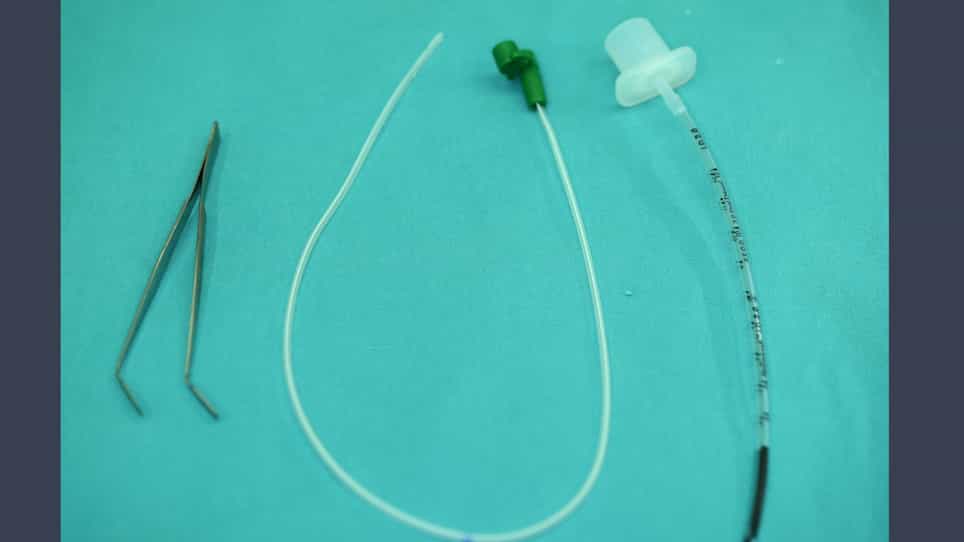
We designed an endotracheal probe for measuring inspired and expired gas fractions during pediatric general anesthesia.
Objective:
To compare the gas fractions measured by means of intratracheal and extratracheal monitoring.
Material And Methods:
The study included ASA 1 patients between the ages of 7 and 12 years under inhaled anesthesia with mechanical ventilation. The following parameters were recorded inside and outside the trachea: inspired and expired oxygen, nitric oxide (N2O) and sevoflurane fractions; the expired and inspired fraction gradients; PaCO2; and end-tidal carbon dioxide (ETCO2). Measurements were taken by an airflow sensor (Pedi-Lite) in the circuit before the point of connection to the endotracheal tube and by an intratracheal probe placed between the tube and the carina. Both sensors were connected to the same monitor. Measurements were taken on intubation and 5, 10, 15, 20, 30, 40, 50, and 60 minutes thereafter. PaCO2 was recorded at the same time. The recorded values were analyzed using the t test and the Pearson product moment correlation coefficient (r), and regression models were constructed using analysis of variance.
Results:
Seventy-one patients were enrolled in the study. The mean difference (SD) ETCO2 was 5 (3) mm Hg higher according to endotracheal measurement (P < .005), and that measurement was almost identical (+/-13 mm Hg) to the PaCO2 (P < or = .5). The inspired/expired gradients of endotracheal measurement of oxygen and N2O were 3 (2) points higher (P < .05) than the gradients of extratracheal measurements. In the case of sevoflurane gradients, however, the extratracheal values were higher (mean difference, 0.6 [0.2] points, P < .05). The inspired/expired oxygen and N2O gradients became equal after 18 (3) minutes; the sevoflurane gradients became equal after 8 (2) minutes.
Conclusions:
Intratracheal and extratracheal measurements of the inspired and expired fractions of mixed gases provide different results.