Related Experiment Video
Updated: Jul 6, 2026


Retroperitoneal Laparoscopic Debridement and Drainage for Pancreatic Abscess
Published on: March 15, 2024
HIV infection and the pancreas: risk factors and potential management guidelines
Roberto Manfredi1, Leonardo Calza
1Department of Clinical and Experimental Medicine, Division of Infectious Diseases, Alma Mater Studiorum University of Bologna, S Orsola-Malpighi Hospital, Bologna, Italy. roberto.manfredi@unibo.it

Abstract:
One thousand and eighty-one evaluable HIV-infected patients were assessed for pancreatic abnormalities in a prospective case-control study including the whole follow-up period of each patient (minimum 12 months). The 435 patients (40.2%), who experienced at least one episode of confirmed pancreatic laboratory abnormality had a longer duration of seropositivity, exposure to protease inhibitors, a more frequent immunodeficiency, AIDS, chronic liver and/or biliary disease and hypertriglyceridaemia, while no relation was found with antiretroviral administration, and the duration of type of nucleoside analogues, when compared with the 646 controls. High and prolonged laboratory alterations eventually associated with signs of organ involvement occurred in 166 cases (38.2%), and were related to the administration of didanosine, stavudine, lamivudine, pentamidine, cotrimoxazole or antitubercular/antimycobacterial therapy, cytotoxic chemotherapy, illicit substance or alcohol abuse, opportunistic infections, chronic liver and/or biliary disease, a protease inhibitor-based highly active antiretroviral therapy (HAART) and hypertriglyceridaemia (usually associated with HAART administration). No difference was noticed between the 46 patients with clinical and/or imaging evidence of pancreatic involvement and the 120 asymptomatic subjects. Although recurrences of enzyme alterations involved 69.6% of patients, only in 30.1% of cases did a change of the underlying antiretroviral or antimicrobial therapy become necessary. An acute, uncomplicated pancreatitis occurred in nine of the 46 symptomatic subjects (19.6%). A two to four week gabexate and/or octreotide administration (performed in 79 cases of 166, 47.6%), achieved a significant laboratory, clinical and imaging cure or improvement in 82.3% of cases, with a better success rate of combined (gabexate mesilate plus octreotide) vs. single (gabexate mesilate or ocreotide) therapy. Reduced disease recurrences and a better tolerability of antiretroviral regimens, were also noticed.

Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
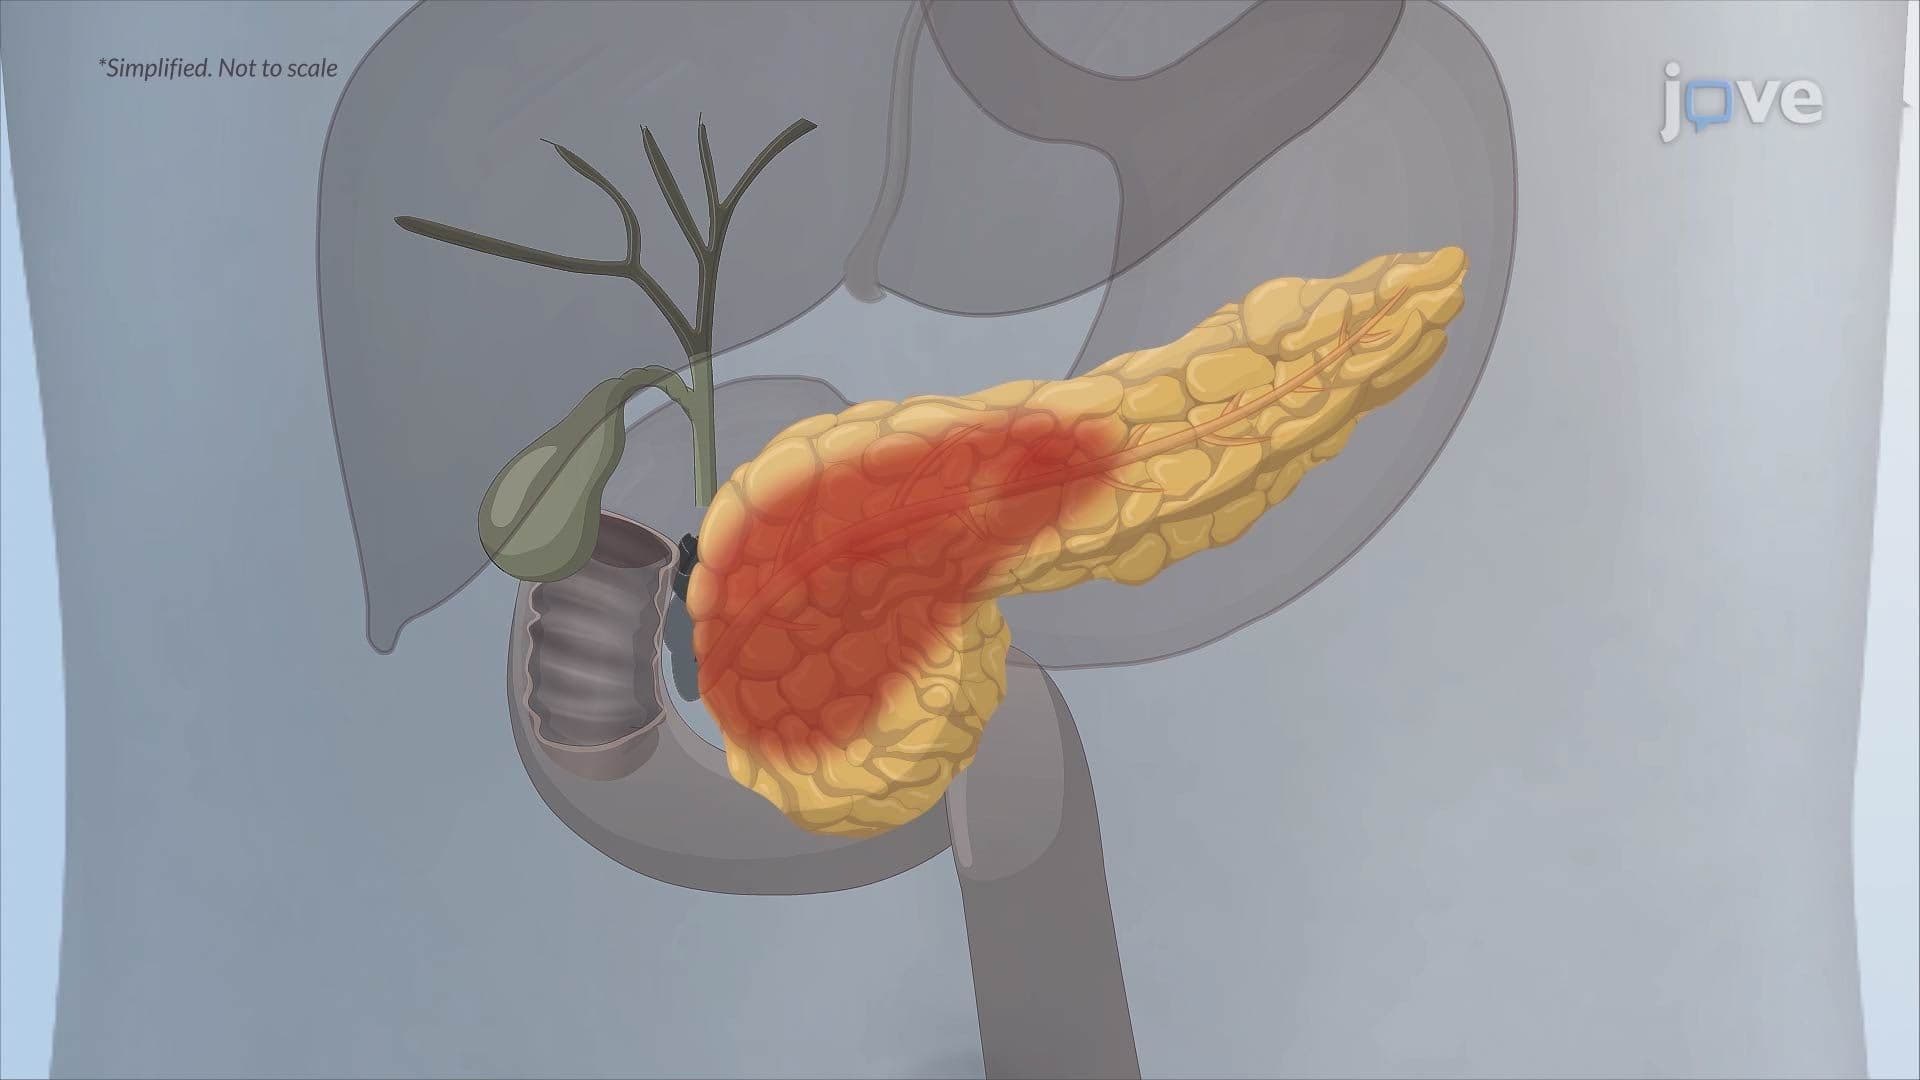
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: