Related Experiment Video
Updated: Jul 6, 2026
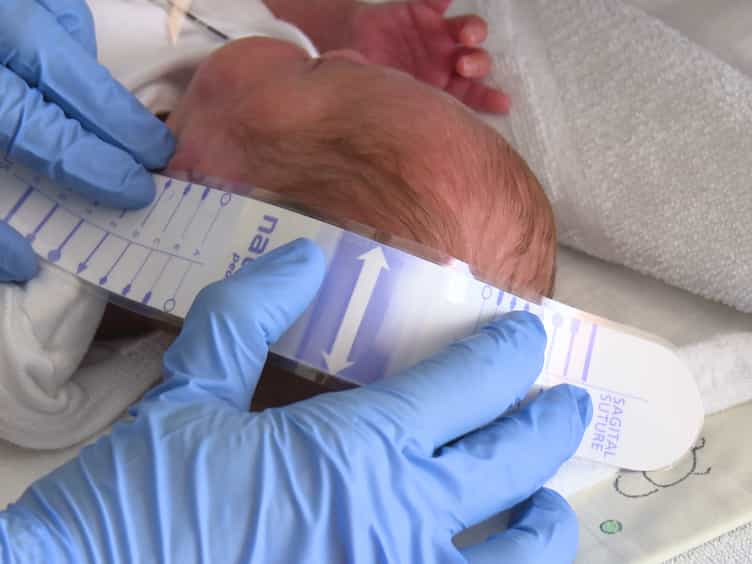
Application of an Amplitude-integrated EEG Monitor (Cerebral Function Monitor) to Neonates
Published on: September 6, 2017
Thyroid function in preterm infants 27-29 weeks of gestational age during the first four months of life: results from
María Clemente1, Pilar Ruiz-Cuevas, Antonio Carrascosa
1Pediatric Endocrine Service, Children's Hospital Vall d'Hebron, Autonomous University of Barcelona, Spain. mclement@vhebron.net

Insights
Thyroid function in very preterm neonates (27-29 weeks) is affected by prematurity and illness. Individual assessment is crucial during the first two months of life for these infants.
Area of Science:
- Neonatal endocrinology
- Perinatal medicine
- Thyroid physiology
Background:
- Thyroid function assessment is critical in preterm neonates (PTN).
- Understanding thyroid hormone dynamics in extremely preterm infants (27-29 weeks gestational age) is essential for clinical management.
- Previous studies have established thyroid function norms for later preterm infants (30-35 weeks).
Purpose of the Study:
- To assess thyroid function in preterm neonates born between 27-29 weeks of gestational age.
- To compare thyroid hormone levels between healthy and sick PTN within this gestational age range.
- To establish reference ranges for thyroid hormones in early preterm infants.
Main Methods:
- Studied 80 preterm neonates (27-29 weeks gestational age), categorized as healthy (n=17) or sick (n=63).
- Measured serum TSH, free T4, T4, T3, and rT3 in mothers, cord blood, and infants at multiple postnatal time points (1 hour to 4 months).
- Compared findings with previously evaluated healthy PTN of 30-35 weeks gestational age.
Main Results:
- TSH peaked at 1 hour and declined in both healthy and sick PTN.
- Healthy PTN showed a free T4 peak at 24 hours, absent in sick neonates.
- Sick PTN exhibited lower TSH and free T4 levels at 24 hours and 1 week compared to healthy PTN (p < 0.05).
- Healthy PTN (27-29 weeks) had lower TSH peaks and hormone levels in the first two months than PTN (30-35 weeks), but remained above -2 SD of controls.
- A significant proportion of sick PTN showed free T4 values above -2 SD of healthy PTN (30-35 weeks) controls at later time points.
Conclusions:
- Prematurity and illness significantly influence thyroid function in preterm neonates (27-29 weeks).
- Individualized thyroid function assessment is necessary for these infants, particularly during the first two months of life.
- The study highlights the variability of thyroid hormone levels in sick preterm infants.
Aim:
Assessment of thyroid function in preterm neonates (PTN) 27-29 weeks of gestational age.
Patients And Methods:
80 PTN, gestational age 27 weeks in 24, 28 weeks in 28, and 29 weeks in 28. Neonates were classified as healthy (n=17) or sick (n=63). Measurement of serum TSH, free T4, T4, T3 and rT3 in the mother and in the cord at the time of delivery, and in the infant at 1 hour, 24 hours, 1 week, 3 weeks, and 2 and 4 months of postnatal age.
Results:
In healthy and sick preterms, TSH values peaked at 1 hour and decreased thereafter. Healthy PTN presented a peak in free T4 values at 24 hours that was not observed in sick neonates. Sick PTN had a lower TSH peak and lower free T4 values at 24 hours and 1 week than healthy ones (p < 0.05). Healthy PTN 27-29 weeks had lower TSH peak at 1 hour and lower free T4, T3 and T4 values during the first 2 months than healthy PTN 30-35 weeks (PTN30-35w) previously evaluated (p < 0.05). However, at all postnatal times healthy preterms had free T4 values above -2 SD of the mean values of healthy PTN30-35w. A wide range of free T4 values was observed in the sick group. Free T4 values above -2 SD of the mean values of healthy PTN30-35w were detected in a high proportion of sick PTN (58.3% at 24 hours, 73.5% at 1 week, 93.9% at 3 weeks, 85.1% at 2 months and 100% at 4 months).
Conclusions:
Prematurity and disease influence thyroid function, and consequently thyroid function should be individually assessed in preterms 27-29 weeks of gestation during the first 2 months of life.

Related Concept Videos
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:23
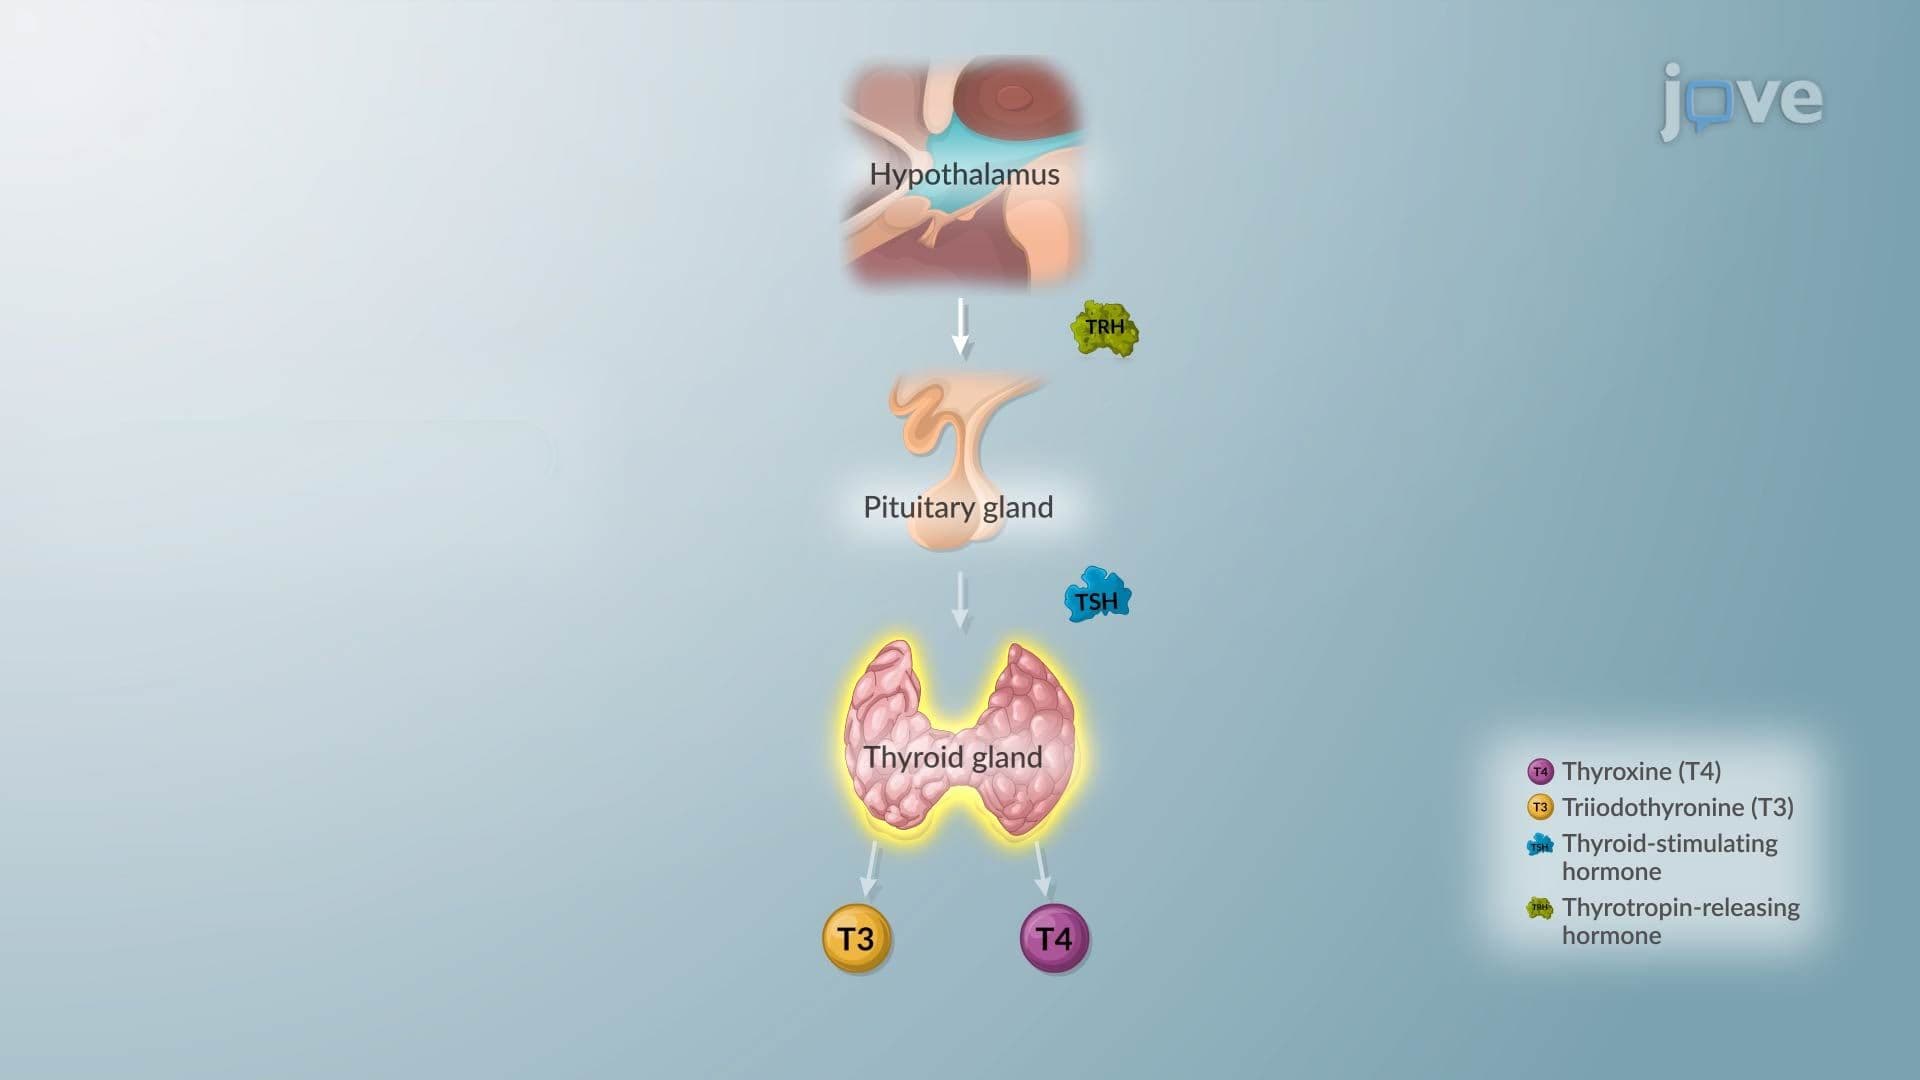
Hypothyroidism II: Pathophysiology
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:27
Hyperthyroidism II: Pathophysiology