

Electrocardiographic criteria for detecting acute myocardial infarction in patients with left bundle branch block: a
Jeffrey A Tabas1, Robert M Rodriguez, Hilary K Seligman
1Department of Medicine, Division of Emergency Services, San Francisco General Hospital, University of California-San Francisco, San Francisco, CA 94110, USA. jtabas@sfghed.ucsf.edu

Insights
The Sgarbossa ECG algorithm score of 3 or higher effectively diagnoses acute myocardial infarction in patients with left bundle branch block. A score of 2 is ineffective for diagnosis, and a score of 0 cannot exclude myocardial infarction.
Area of Science:
- Cardiology
- Electrocardiography
- Medical Diagnostics
Background:
- Left bundle branch block (LBBB) complicates the electrocardiogram (ECG) diagnosis of acute myocardial infarction (AMI).
- The Sgarbossa ECG algorithm was developed to aid in AMI diagnosis in LBBB patients.
- Previous studies on the Sgarbossa algorithm's utility have yielded conflicting results.
Purpose of the Study:
- To systematically review and meta-analyze existing trials evaluating the Sgarbossa ECG algorithm for AMI prediction in LBBB.
- To clarify the diagnostic accuracy and clinical utility of the Sgarbossa ECG algorithm.
Main Methods:
- A comprehensive literature search of MEDLINE and Scopus databases was conducted from 1996 onwards.
- Two independent reviewers screened studies, assessed methodological quality, and extracted relevant data.
- Fixed-effect models were used to calculate summary estimates for sensitivity, specificity, and likelihood ratios.
Main Results:
- Eleven studies with 2,100 patients were included.
- A Sgarbossa score ≥3 showed a sensitivity of 20% and specificity of 98% for AMI diagnosis (10 studies, 1,614 patients).
- A Sgarbossa score ≥2 demonstrated variable sensitivity (20-79%) and specificity (61-100%) with heterogeneous likelihood ratios (7 studies, 1,213 patients).
Conclusions:
- A Sgarbossa ECG algorithm score of ≥3 is a valuable tool for diagnosing AMI in LBBB patients.
- The scoring system exhibits substantial interobserver agreement.
- A Sgarbossa score of 2 is ineffective for AMI diagnosis, and a score of 0 does not rule out AMI.
Study Objective:
Numerous investigators have evaluated the ECG algorithm described by Sgarbossa et al to predict acute myocardial infarction in the presence of left bundle branch block and have arrived at divergent conclusions. To clarify the utility of the Sgarbossa ECG algorithm, we perform a systematic review and meta-analysis of these trials.
Methods:
A structured search was applied to MEDLINE and Scopus databases, beginning with the year that the algorithm was derived (1996). Two reviewers independently screened citations, assessed for method quality, and extracted data (individual study characteristics, screening performance, and interobserver agreement) with a standardized extraction tool. We assessed qualifying studies for heterogeneity and generated summary estimates for the sensitivity, specificity, and positive and negative likelihood ratios with fixed-effect models.
Results:
We identified 11 studies with 2,100 patients that met criteria for at least 1 component of the analysis. Ten studies with 1,614 patients reported a Sgarbossa ECG algorithm score of greater than or equal to 3. These yielded a summary sensitivity of 20% (95% confidence interval [CI] 18% to 23%), specificity of 98% (95% CI 97% to 99%), a positive likelihood ratio of 7.9 (95% CI 4.5 to 13.8), and a negative likelihood ratio of 0.8 (95% CI 0.8 to 0.9). The summary diagnostic odds ratio revealed homogeneity. Seven studies with 1,213 patients reported a Sgarbossa ECG algorithm score of greater than or equal to 2. These yielded sensitivities ranging from 20% to 79% and specificities ranging from 61% to 100%. Positive likelihood ratios ranged from 0.7 to 6.6 and negative likelihood ratios ranged from 0.2 to 1.1. The summary diagnostic odds ratio revealed heterogeneity. Intra- and interobserver agreement was substantial. Sensitivity analysis using the highest-quality studies yielded similar results.
Conclusion:
A Sgarbossa ECG algorithm score of greater than or equal to 3, representing greater than or equal to 1 mm of concordant ST elevation or greater than or equal to 1 mm ST depression in leads V1 to V3, is useful for diagnosing acute myocardial infarction in patients who present with left bundle branch block on ECG. The scoring system demonstrates good to excellent overall interobserver variability. A score of 2, representing 5 mm or more of discordant ST deviation, demonstrated ineffective positive likelihood ratios. A Sgarbossa ECG algorithm score of 0 is not useful in excluding acute myocardial infarction.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
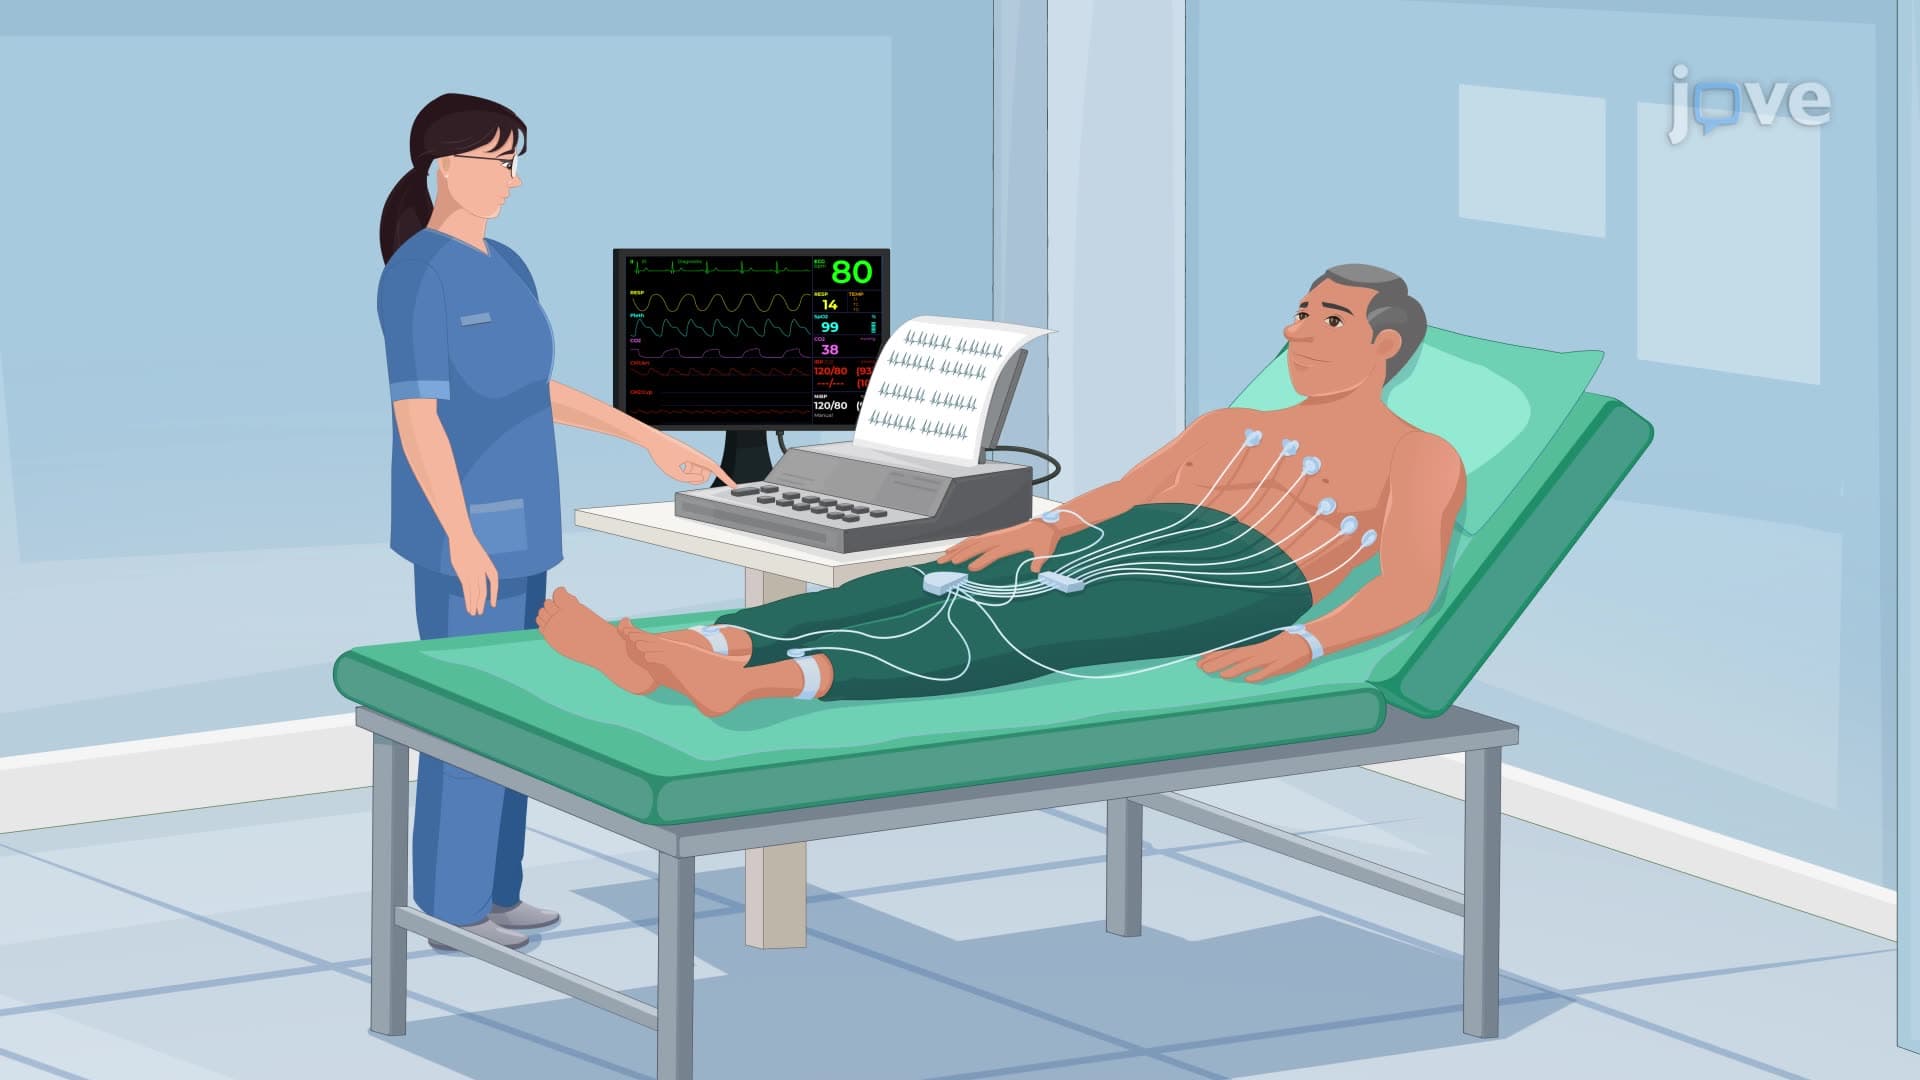
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Electrocardiogram Fundamentals
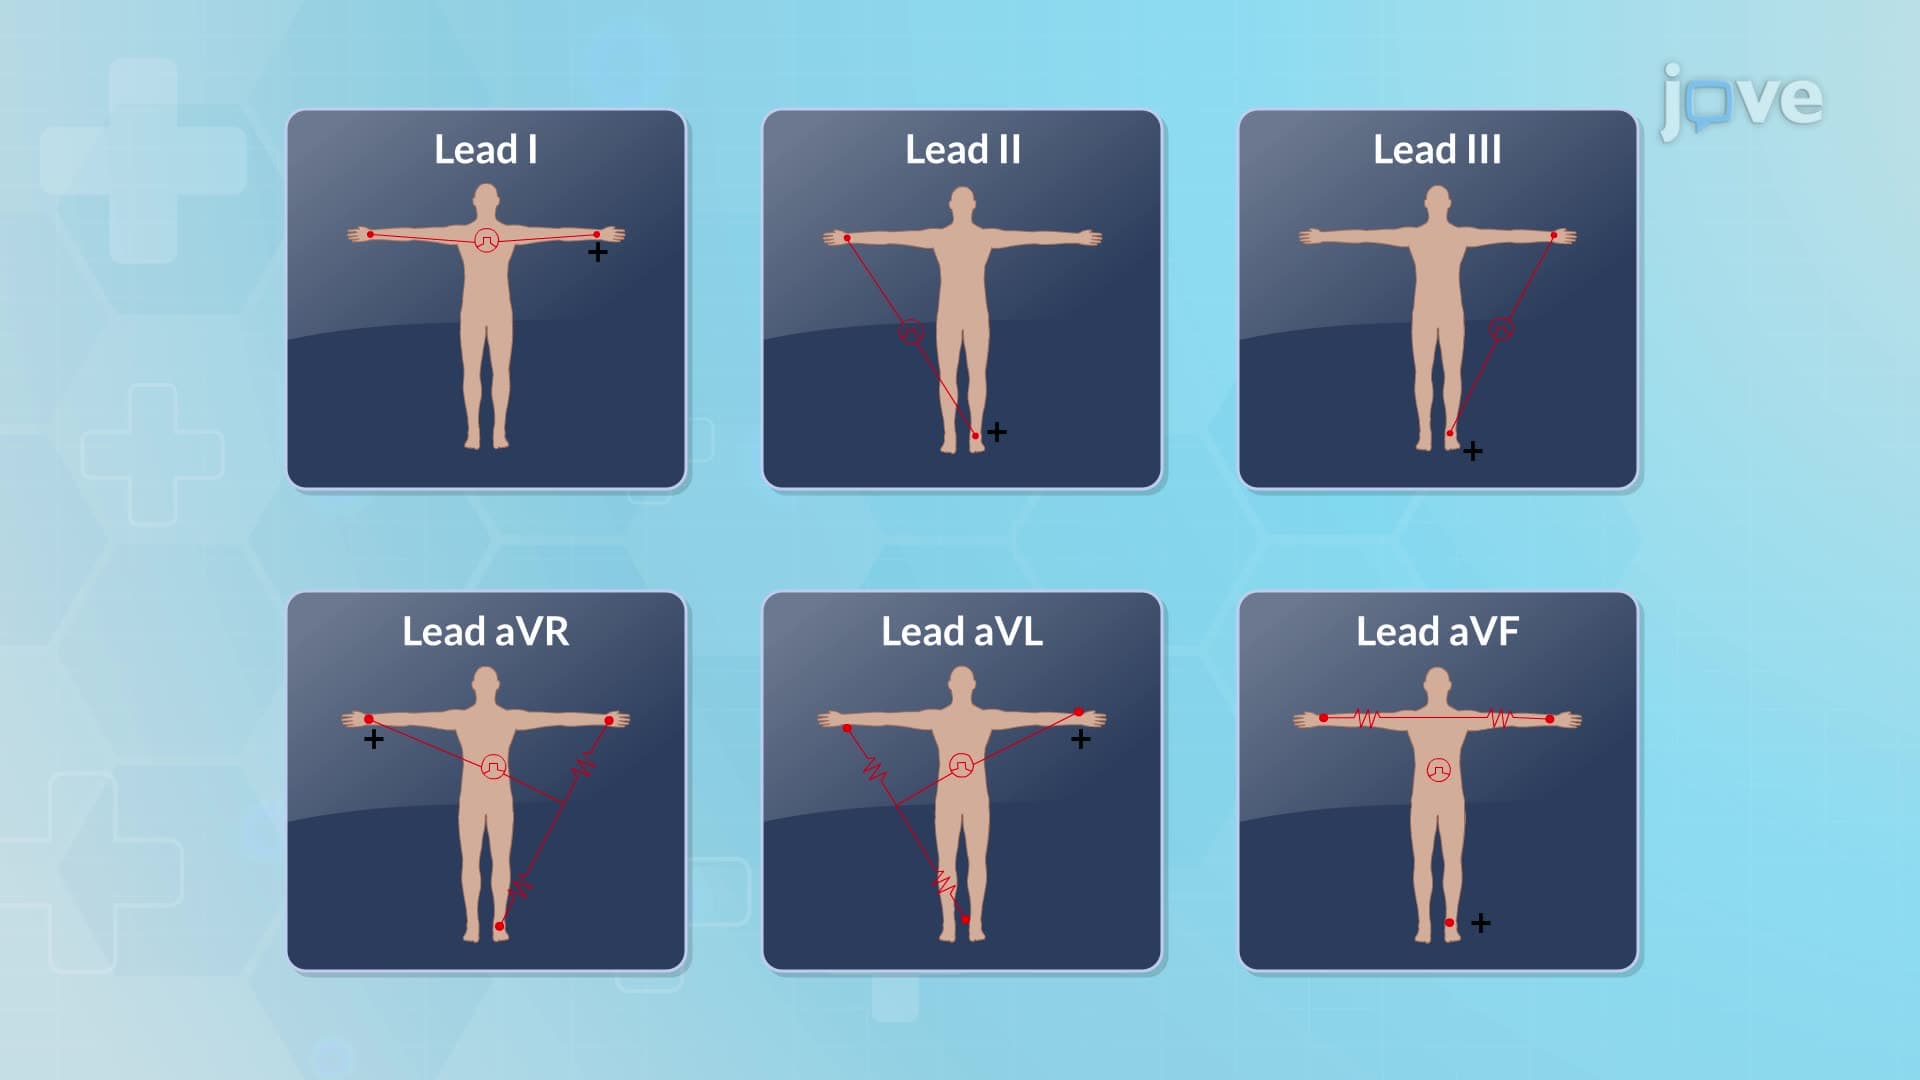
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...