A neuropathic pain component is common in acute whiplash and associated with a more complex clinical presentation

Michele Sterling1, Ashley Pedler

  • 1Centre of National Research on Disability and Rehabilitation Medicine, The University of Queensland, Mayne Medical School, Herston, QLD, Australia. m.sterling@uq.edu.au

Manual Therapy
|March 25, 2008
PubMed

Related Concept Videos

Spinal Cord Injury ll: Pathophysiology01:14

Spinal Cord Injury ll: Pathophysiology
Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...
Nociception01:44

Nociception

Nociception—the ability to feel pain—is essential for an organism’s survival and overall well-being. Noxious stimuli such as piercing pain from a sharp object, heat from an open flame, or contact with corrosive chemicals are first detected by sensory receptors, called nociceptors, located on nerve endings. Nociceptors express ion channels that convert noxious stimuli into electrical signals. When these signals reach the brain via sensory neurons, they are perceived as pain. Thus, pain helps the...
Degenerative Disc Disease ll: Pathophysiology01:23

Degenerative Disc Disease ll: Pathophysiology

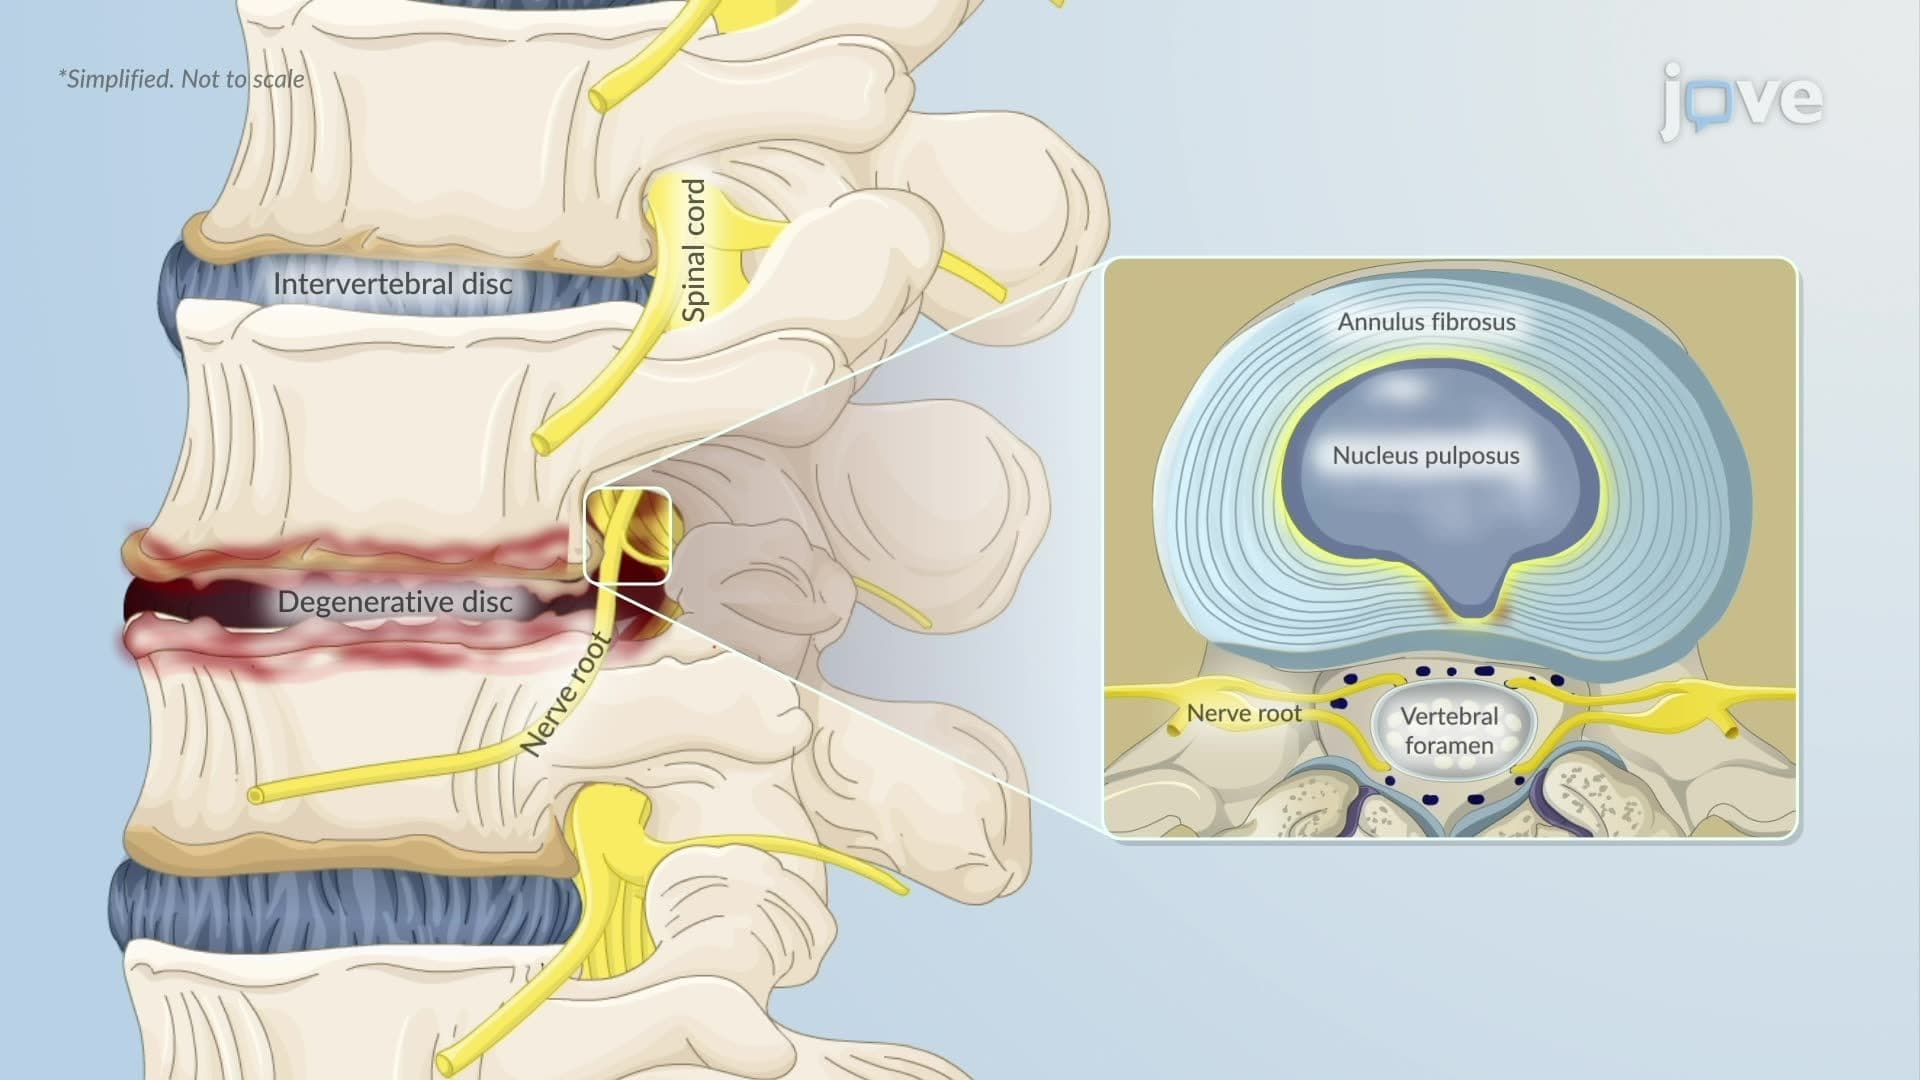
The symptoms of degenerative disc disease arise from a combination of mechanical compression, vascular compromise, and biochemical inflammation, which together disrupt nerve function and produce pain.Mechanical CompressionDisc degeneration reduces height and elasticity, predisposing to herniation of the nucleus pulposus, a major cause of radicular pain. Herniations may be protrusion (bulging with intact annulus), extrusion (nucleus extends beyond disc but remains connected), or sequestration...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology
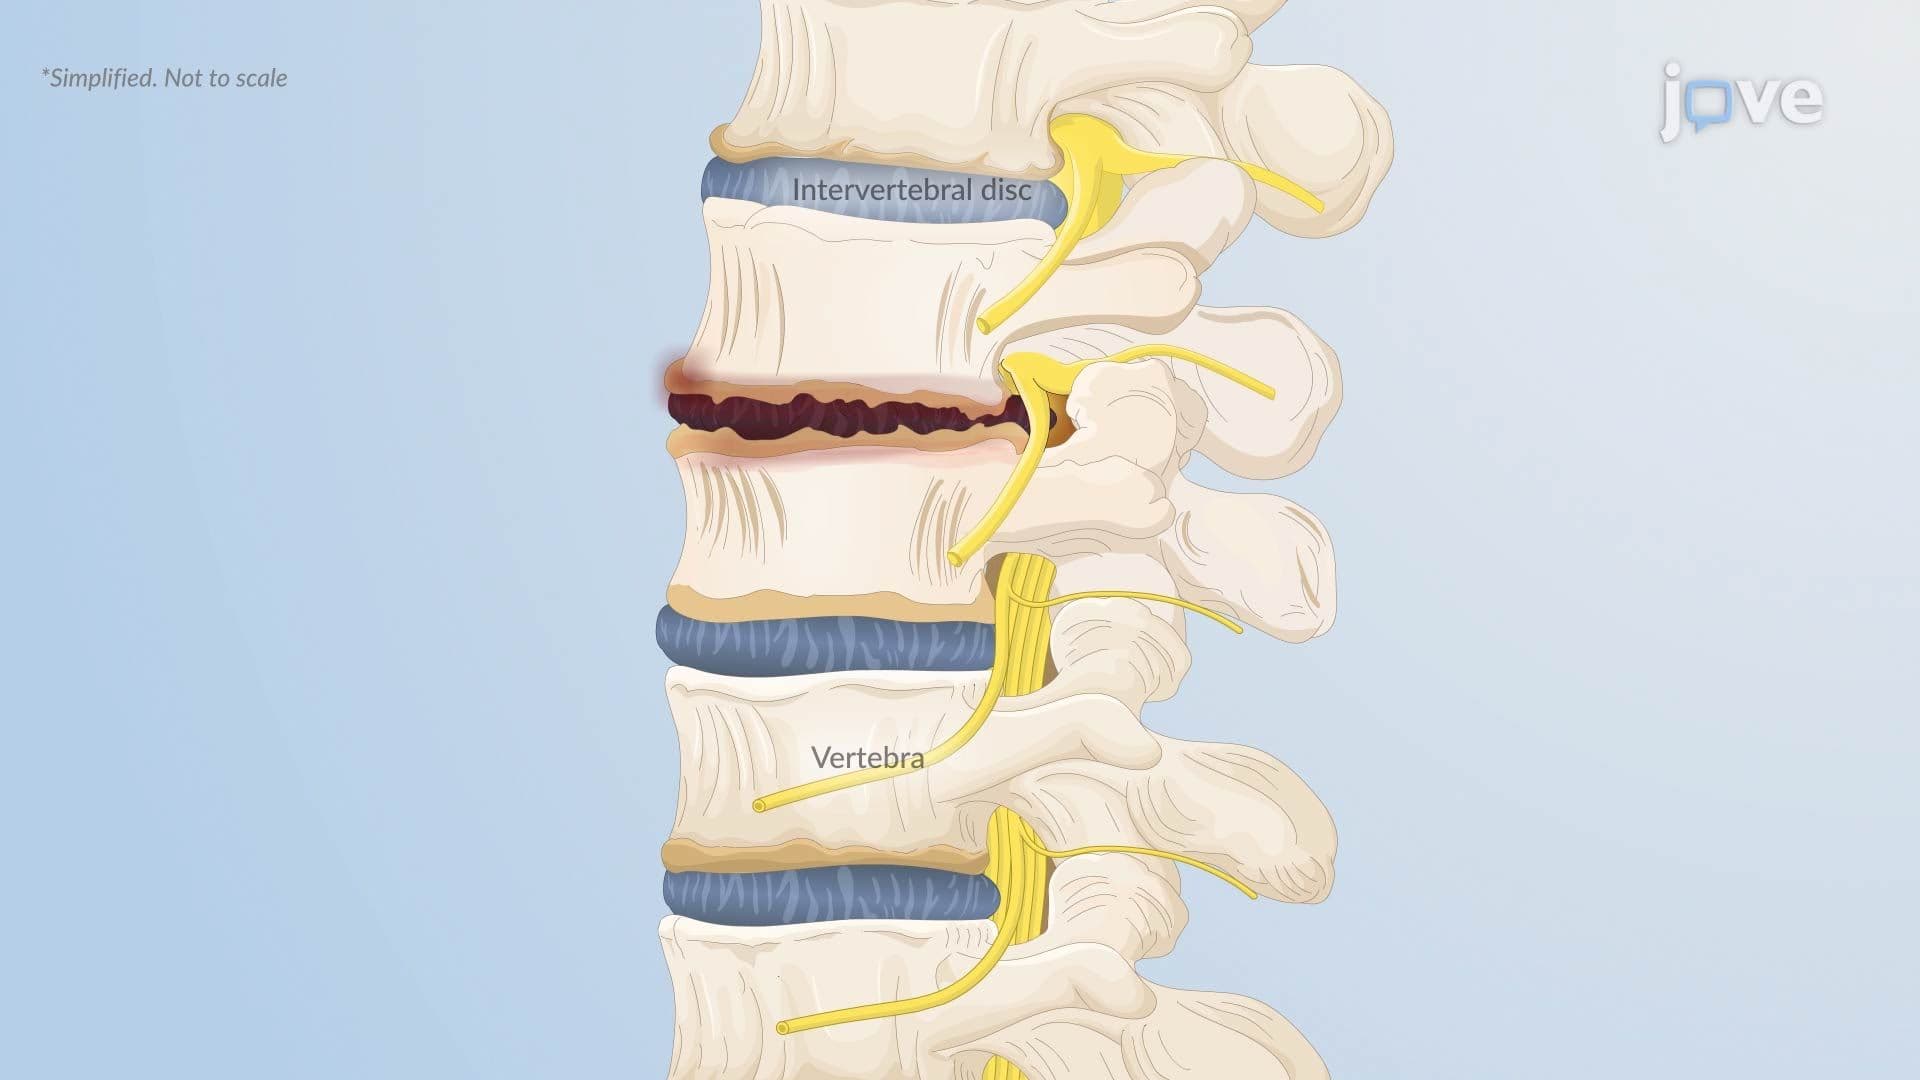
Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...
Herniated Intervertebral Disc l: Introduction01:29

Herniated Intervertebral Disc l: Introduction

Intervertebral disc herniation refers to the displacement of the nucleus pulposus (the gel-like inner core of the disc) through a tear or weakened area in the annulus fibrosus (the outer fibrous ring). The displaced disc material extends beyond the normal boundaries of the disc space and may compress or irritate nearby spinal nerve roots or, less commonly, the spinal cord.Etiology and Risk FactorsHerniation commonly results from degeneration, in which aging reduces disc hydration and...
Analgesia and Pain Management01:25

Analgesia and Pain Management

Pain is critical to various clinical pathologies, provoking an urgent need for effective management. Pain, whether acute or chronic, is a complex neurochemical process. Its alleviation depends on the type, with nonopioid analgesics effective for mild to moderate pain, such as musculoskeletal or inflammatory pain, while neuropathic pain responds best to anticonvulsants, tricyclic antidepressants, or serotonin/norepinephrine reuptake inhibitors. For severe acute or chronic pain, opioids may be...