Related Experiment Video
Updated: Jul 6, 2026
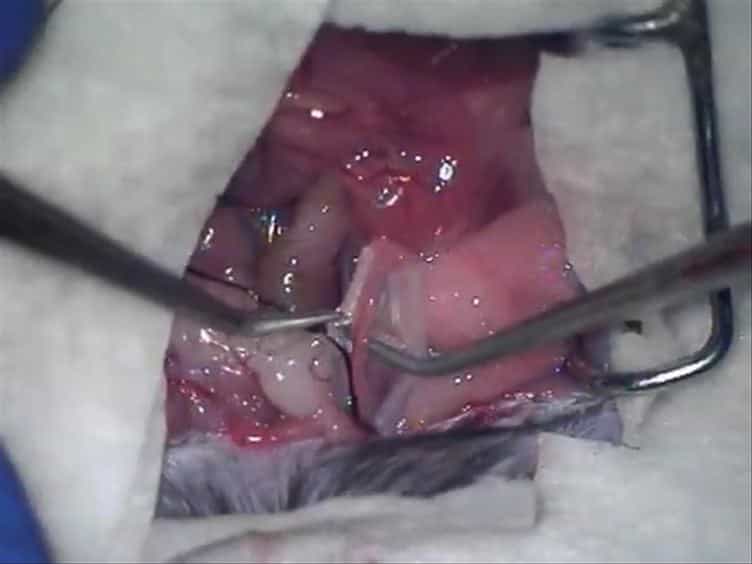

A Murine Model of Irreversible and Reversible Unilateral Ureteric Obstruction
Published on: December 20, 2014
[Vesicoureteral reflux and renal scarring]

Insights
Reflux nephropathy, a kidney scarring condition in children, often results from urinary tract infections and vesicoureteral reflux. Early detection and management are crucial to prevent long-term complications like chronic kidney disease.
Area of Science:
- Pediatric Nephrology
- Urology
- Medical Imaging
Context:
- Reflux nephropathy is an acquired focal renal scarring linked to vesicoureteral reflux (VUR), intrarenal reflux (IRR), urinary tract infections (UTI), and high intravesical pressure.
- Renal scarring can occur in 30-60% of children with VUR and symptomatic UTI, typically before age five.
- Girls have a higher risk due to increased UTI incidence.
Purpose:
- To differentiate reflux nephropathy from congenital renal scarring (hypo-dysplasia).
- To highlight the diagnostic role of 99mTc-DMSA renal scintigraphy as the gold standard.
- To emphasize the importance of serial follow-up for monitoring kidney growth and detecting complications.
Summary:
- 99mTc-DMSA renal scintigraphy is the gold standard for diagnosing reflux nephropathy (92% sensitivity, 98% specificity).
- Ultrasound is valuable for monitoring kidney growth over time.
- Reflux nephropathy and hypodysplasia are primary causes of chronic renal failure and hypertension in pediatric populations.
Impact:
- Long-term follow-up of children with reflux nephropathy is essential due to potential complications developing over 10-20 years.
- Uncontrolled hypertension and proteinuria predict a poor prognosis.
- ACE inhibitors and ARBs offer effective antihypertensive therapy, improving intrarenal hemodynamics and preserving renal function.
Abstract:
Reflux nephropathy is an acquired focal renal scarring due to the combination of vesicoureteral (VUR) and intrarenal reflux (IRR) associated with urinary tract infections (IUT) and/or permanently high intravesical pressure. Up to 30-60% of children with VUR and a history of symptomatic IUT have renal scarring at the time of their initial studies. The onset of renal scarring usually occurs early in life, usually before age five years and most frequently before three years of age. Girls are at greater risk for developing reflux nephropathy, because of increased incidence of IUT. Reflux nephropathy is different from a diffuse congenital renal scarring (hypo-dysplasia), which is usually discovered antenatally or during infancy in boys with severe VUR. Without serial follow-up (ultrasonography, intravenous pyelourography, 99mTc-DMSA scan) from birth, it is not always possible to differentiate congenital renal scarring from reflux nephropathy. In contrast to reflux nephropathy, congenital renal scarring cannot be prevented. 99mTc-DMSA renal scintigraphy is the gold standard technique (sensitivity 92%, specificity 98%) for the diagnosis of reflux nephropathy, but ultrasound is a good modality to monitor kidney growth over time. Reflux nephropathy and hypodysplasia are the main causes of chronic renal failure and arterial hypertension in children and adolescents in our country. The long-term follow-up of children with reflux nephropathy is mandatory, since its complications may take 10 to 20 years to develop. Uncontrollable arterial hypertension and proteinuria are the predictors of poor prognosis. The selective use of angiotensin converting enzyme inhibitors and/or angiotensin II receptor blockers is the efficient antihypertensive therapy, which also modify intrarenal haemodynamics and can preserve renal function.


Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:29
Acute Kidney Injury II: Pathophysiology
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...