Related Experiment Video
Updated: Jul 6, 2026
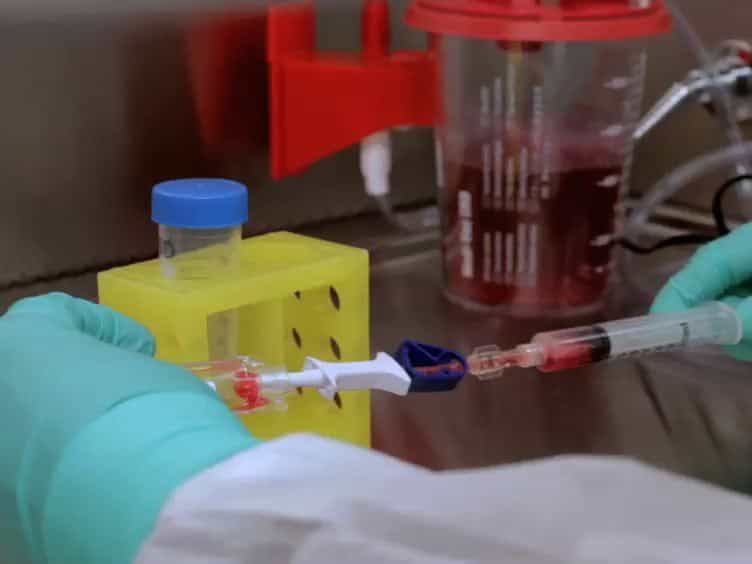

Expanding Cytotoxic T Lymphocytes from Umbilical Cord Blood that Target Cytomegalovirus, Epstein-Barr Virus, and Adenovirus
Published on: May 7, 2012
Cytomegalovirus infection in paediatric haemopoietic stem cell transplantation
A Lee Chong1, F Clinton, F Breatnach
1Department of Haematology & Oncology, Our Lady's Children's Hospital, Crumlin, Dublin.

A retrospective audit of CMV infection was undertaken to determine prevalence and outcome in the national paediatric Haemopoietic Stem Cell Transplant (HSCT) unit, with particular reference to surveillance and treatment. All patients undergoing HSCT (125 allogeneic, 50 autologous) from January 1994 to December 2004 were included. Nine underwent a second transplant for graft failure or disease recurrence. Of 134 allogeneic transplants performed, 62 were unrelated. Shell vial cultures of throat swabs and urine, and blood samples for pp65 antigenemia +/- PCR were tested weekly for a mean of 147 days post transplant. CMV negative blood products and filters were used in all. 11 rec+/donor-, 12rec-/donor+ and 10rec+/donor+ transplants were performed. All received prophylactic acyclovir, IVIG was prescribed for all but CMV -/- transplants. Initial detection of CMV was urine in 5 cases, four of whom developed antigenemia. Of ten patients who developed antigenemia, nine were treated with ganciclovir +/- foscarnet and two of these patients developed CMV pneumonitis and died. The current policy of strict surveillance, matching donor and recipient CMV status, use of CMV negative blood products and filters and pre-emptive therapy appears to be effective in controlling CMV disease/infection in the peritransplant period.
A retrospective audit of CMV infection was undertaken to determine prevalence and outcome in the national paediatric Haemopoietic Stem Cell Transplant (HSCT) unit, with particular reference to surveillance and treatment. All patients undergoing HSCT (125 allogeneic, 50 autologous) from January 1994 to December 2004 were included. Nine underwent a second transplant for graft failure or disease recurrence. Of 134 allogeneic transplants performed, 62 were unrelated. Shell vial cultures of throat swabs and urine, and blood samples for pp65 antigenemia +/- PCR were tested weekly for a mean of 147 days post transplant. CMV negative blood products and filters were used in all. 11 rec+/donor-, 12rec-/donor+ and 10rec+/donor+ transplants were performed. All received prophylactic acyclovir, IVIG was prescribed for all but CMV -/- transplants. Initial detection of CMV was urine in 5 cases, four of whom developed antigenemia. Of ten patients who developed antigenemia, nine were treated with ganciclovir +/- foscarnet and two of these patients developed CMV pneumonitis and died. The current policy of strict surveillance, matching donor and recipient CMV status, use of CMV negative blood products and filters and pre-emptive therapy appears to be effective in controlling CMV disease/infection in the peritransplant period.
Related Concept Videos
 01:27
Cytomegalovirus Disease
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:01
Regulation of Hematopoietic Stem Cells
 01:27
Cryptococcal Meningitis