Related Experiment Video
Updated: Jul 6, 2026


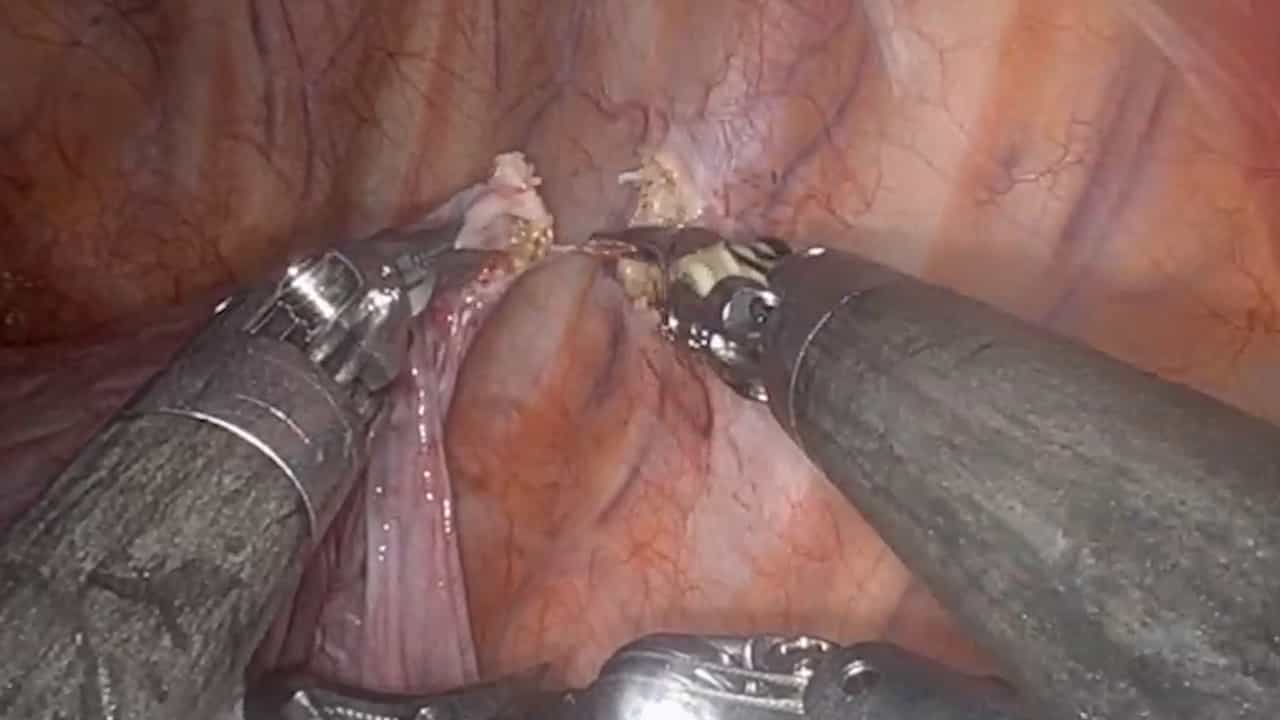
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Abscess of residual lobe after pulmonary resection for lung cancer
Tommaso Ligabue1, Luca Voltolini, Claudia Ghiribelli
1Thoracic Surgery Unit, University Hospital of Siena, Viale Bracci 14, 53100 Siena, Italy. tligabue@hotmail.com

Abstract:
Abscess of the residual lobe after lobectomy is a rare but potentially lethal complication. Between January 1975 and December 2006, 1,460 patients underwent elective pulmonary lobectomy for non-small-cell lung cancer at our institution. Abscess of the residual lung parenchyma occurred in 5 (0.3%) cases (4 bilobectomies and 1 lobectomy). Postoperative chest radiography showed incomplete expansion and consolidation of residual lung parenchyma. Flexible bronchoscopy revealed persistent bronchial occlusion from purulent secretions and/or bronchial collapse. Computed tomography in 3 patients demonstrated lung abscess foci. Surgical treatment included completion right pneumonectomy in 3 patients and a middle lobectomy in one. Complications after repeat thoracotomy comprised contralateral pneumonia and sepsis in 1 patient. Residual lobar abscess after lobectomy should be suspected in patients presenting with fever, leukocytosis, bronchial obstruction and lung consolidation despite antibiotic therapy, physiotherapy and bronchoscopy. Computed tomography is mandatory for early diagnosis. Surgical resection of the affected lobe is recommended.
Insights
Residual lobar abscess is a rare, lethal complication after lung lobectomy. Early diagnosis via CT scans and surgical resection are recommended for suspected cases presenting with fever and consolidation.
Area of Science:
- Thoracic Surgery
- Pulmonary Medicine
- Surgical Complications
Background:
- Post-lobectomy abscess of the residual lung lobe is a rare but serious complication.
- Non-small-cell lung cancer surgery involves risks, including residual lobe complications.
Purpose of the Study:
- To investigate the incidence, diagnosis, and management of residual lobar abscess following pulmonary lobectomy.
- To highlight key diagnostic indicators and recommended treatments for this rare complication.
Main Methods:
- Retrospective review of 1,460 patients undergoing pulmonary lobectomy for non-small-cell lung cancer (1975-2006).
- Analysis of diagnostic methods including chest radiography, flexible bronchoscopy, and computed tomography (CT).
- Evaluation of surgical interventions and post-operative outcomes.
Main Results:
- Five cases (0.3%) of residual lobar abscess were identified (4 bilobectomies, 1 lobectomy).
- Diagnostic findings included consolidation, bronchial occlusion, and CT-identified abscess foci.
- Surgical treatment involved completion pneumonectomy (3 patients) or lobectomy (1 patient), with one instance of sepsis.
Conclusions:
- Residual lobar abscess should be suspected in patients with persistent fever, leukocytosis, and consolidation post-lobectomy.
- Computed tomography is crucial for early and accurate diagnosis.
- Surgical resection of the affected lobe is the recommended treatment approach.
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:17
Gross Anatomy of the Lungs
 01:13
Pleura of the Lungs