Related Experiment Video
Updated: Jul 6, 2026
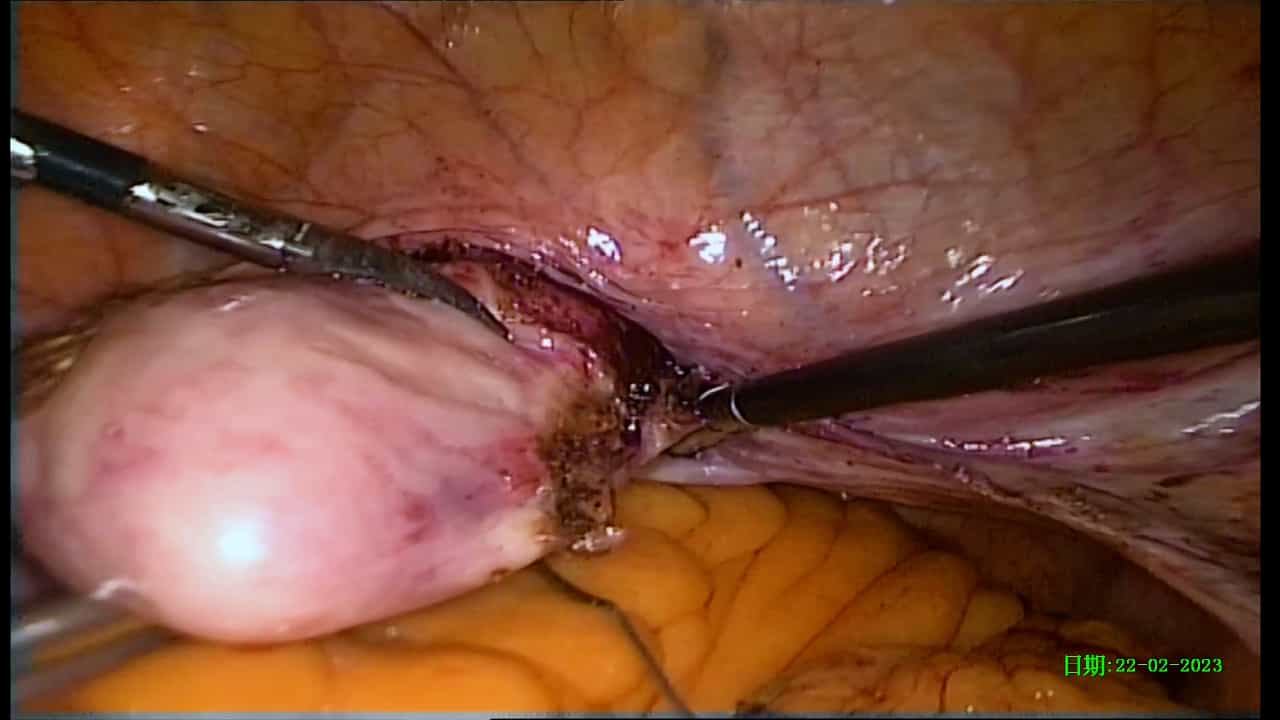

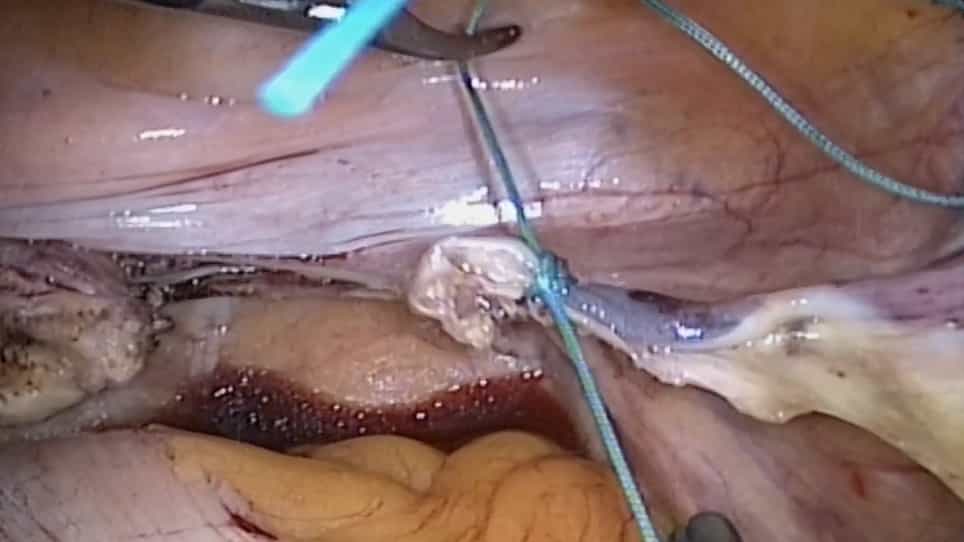
Laparoscopic Non-Mesh Cerclage Pectopexy with Uterine Preservation for Pelvic Organ Prolapse
Published on: October 25, 2024
Genital prolapse surgery after a shift in treatment tradition: an analysis of subsequent prolapse surgery
Kristina Crafoord1, Adam Sydsjö, Preben Kjølhede
1Department of Obstetrics and Gynecology, Orebro University Hospital, Orebro, Sweden. kristina.crafoord@orebroll.se

Objective:
To determine whether the shift in treatment tradition of genital prolapse surgery was followed by a change in the occurrence of subsequent prolapse surgery, and to analyze the complementary and recurrent surgery with respect to the size of the prolapse and the extent of the primary surgery.
Methods:
A retrospective study of patients consecutively operated with primary prolapse surgery in three Swedish hospitals in two time periods: 261 patients in 1983 (Period I) and 281 patients in 1993 (Period II). Clinical data were obtained from the patient records. A follow-up period of 6 years was used for both periods.
Results:
Subsequent prolapse surgery was seen significantly more often in Period II than in Period I (7.7 versus 2.7%), and after selective repairs compared with complete repairs (7.7 versus 3.2%). Despite a significant reduction in the use of posterior repair between the time periods, no significant increase was seen in complementary posterior repairs compared with complementary repair in any of the other compartments. Size of the prolapse at the primary surgery or hysterectomy did not seem to influence the occurrence of subsequent prolapse surgery. The postoperative complication rate was significantly higher after complete repairs than after selective repair, and especially when posterior repair was included in the operation.
Conclusion:
Subsequent prolapse surgery is slightly more common after selective repair than after complete repair. However, selective repairs are encumbered with a lower complication rate. The results of this study appear to be in favor of a restrictive use of 'prophylactic' posterior repair.