Related Experiment Video
Updated: Jul 6, 2026


Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
[Electrocardiographic changes in acute organophosphate poisoning]
Cătălina Lionte1, L Sorodoc, O Petriş
1Spitalul Clinic de Urgenţe "Sf. Ioan", Clinica Medicală, Facultatea de Medicină, Universitatea de Medicină si Farmacie "Gr.T. Popa", Iaşi.

Abstract:
Cardiac complications often accompany poisoning with organophosphates. These may be serious and often fatal, being represented by cardiac arrhythmias, electrocardiographic abnormalities and conduction defects, as well as myocardial infarction, a rarely reported complication of acute pesticide poisoning. The extent and pathogenesis of cardiac toxicity from these compounds is not yet clearly defined. We report the case of a 57-year-old woman who presented to our emergency department with coma and acute non-cardiogenic pulmonary edema, as a result of organophosphates ingestion. She was resuscitated for asystole presented shortly after admission; prolonged QTc interval, ST-T changes, right bundle branch block, ventricular tachycardia were recorded. Finally she developed acute anteroseptal myocardial infarction and died despite serum cholinesterase normalization. We believe that admission in an intensive care unit, careful electrocardiographic and enzymatic monitoring of all patients is important for the diagnosis and treatment of cardiac complications of organophosphates poisoning.
Insights
Organophosphate poisoning can cause severe cardiac issues, including fatal arrhythmias and myocardial infarction. Early intensive care unit admission and monitoring are crucial for managing these serious cardiovascular complications.
Area of Science:
- Toxicology
- Cardiology
- Emergency Medicine
Background:
- Organophosphate (OP) poisoning is a significant global health concern, primarily known for its neurological effects.
- Cardiac complications, though less understood, can be severe and fatal in OP poisoning.
- Myocardial infarction is a rarely reported but serious cardiac event in acute pesticide poisoning.
Observation:
- A 57-year-old woman ingested organophosphates, presenting with coma and non-cardiogenic pulmonary edema.
- She experienced asystole, requiring resuscitation, and subsequent cardiac abnormalities including prolonged QTc, ST-T changes, right bundle branch block, and ventricular tachycardia.
- The patient ultimately developed acute anteroseptal myocardial infarction and died despite normalized cholinesterase levels.
Findings:
- Organophosphate exposure can lead to a spectrum of cardiac toxicity, including arrhythmias and conduction defects.
- Acute myocardial infarction is a potential, albeit rare, complication of severe organophosphate poisoning.
- Cardiac events may occur even after initial toxicological markers, like cholinesterase levels, normalize.
Implications:
- Intensive care unit (ICU) admission is vital for patients with organophosphate poisoning.
- Continuous electrocardiographic (ECG) and cardiac enzyme monitoring are essential for early diagnosis and management of cardiac complications.
- Understanding the pathogenesis of OP-induced cardiotoxicity is critical for improving patient outcomes.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:30
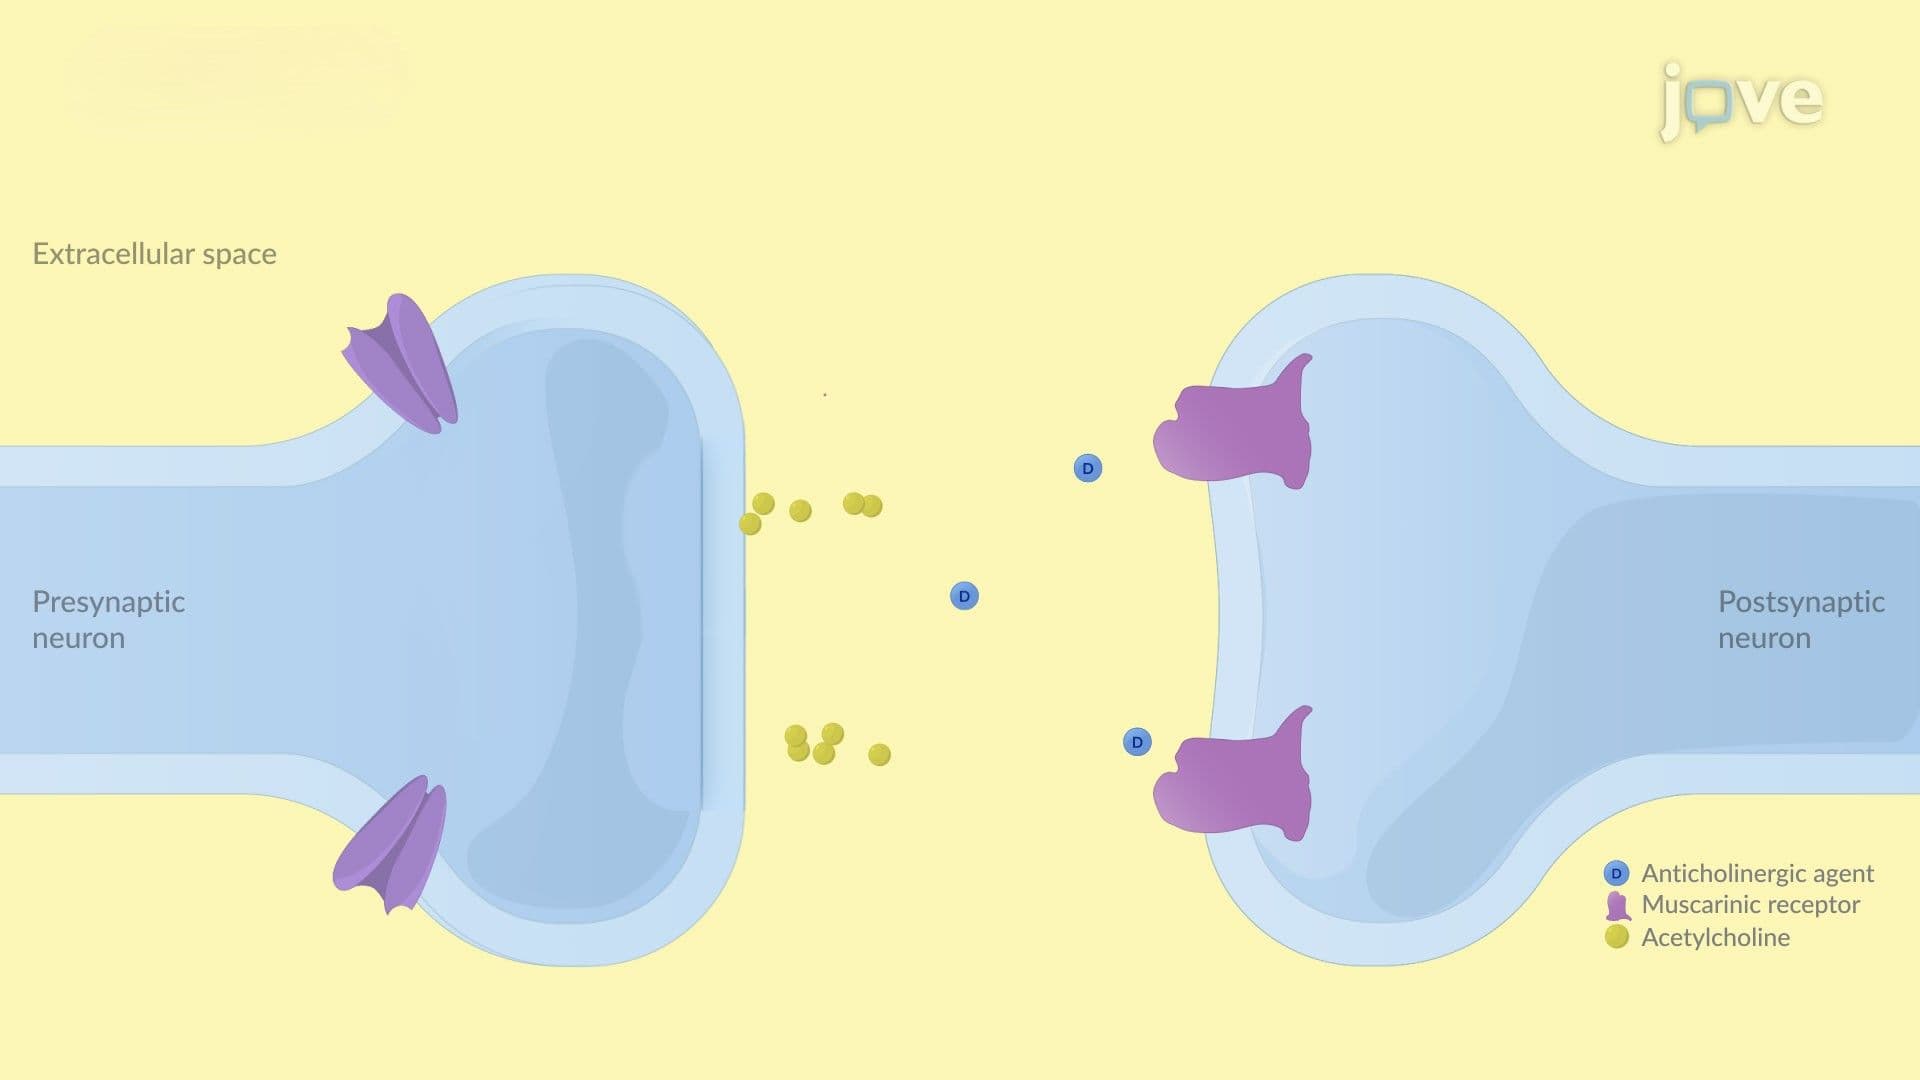
Toxidromes: Clinical Features
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:19
Depolarizing Blockers: Pharmocokinetics