Related Experiment Video
Updated: Jul 6, 2026
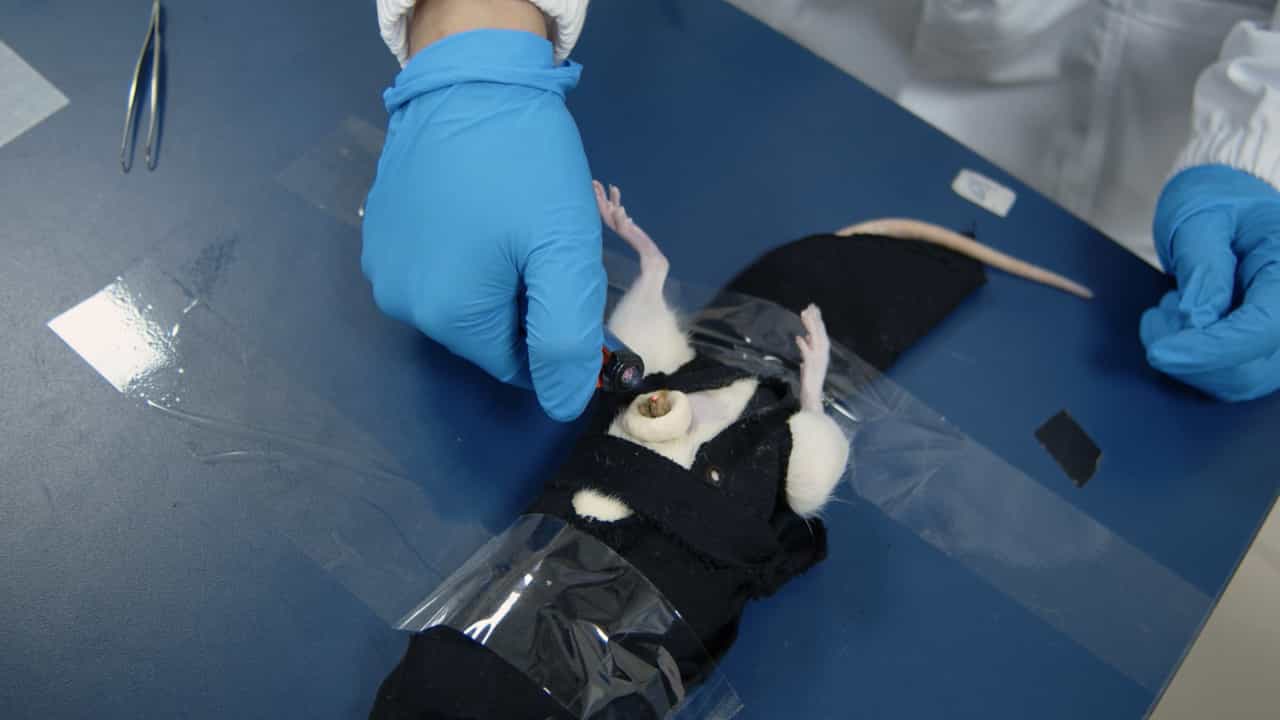

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Premenstrual syndrome
Kimberly Ann Yonkers1, P M Shaughn O'Brien, Elias Eriksson
1Department of Psychiatry, Yale School of Medicine, CT 06510, USA. Kimberly.Yonkers@yale.edu

Most women of reproductive age have some physical discomfort or dysphoria in the weeks before menstruation. Symptoms are often mild, but can be severe enough to substantially affect daily activities. About 5-8% of women thus suffer from severe premenstrual syndrome (PMS); most of these women also meet criteria for premenstrual dysphoric disorder (PMDD). Mood and behavioural symptoms, including irritability, tension, depressed mood, tearfulness, and mood swings, are the most distressing, but somatic complaints, such as breast tenderness and bloating, can also be problematic. We outline theories for the underlying causes of severe PMS, and describe two main methods of treating it: one targeting the hypothalamus-pituitary-ovary axis, and the other targeting brain serotonergic synapses. Fluctuations in gonadal hormone levels trigger the symptoms, and thus interventions that abolish ovarian cyclicity, including long-acting analogues of gonadotropin-releasing hormone (GnRH) or oestradiol (administered as patches or implants), effectively reduce the symptoms, as can some oral contraceptives. The effectiveness of serotonin reuptake inhibitors, taken throughout the cycle or during luteal phases only, is also well established.
Most women of reproductive age have some physical discomfort or dysphoria in the weeks before menstruation. Symptoms are often mild, but can be severe enough to substantially affect daily activities. About 5-8% of women thus suffer from severe premenstrual syndrome (PMS); most of these women also meet criteria for premenstrual dysphoric disorder (PMDD). Mood and behavioural symptoms, including irritability, tension, depressed mood, tearfulness, and mood swings, are the most distressing, but somatic complaints, such as breast tenderness and bloating, can also be problematic. We outline theories for the underlying causes of severe PMS, and describe two main methods of treating it: one targeting the hypothalamus-pituitary-ovary axis, and the other targeting brain serotonergic synapses. Fluctuations in gonadal hormone levels trigger the symptoms, and thus interventions that abolish ovarian cyclicity, including long-acting analogues of gonadotropin-releasing hormone (GnRH) or oestradiol (administered as patches or implants), effectively reduce the symptoms, as can some oral contraceptives. The effectiveness of serotonin reuptake inhibitors, taken throughout the cycle or during luteal phases only, is also well established.
Related Concept Videos
 01:24
Disorders of the Female Reproductive System
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:28
Menopause
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.