Related Experiment Video
Updated: Jul 5, 2026


Measuring Psoriasis Severity at Home
Published on: March 1, 2024
Relative responsiveness of physician/assessor-derived and patient-derived core set measures in rheumatoid arthritis
Tuhina Neogi1, Hui Xie, David T Felson
1Clinical Epidemiology Research and Training Unit, Boston University School of Medicine, Boston, Massachusetts 02118, USA.

Objective:
We assessed whether individual American College of Rheumatology core set measures (CSM), and the CSM grouped as composite patient-derived (CPD) or composite physician/assessor-derived (CMD), performed differently in rheumatoid arthritis (RA) clinical trials.
Methods:
We used data from 9 RA trials [anti-tumor necrosis factor-alpha (TNF-alpha) and disease modifying antirheumatic drug (DMARD)] in which CSM had been assessed, conducted from the early 1990s to present, with a total of 2969 patients. We grouped the CSM as CPD (pain, patient global assessment, function) and CMD [tender joint count (TJC), swollen joint count (SJC), physician global, inflammatory marker]. Using bootstrap simulation, we estimated the sample size that would be required to distinguish active treatment from placebo with the Wilcoxon rank-sum test in the clinical trials for the outcomes of percentage change of each individual CSM, of the Disease Activity Score (DAS), and average percentage change of the CMD or of the CPD.
Results:
Comparing the performance of individual CSM relative to one another, the physician and patient global assessments and TJC would require the lowest sample sizes to distinguish active treatment from placebo, while use of the SJC, inflammatory marker, and function would require the highest. The CMD performed similarly to the DAS, requiring similar sample sizes, while the CPD would require 1.7 times greater sample size to distinguish treatment from placebo. The results were similar across DMARD and anti-TNF-alpha trials.
Conclusion:
Because of their demonstrated sensitivity to change, composite measures assessing RA outcomes in clinical trials should continue to include physician/assessor-derived core set measure assessments.

Related Concept Videos
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:13
Bioequivalence studies: Biowaivers
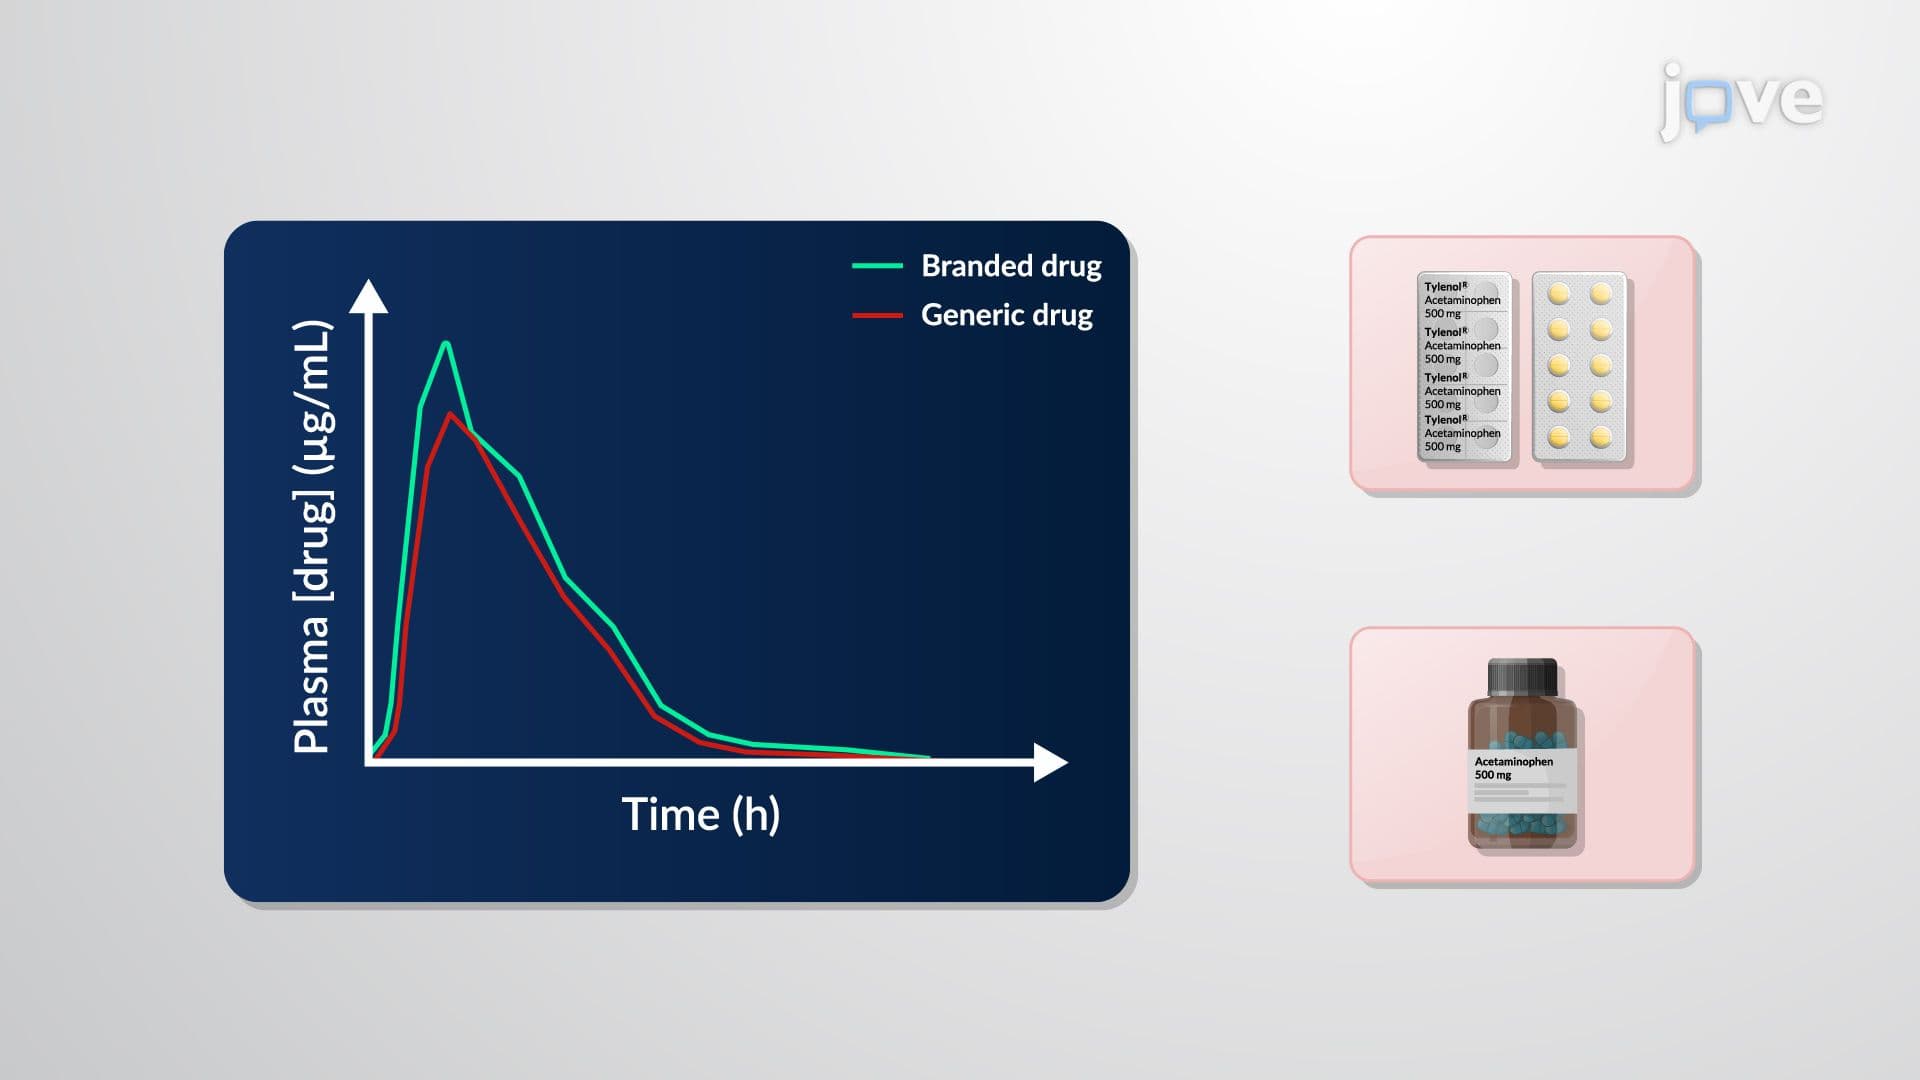 01:16
Bioequivalence Data: Statistical Interpretation
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...