Related Experiment Video
Updated: Jul 5, 2026
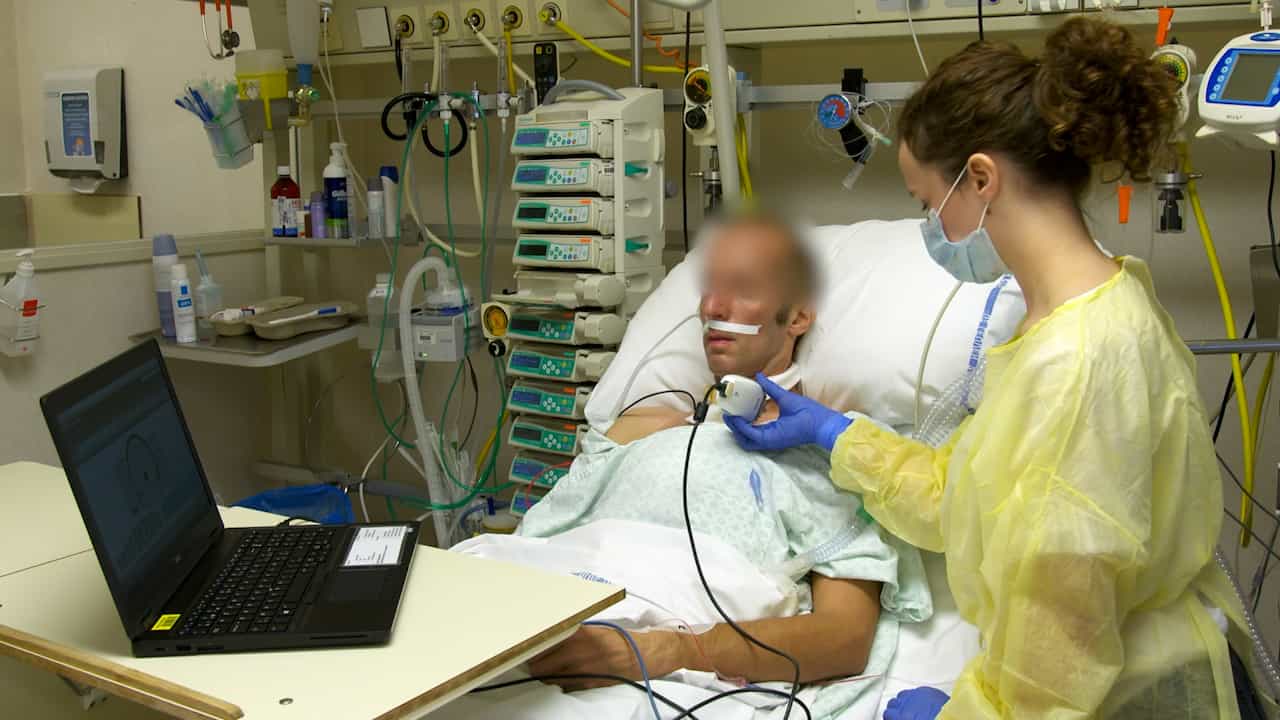
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Noninvasive mechanical ventilation may be useful in treating patients who fail weaning from invasive mechanical
Cristiane E Trevisan1, Silvia R Vieira,
1Intensive Care Unit, Hospital de Clínicas de Porto Alegre, Universidade Federal do Rio Grande do Sul, Porto Rua Ramiro Barcelos, 2350, CEP 90035-903, Porto Alegre, RS, Brazil. cris.trevisan@yahoo.com.br

Introduction:
The use of noninvasive positive-pressure mechanical ventilation (NPPV) has been investigated in several acute respiratory failure situations. Questions remain about its benefits when used in weaning patients from invasive mechanical ventilation (IMV). The objective of this study was to evaluate the use of bi-level NPPV for patients who fail weaning from IMV.
Methods:
This experimental randomized clinical trial followed up patients undergoing IMV weaning, under ventilation for more than 48 hours, and who failed a spontaneous breathing T-piece trial. Patients with contraindications to NPPV were excluded. Before T-piece placement, arterial gases, maximal inspiratory pressure, and other parameters of IMV support were measured. During the trial, respiratory rate, tidal volume, minute volume, rapid shallow breathing index, heart rate, arterial blood pressure, and peripheral oxygen saturation were measured at 1 and 30 minutes. After failing a T-piece trial, patients were randomly divided in two groups: (a) those who were extubated and placed on NPPV and (b) those who were returned to IMV. Group results were compared using the Student t test and the chi-square test.
Results:
Of 65 patients who failed T-piece trials, 28 were placed on NPPV and 37 were placed on IMV. The ages of patients in the NPPV and IMV groups were 67.6 +/- 15.5 and 59.7 +/- 17.6 years, respectively. Heart disease, post-surgery respiratory failure, and chronic pulmonary disease aggravation were the most frequent causes of IMV use. In both groups, ventilation time before T-piece trial was 7.3 +/- 4.1 days. Heart and respiratory parameters were similar for the two groups at 1 and 30 minutes of T-piece trial. The percentage of complications in the NPPV group was lower (28.6% versus 75.7%), with lower incidences of pneumonia and tracheotomy. Length of stay in the intensive care unit and mortality were not statistically different when comparing the groups.
Conclusion:
The results suggest that NPPV is a good alternative for ventilation of patients who fail initial weaning attempts. NPPV reduces the incidence of pneumonia associated with mechanical ventilation and the need for tracheotomy.
Trial Registration:
CEP HCPA (02-114).

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management