Related Experiment Video
Updated: Jul 5, 2026
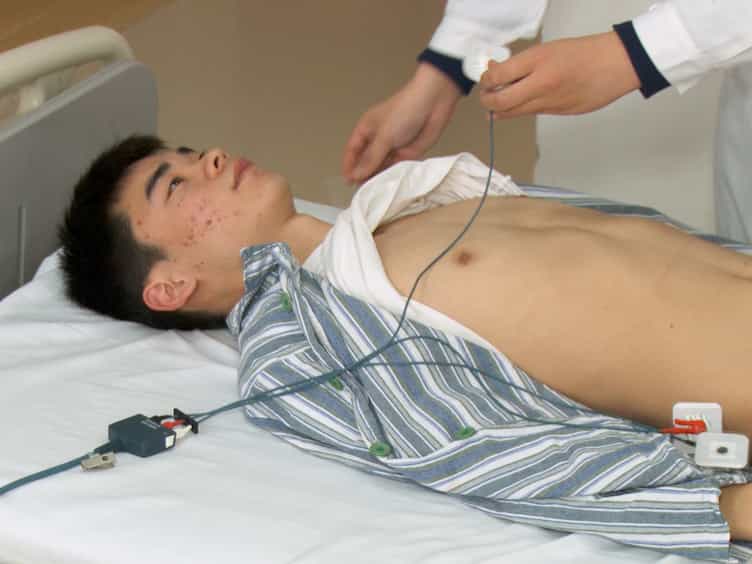

Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
Blood pressure variability and arterial elasticity in hyperlipidaemic subjects
H M Rafidah1, A Azizi, M N Noriah
1Faculty of Medicine, International Islamic University of Malaysia, Bandar Indera Mahkota, Kuantan 25200, Malaysia. rafidahhanim@gmail.com

Insights
Hyperlipidaemic individuals exhibit higher blood pressure variability (BPV) compared to those with normal lipid levels. While large arterial compliance showed an inverse correlation with systolic blood pressure, BPV did not correlate with arterial compliance.
Area of Science:
- Cardiovascular Medicine
- Lipid Metabolism
- Hypertension Research
Background:
- Assessing myocardial infarction risk solely by low-density lipoprotein or total cholesterol (TC) is debated.
- The TC to high-density lipoprotein cholesterol (TC:HDL) ratio is a better indicator of coronary artery disease risk.
- Hyperlipidaemia is defined as a TC:HDL ratio > 5.0.
Purpose of the Study:
- To investigate the relationship between blood pressure variability (BPV) and arterial compliance in hyperlipidaemic subjects.
- To compare BPV and arterial compliance in hyperlipidaemic versus normolipidaemic individuals.
Main Methods:
- Age-, gender-, and weight-matched study design comparing 22 hyperlipidaemic subjects with normolipidaemic controls.
- 24-hour ambulatory blood pressure monitoring to assess BPV.
- Measurement of large and small arterial compliances.
Main Results:
- Hyperlipidaemic subjects demonstrated significantly higher 24-hour systolic, diastolic, and mean arterial BPV.
- No significant differences in large or small arterial compliances were found between the groups.
- A significant inverse relationship was observed between systolic blood pressure and large arterial compliance (r=-0.46, p<0.05).
- No correlation was found between BPV and arterial compliances.
Conclusions:
- Blood pressure variability is elevated in individuals with hyperlipidaemia.
- Large arterial compliance is negatively correlated with systolic blood pressure in hyperlipidaemic individuals.
Introduction:
It is debatable whether the assessment of low density lipoprotein or total cholesterol (TC) alone is sufficient to identify an individual's risk of having myocardial infarction. In the Framingham study, the risk of coronary artery disease was better indicated by an increase in the TC to high density lipoprotein cholesterol (TC: HDL) ratio. The aim of this study is to determine the relationship between blood pressure variability (BPV) and arterial compliances in hyperlipidaemics, which was defined as TC:HDL of more than 5.0 as compared to normolipidaemics.
Methods:
22 subjects with hyperlipidaemia were age-, gender- and weight-matched with normolipidaemic controls. 24-hour ambulatory blood pressure monitoring was recorded and arterial compliances were measured.
Results:
There were significantly higher 24-hour systolic (SBP) (19.9 +/- 6.1 mmHg vs. 16.1 +/- 4.4 mmHg, p-value is less than 0.01), diastolic (16.6 +/- 4.7 mmHg vs. 13.9 +/- 4.8 mmHg, p-value is less than 0.05) and mean arterial (16.3 +/- 4.9 mmHg vs. 13.3 +/- 4.7 mmHg, p-value is less than 0.05) BPVs in the hyperlipidaemic group as compared to the normolipidaemic group. There were no significant differences in large and small arterial compliances between groups. There was a significant inverse relationship between SBP and large arterial compliance (r-value equals to -0.46, p-value is less than 0.05). There was no correlation between BPV and arterial compliances.
Conclusion:
The BPV was higher in hyperlipidaemic subjects as compared to normolipidaemic subjects. Large arterial compliance was negatively correlated with SBP in hyperlipidaemic subjects.
Related Concept Videos
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation