Related Experiment Video
Updated: Jul 5, 2026
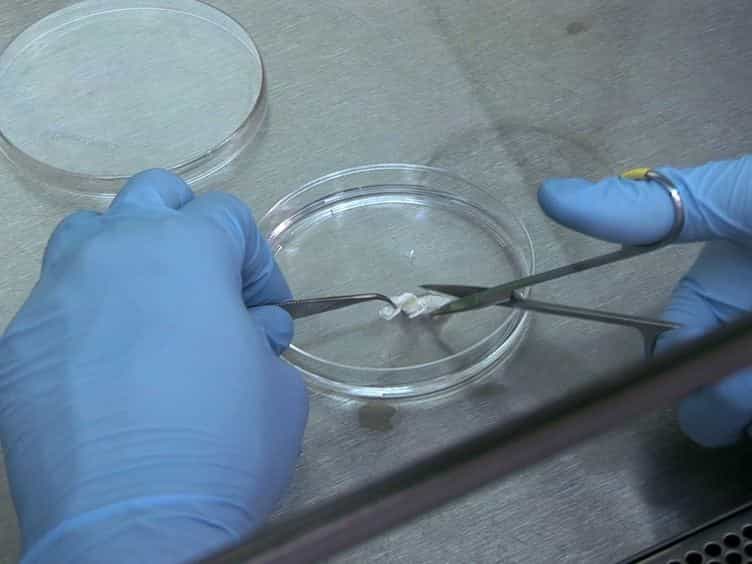
Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Biomechanics of the anterior cruciate ligament and implications for surgical reconstruction
1Department for Trauma and Orthopaedic Surgery, Hand and Reconstructive Surgery, St. Vinzenz Hospital, Merheimer Strasse 221-223, D-50733, Cologne, Germany, dargel@dshs-koeln.de.

Abstract:
Injury to the anterior cruciate ligament (ACL) is regarded as critical to the physiological kinematics of the femoral-tibial joint, its disruption eventually causing long-term functional impairment. Both the initial trauma and the pathologic motion pattern of the injured knee may result in primary degenerative lesions of the secondary stabilisers of the knee, each of which are associated with the early onset of osteoarthritis. Consequently, there is a wide consensus that young and active patients may profit from reconstructing the ACL. Several factors have been identified as significantly influencing the biomechanical characteristics and the functional outcome of an ACL reconstructed knee joint. These factors are: (1) individual choice of autologous graft material using either patellar tendon-bone grafts or quadrupled hamstring tendon grafts, (2) anatomical bone tunnel placement within the footprints of the native ACL, (3) adequate substitute tension after cyclic graft preconditioning, and (4) graft fixation close to the joint line using biodegradable graft fixation materials that provide an initial fixation strength exceeding those loads commonly expected during rehabilitation. Under observance of these factors, the literature encourages mid-to long-term clinical and functional outcomes after ACL reconstruction.
