Related Experiment Video
Updated: Jul 5, 2026
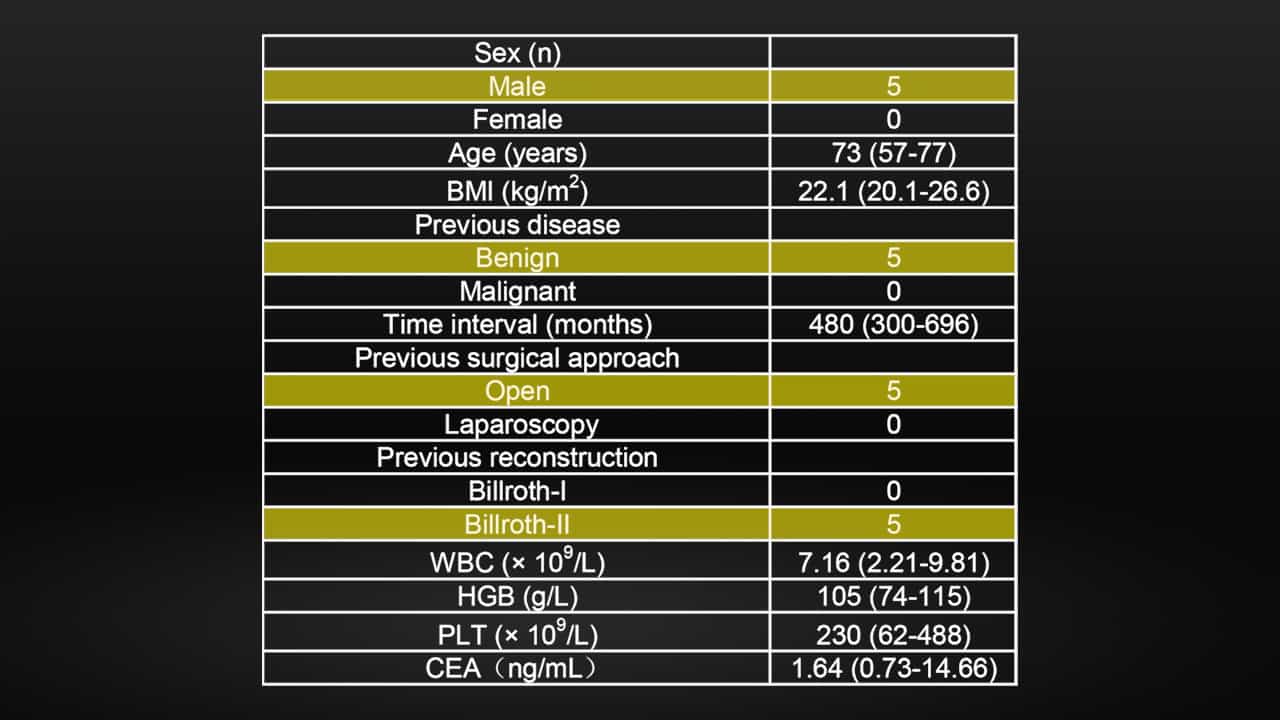
Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Clinical outcome of esophageal cancer after distal gastrectomy: a prospective study
1Division of Thoracic Surgery, Department of Surgery, Jiangsu Province Tumor Hospital, Nanjing 210009, China. lihouhuai@vip.163.com

Objectives:
To investigate the clinicopathological characteristics and surgical outcome of thoracic esophageal cancer after gastrectomy, and compare with those without gastrectomy.
Result:
Among 1411 esophageal cancer patients who underwent curative operation, 48 (3.4%) had a history of distal gastrectomy, the interval between gastrectomy and esophagectomy was significantly shorter in those gastrectomized for gastric cancer (11.5+/-8.2 years) than for peptic ulcer (24.6+/-9.2 years), the proportion of lower-third tumors and multiple esophageal cancer was significantly higher compared with that of the non-gastrectomized patients (50.0% vs. 33.1%, P=0.033; 14.6% vs. 5.3%, P=0.006, respectively), this increase was more pronounced after Billroth I vs. Billroth II gastrectomy. Pathologically, the esophageal cancers after gastrectomy frequently showed expansive growth pattern (39.6%), while those without gastrectomy dominantly showed infiltrative growth pattern (40.3%) (P=0.012), the coexisting lesions showed well-differentiated squamous cell carcinoma confined within the superficial mucosal layer. Compared with the non-gastrectomized patients, the operative time (311.2+/-86.0 vs. 263.7+/-84.9 min; P<0.001) was longer and blood loss (4.38+/-1.33 vs. 3.57+/-1.82 IU; P=0.003) was more, the postoperative hospital stay was significantly longer in gastrectomized patients (median 69 days vs. 40 days, P<0.001). The overall 1, 3, 5, 10-year survival of gastrectomized and non-gastrectomized patients were similar, and their cause-specific 5-year survival were 65% vs. 44% (P=0.992).
Conclusions:
Gastrectomy (especially the Billroth I) precipitated subsequent chronic gastroesophageal reflux and induced the development of squamous dysplasia and carcinoma at multiple locations in the esophagus. Surgical treatment of the gastrectomized patients should be considered as a reliable therapeutic modality because of favorable prognoses.

Related Concept Videos
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...