Related Experiment Video
Updated: Jul 5, 2026
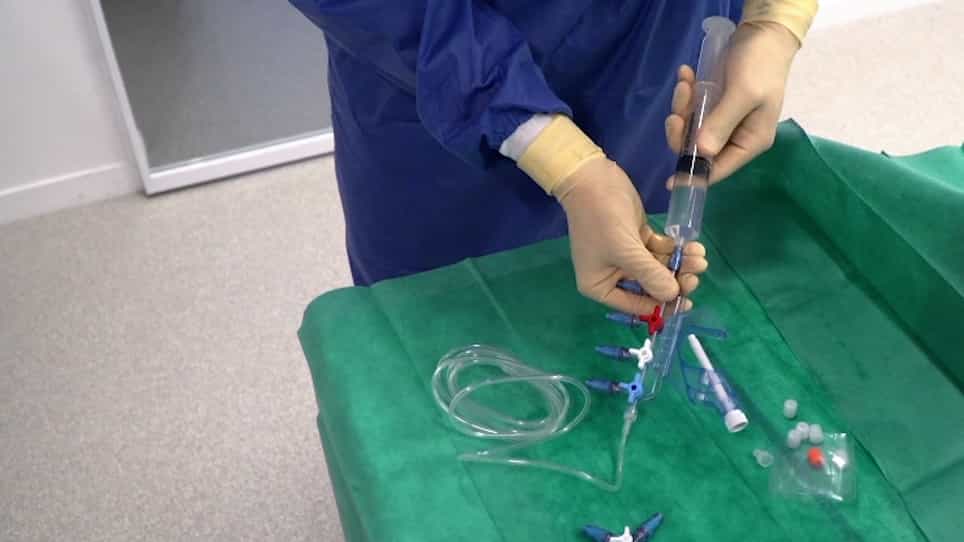
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Systematic intervention to reduce central line-associated bloodstream infection rates in a pediatric cardiac
John M Costello1, Debra Forbes Morrow, Dionne A Graham
1Division of Cardiac Intensive Care, Department of Cardiology, Children's Hospital Boston, Harvard Medical School, Boston, MA 02115, USA. john.costello@cardio.chboston.org

Insights
A staff education and practice change initiative significantly reduced central line-associated bloodstream infections (CLABSI) in a pediatric cardiac ICU. This intervention lowered CLABSI rates, improving patient safety and outcomes.
Area of Science:
- Pediatric critical care medicine
- Infection control and prevention
- Healthcare quality improvement
Background:
- Central line-associated bloodstream infections (CLABSI) are a significant concern in pediatric cardiac intensive care units (ICUs).
- Effective prevention strategies are crucial to reduce patient morbidity and mortality.
- Previous infection rates in the unit were higher than national benchmarks.
Purpose of the Study:
- To evaluate the impact of a staff education and practice change intervention on CLABSI rates.
- To determine if a multidisciplinary approach could decrease healthcare-associated infections in a pediatric cardiac ICU.
Main Methods:
- A retrospective, interrupted time-series study design was used.
- Data were collected from April 2004 to December 2006 for all patients in a pediatric cardiac ICU.
- Interventions included staff education, increased awareness, and implementation of central line bundles and daily goal sheets.
Main Results:
- The mean CLABSI rate decreased from 7.8 infections per 1000 catheter-days preintervention to 2.3 infections per 1000 catheter-days during the full intervention period.
- The preintervention rate was significantly higher than the national benchmark for pediatric ICUs.
- The postintervention rate was lower than the benchmark, though not statistically significant.
Conclusions:
- A multidisciplinary, evidence-based initiative effectively reduced CLABSI rates in a pediatric cardiac ICU.
- The findings support the implementation of similar comprehensive infection control programs.
- Sustained efforts in infection prevention are vital for improving patient safety in critical care settings.
Objective:
Our goal was to determine whether an intervention involving staff education, increased awareness, and practice changes would decrease central line-associated bloodstream infection rates in a pediatric cardiac ICU.
Methods:
A retrospective, interventional study using an interrupted time-series design was conducted to compare central line-associated bloodstream infection rates during 3 time periods for all patients admitted to our pediatric cardiac ICU between April 1, 2004, and December 31, 2006. During the preintervention period (April 2004 to December 2004), a committee was convened to track and prevent nosocomial infections. Pretesting demonstrated knowledge deficits regarding nosocomial infection prevention, and educational tools were developed. During the partial intervention period (January 2005 to March 2006), a comprehensive central line-associated bloodstream infection prevention initiative was implemented, including establishment of a unit-based infection control nurse position, education for physicians and nurses, real-time feedback on central line-associated bloodstream infection data, implementation of central venous line insertion, access, and maintenance bundles, and introduction of daily goal sheets on rounds that emphasized timely central venous line removal. Central line-associated bloodstream infection rates in the preintervention, partial intervention, and full intervention (April 2006 to December 2006) periods were compared.
Results:
The estimated mean preintervention central line-associated bloodstream infection rate was 7.8 infections per 1000 catheter-days, which decreased to 4.7 infections per 1000 catheter-days in the partial intervention period and 2.3 infections per 1000 catheter-days in the full intervention period. The preintervention central line-associated bloodstream infection rate was significantly higher than the median rate of 3.5 infections per 1000 catheter-days for multidisciplinary PICUs reporting to the National Healthcare Safety Network. During the full intervention period, our central line-associated bloodstream infection rate was lower than this pediatric benchmark, although statistical significance was not achieved.
Conclusions:
A multidisciplinary, evidence-based initiative resulted in a significant reduction in central line-associated bloodstream infections in our pediatric cardiac ICU.

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
Endocarditis IV: Nursing Management
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:27
Nursing Clinical Information System
A Nursing Clinical Information System (NCIS) is a specialized type of healthcare information system tailored to meet the unique needs of nursing practice. It incorporates the principles of nursing informatics to streamline information management and improve the quality of care delivery.
Critical attributes of NCIS include:
 01:26
Cardiac Catheterization IV: Nursing Management