Related Experiment Video
Updated: Jul 5, 2026

06:47

Microfluidics in Assessing Platelet Function
Published on: November 8, 2024
Plasma clopidogrel metabolites and antiplatelet "resistance": back to the future
Thrombosis Research
|May 3, 2008

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Antiplatelet drugs emerge as frontline defenders against the insidious threat of thromboembolic diseases, where abnormal clots obstruct vital blood vessels. These drugs stand as bulwarks, inhibiting platelet aggregation and clot formation, thereby mitigating the risk of life-threatening conditions like myocardial infarction, coronary artery disease, and thrombotic strokes.
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
Genetic variations significantly influence drug response through pharmacokinetics, receptor interactions, and biologic milieu modifications. Pharmacokinetic alterations impact drug metabolism and clearance, affecting efficacy and toxicity. Variants in drug-metabolizing enzymes, such as CYP2C9 and CYP2C19, alter drug activation and elimination. For example, CYP2C9 loss-of-function variants require lower warfarin doses to prevent excessive bleeding, while CYP2C19 variants reduce clopidogrel...
 01:27
Pharmacogenetics of Drug Metabolism: Overview
Genetic polymorphism in drug metabolism is crucial to the inter-individual variability observed in drug responses. Drug metabolism primarily involves the chemical modification of drugs and other xenobiotics to enhance their elimination by increasing their polarity. Two main classes of enzymes mediate this biotransformation process: Phase I enzymes, primarily cytochrome P450s, catalyze oxidation and reduction reactions, while other enzymes, such as esterases, mediate hydrolysis, and Phase II...
 01:29
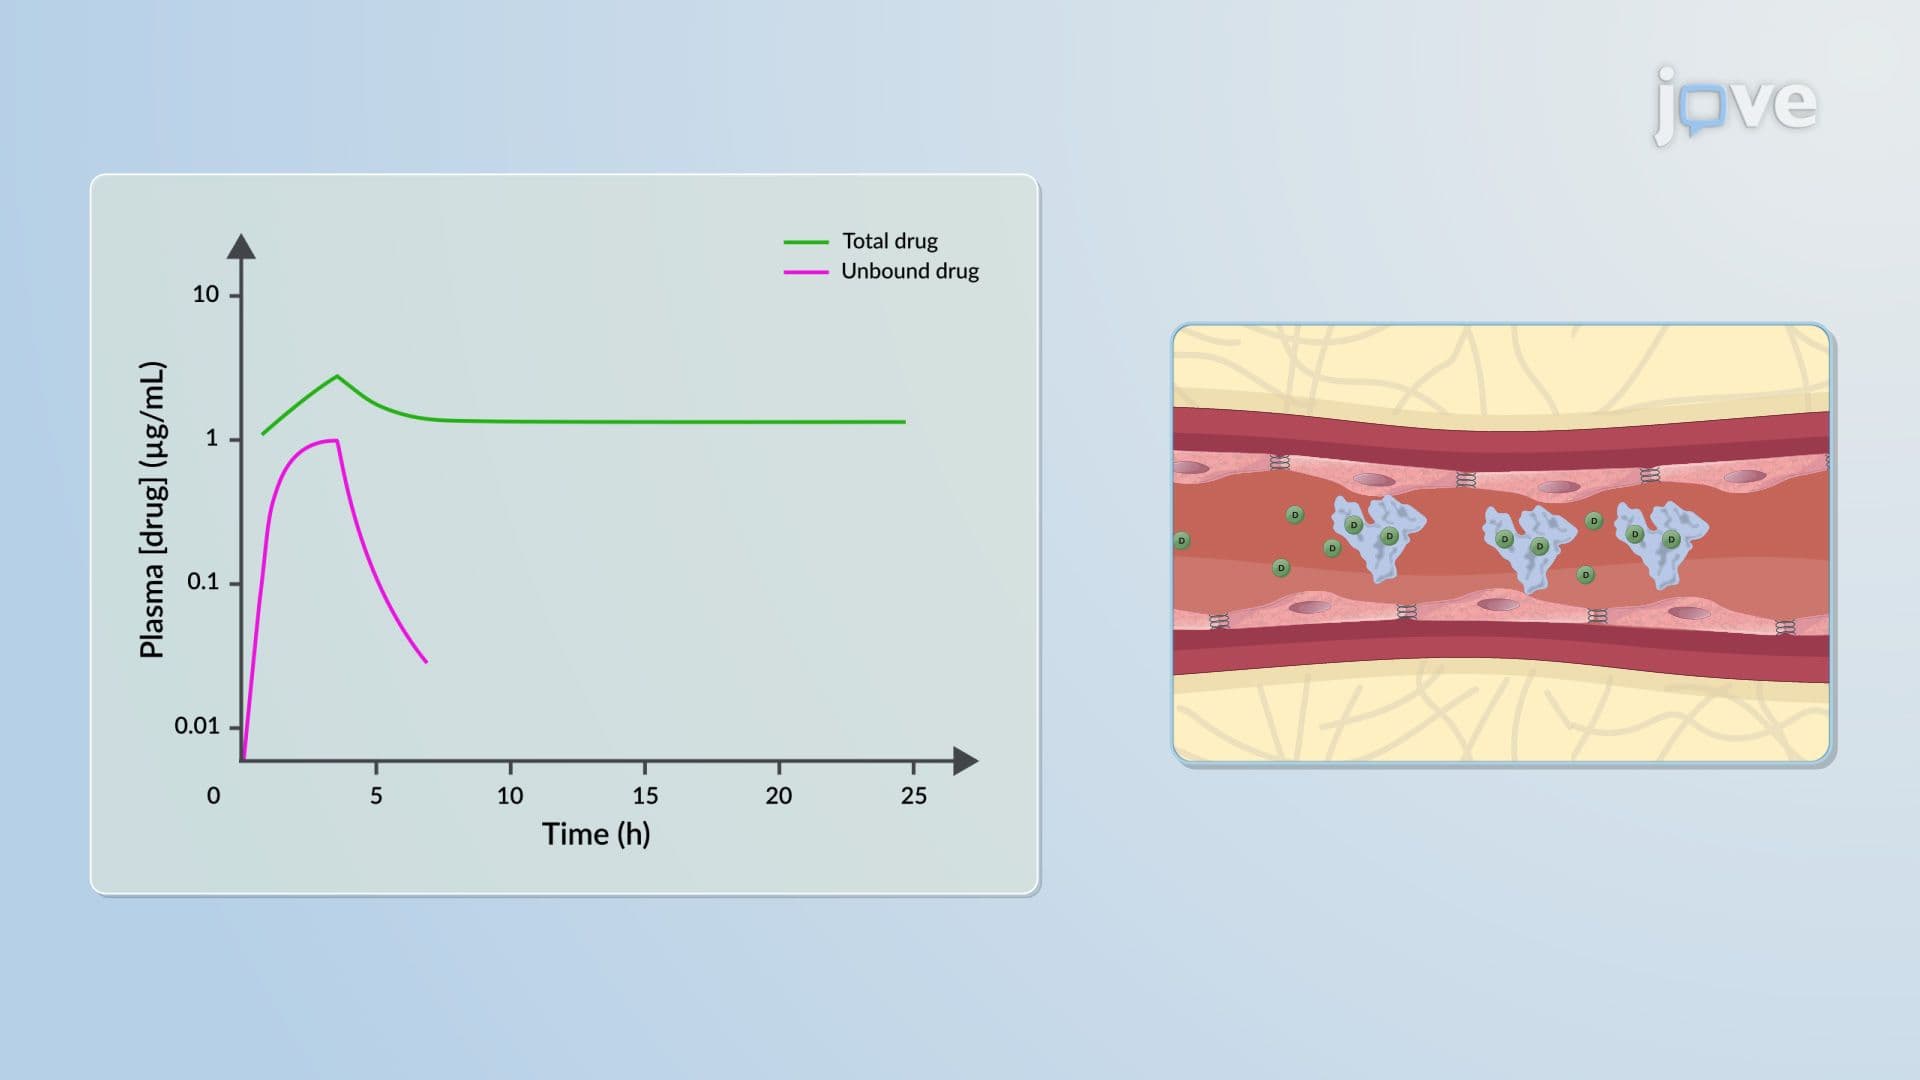
Drug Distribution: Plasma Protein Binding
Drugs predominantly attach to plasma proteins, with only a small percentage remaining unbound. The unbound portion can be calculated as one minus the bound fraction. Acidic drugs form large, inactive complexes by reversibly binding to plasma albumin, which prevents them from diffusing across biological barriers. These drug-protein complexes act as reservoirs for the drugs. As the concentration of unbound drugs decreases, these complexes quickly dissociate to release the free drug, maintaining...
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
Drug transporters are critical in drug absorption, distribution, and excretion processes. They should be included in physiological-based pharmacokinetic (PBPK) models, which help predict human drug disposition. However, predicting this is challenging during drug development, especially when liver transport is involved. However, with a realistic representation of body transport processes, an accurate model may be possible.
A recent model describes pravastatin's hepatobiliary excretion, mediated...
A recent model describes pravastatin's hepatobiliary excretion, mediated...
 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
The empirical approach to drug therapy optimization relies on correlating pharmacological response with administered dosage. Such an approach can be costly, time-consuming, and often yields poor correlation due to variables like formulation factors and drug elimination characteristics. A more precise approach correlates response with plasma drug concentration or the amount of drug in the body, rather than dosage. This is achieved through pharmacokinetic-pharmacodynamic (PK/PD) modeling, which...