Related Experiment Video
Updated: Jul 5, 2026
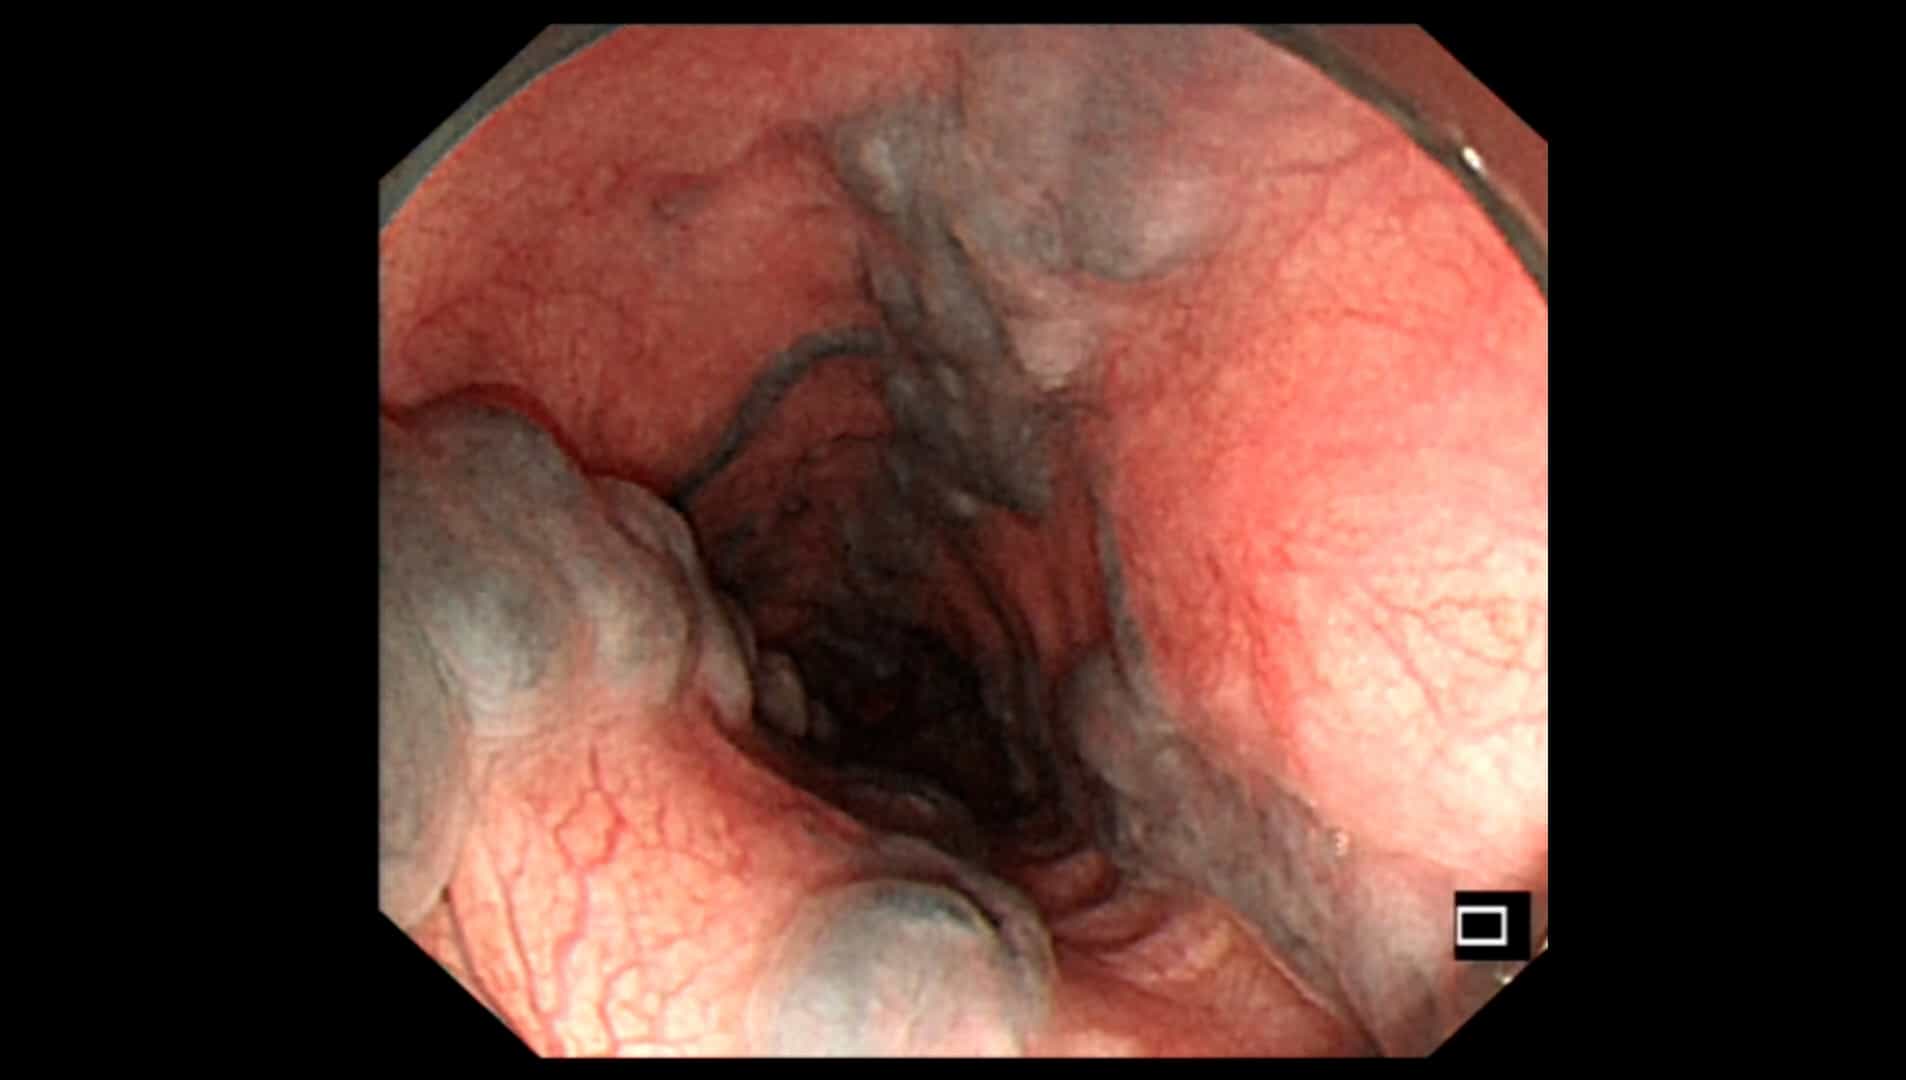

Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
Primary prophylaxis of esophageal variceal bleeding in cirrhosis
P Bellot1, J C García-Pagán, J G Abraldes
1Hepatic Hemodynamic Laboratory and Centro de Investigación Biomédica en Red de Enfermedades Hepáticas y Digestivas (Ciberehd), Liver Unit, IMD, Hospital Clinic, IDIBAPS, University of Barcelona, C. Villarroel 170, 08036 Barcelona, Spain.

Abstract:
Variceal bleeding is a common and severe complication of liver cirrhosis. The risk of bleeding increases with the size of varices, red wheal marks and disease severity. Noninvasive tests are not accurate enough for the diagnosis of varices, so all patients with cirrhosis should be screened by endoscopy. Nonselective beta-blockers (propranolol, nadolol) are indicated for primary prophylaxis in patients with medium/large varices, and for those with small varices and red signs or advanced liver failure (Child C). In such patients, beta-blockers have been shown to reduce the risk of bleeding from 25 to 15%. There is no evidence to support using beta-blockers with nitrates or spironolactone. In patients with contraindication or intolerance to beta-blockers, endoscopic band ligations are indicated.


Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:22
Portal Hypertension
 01:29
Venous Thrombosis III: Interprofessional Care