Related Experiment Video
Updated: Jul 5, 2026
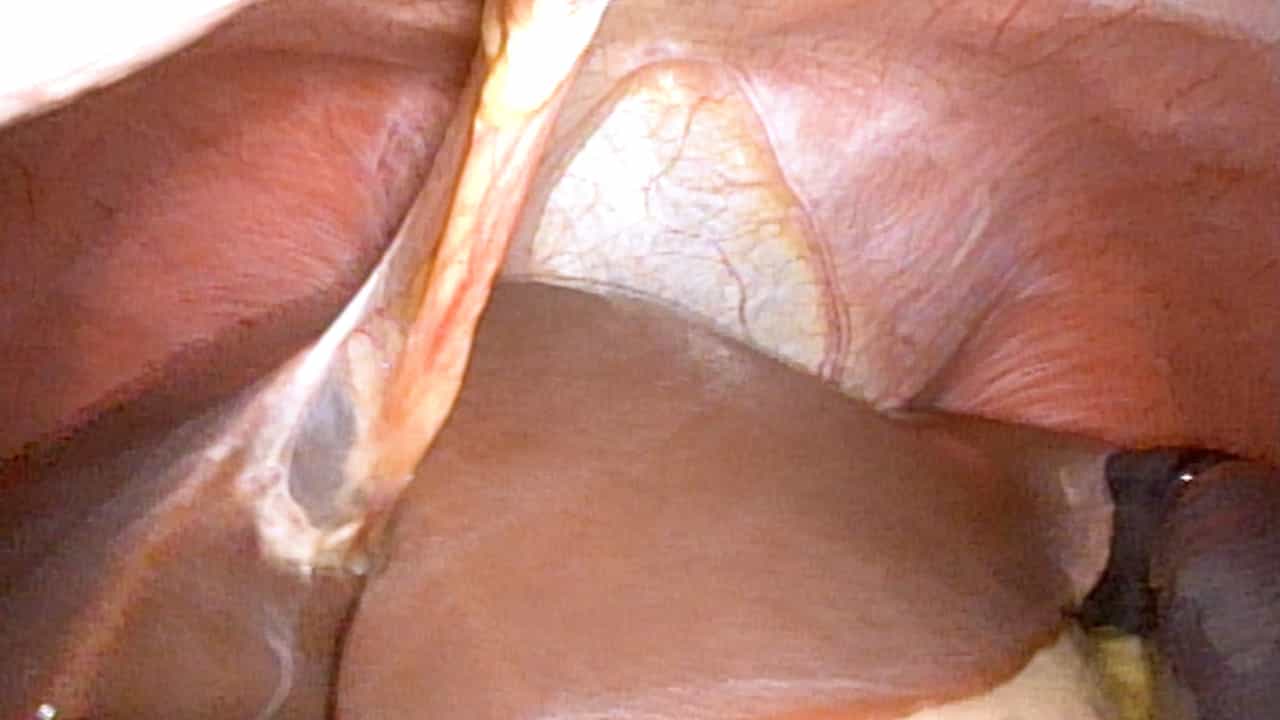

Robot-Assisted Laparoscopic Splenectomy In Children: A Case Report with Literature Review
Published on: March 27, 2026
Acute chest syndrome after splenectomy in children with sickle cell disease
Salim Ghantous1, Saad Al Mulhim, Nafeesa Al Faris
1Saudi Aramco Medical Services Organization, Dhahran 31311, Saudi Arabia.

Background/Purpose:
The purpose of this study was to determine the incidence of acute chest syndrome (ACS) in children with sickle cell disease (SCD) undergoing laparoscopic or open splenectomy and to assess factors that may predispose to this complication.
Methods:
A retrospective review of all patients with SCD undergoing splenectomy between 1999 and 2007 in our institution. Charts were screened for demographics, perioperative clinical status (vaso-occlusive crises, sequestration crises), preoperative hemoglobin electrophoresis and preoperative transfusion, postoperative development of ACS, and need for an intensive care unit (ICU) admission.
Results:
Forty-three children with SCD, 17 females and 16 males (mean age 9 years), underwent splenectomy (19 laparoscopy and 24 open). Acute chest syndrome occurred in 9 patients (20%), 1 (5.2%) of 19 in the laparoscopy group, and 8 (33.3%) of the 24 in the open group. All patients with ACS were admitted to the ICU. Acute chest syndrome developed within the first 24 hours in 5 of the 9 patients, on the second postoperative day in 1 patient, and more than 1 month postoperatively in 3 patients. Six of 9 patients with ACS had been transfused preoperatively. All patients with ACS had had vaso-occlusive crises before surgery. Five of 9 patients who developed ACS had previous ACS episodes before surgery. There was no death in our series.
Conclusion:
The incidence of ACS is in accordance with the literature. Preoperative transfusions did not prevent ACS. There is a clear tendency for laparoscopically operated patients to experience less ACS postoperatively. In our group of patients, there were no clear benefits for routine perioperative admission to the ICU.
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations