Related Experiment Video
Updated: Jul 5, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Levator trauma is associated with pelvic organ prolapse
1Department of Obstetrics and Gynaecology, Nepean Clinical School, University of Sydney, Nepean Hospital, Penrith, New South Wales, Australia. hpdietz@bigpond.com

Objective:
To estimate the risk of prolapse associated with levator avulsion injury among a urogynaecological clinic population.
Design:
Retrospective observational study.
Setting:
Tertiary urogynaecological unit.
Sample:
A total of 934 women seen for interview, examination using the pelvic organ prolapse quantification (POP-Q) staging system and imaging of the levator ani muscle by four-dimensional translabial ultrasound.
Methods:
Retrospective review of charts and stored imaging data.
Main Outcome Measures:
Pelvic organ prolapse stage II and higher and presence of defects of the levator ani muscle.
Results:
After exclusion of 137 women with a history of anti-incontinence or prolapse surgery, and a further exclusion of 16 women in whom either examination or imaging was impossible, we compared prolapse and imaging data in 781 women. Mean age was 53 years (range 15-89 years), and median parity was 2 (range 0-12). Women reported stress incontinence (76%), urge incontinence (69%), frequency (47%), nocturia (49%) and symptoms of prolapse (38%). Significant prolapse (stage II or higher) was diagnosed in 415 (53%) women, and 181 (23%) women were found to have levator avulsion defects. Prolapse was seen in 150/181 (83%) women with avulsion and in 265/600 (44%) women without avulsion, giving a relative risk (RR) of 1.9 (95% CI 1.7-2.1). The association was strongest for cystocele (RR 2.3, 95% CI 2.0-2.7) and uterine prolapse (RR 4.0, 95% CI 2.5-6.5).
Conclusions:
Women with levator avulsion defects were about twice as likely to show pelvic organ prolapse of stage II or higher than those without. This effect is mainly due to an increased risk of cystocele and uterine prolapse.

Related Concept Videos
 01:29
Herniated Intervertebral Disc l: Introduction
 01:26
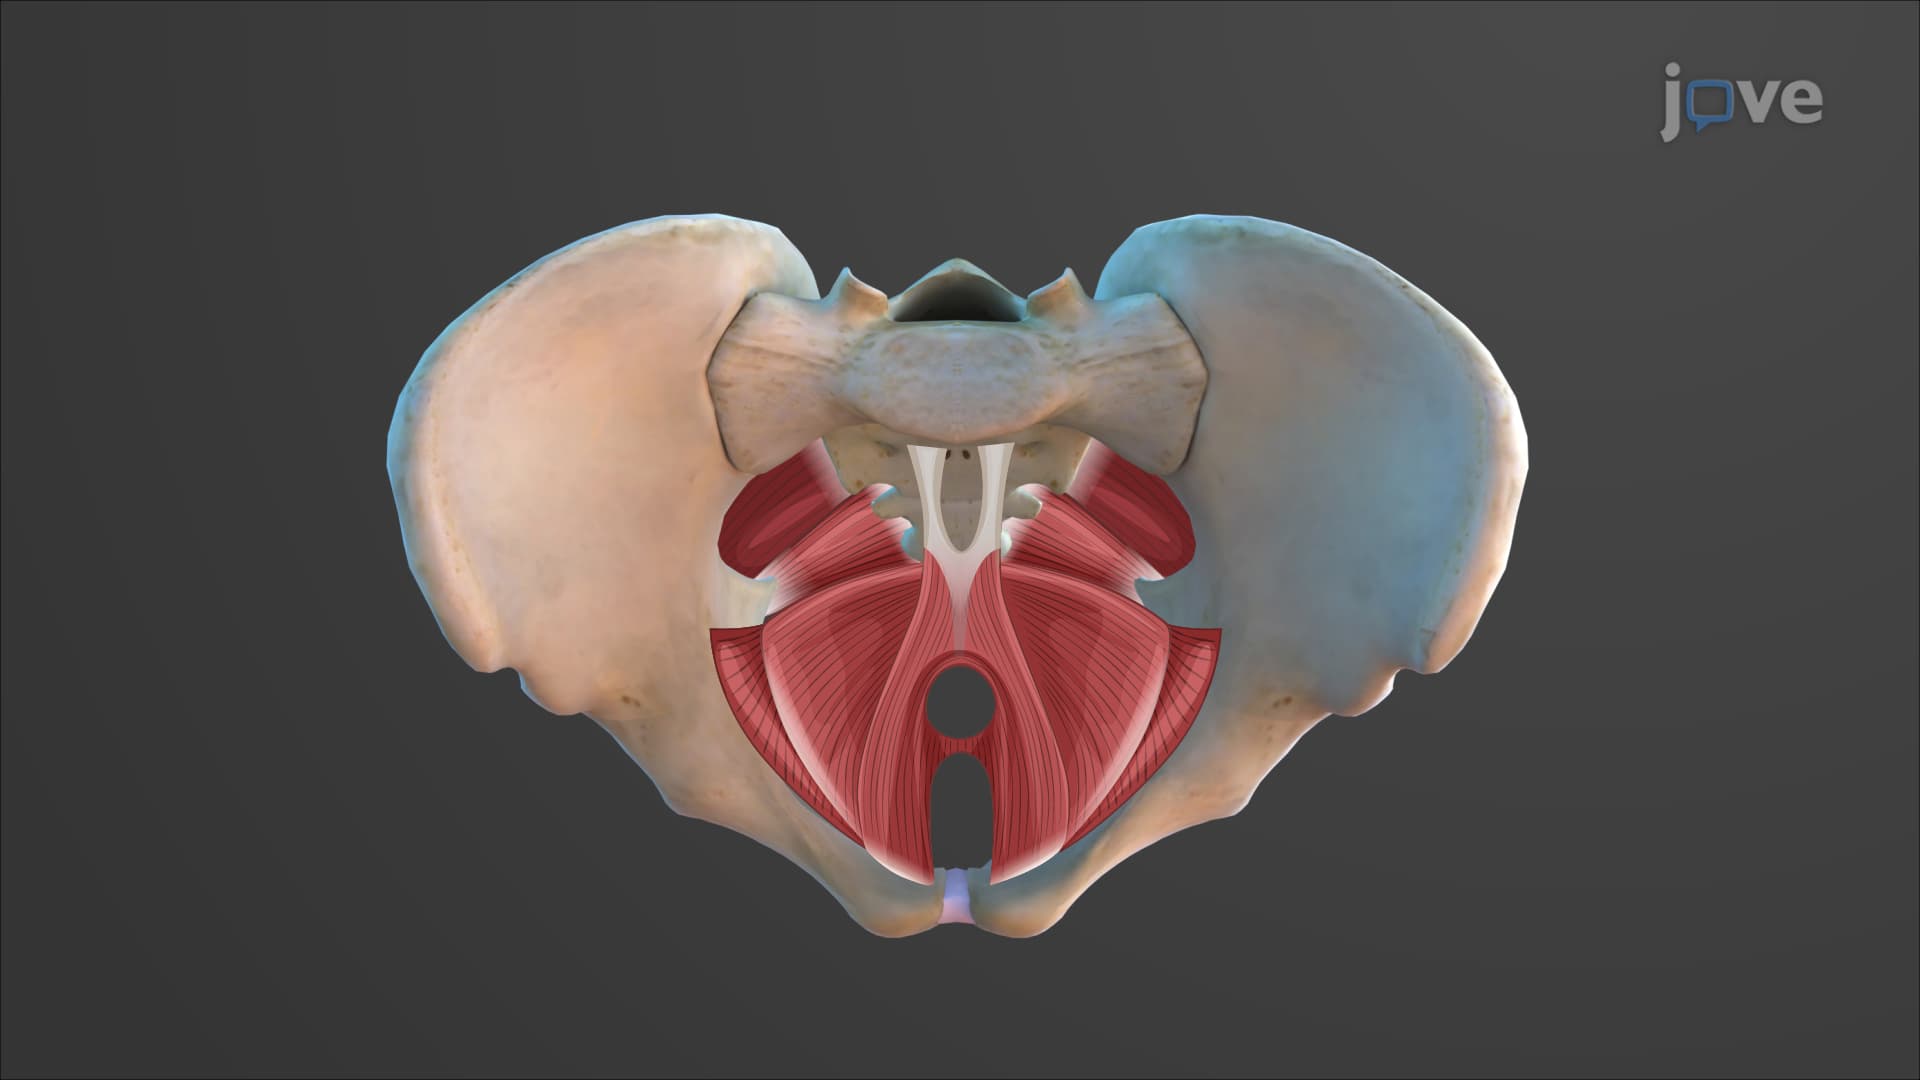
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:28
Traumatic Brain Injury l: Introduction
 01:25
Hiatal Hernia
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.