Related Experiment Video
Updated: Jul 4, 2026

Chemotherapy-induced Vascular Toxicity - Real-time In vivo Imaging of Vessel Impairment
Published on: January 7, 2015
[Chemotherapy and renal toxicity]
Vincent Launay-Vacher1, Corinne Isnard-Bagnis, Nicolas Janus
1Service de néphrologie, hôpital de la Pitié-Salpêtrière, 83, boulevard de l'Hôpital, 75013 Paris, France. vincent.launay-vacher@psl.aphp.fr

Abstract:
Antineoplastic drugs used in the treatment of cancers present with variable renal tolerance profiles. Among drugs with a potential for renal toxicity, platinum salts, methotrexate, and gemcitabine are well-known. The mechanisms of their renal toxicity and the means of its prevention are presented in this article. Anti-angiogenic drugs, recently marketed or still under clinical development, may also interact with the kidneys. In general, optimising the renal tolerance of anticancer drugs requires an appropriate evaluation of patients'renal function, before and during treatment, at each course. Serum creatinine alone is not a reliable index of renal function. Its evaluation must be performed with the use of Cockcroft-Gault or aMDRD formulae. In patients with abnormal renal function, dosage adjustment is often required to improve the renal tolerance, and also to limit the risk of extra-renal toxicities (such as haematological toxicities) induced by a drug overdosage, in those patients with reduced drug-elimination.
Insights
Antineoplastic drugs can harm kidneys. Monitoring renal function using formulas like Cockcroft-Gault and adjusting dosages prevents anticancer drug toxicity.
Area of Science:
- Nephrology
- Oncology
- Pharmacology
Background:
- Antineoplastic drugs are crucial for cancer treatment but exhibit varied renal tolerance.
- Several chemotherapy agents, including platinum salts, methotrexate, and gemcitabine, are known for potential kidney toxicity.
- Emerging anti-angiogenic drugs also pose risks to renal function.
Purpose of the Study:
- To review the mechanisms of renal toxicity associated with common antineoplastic drugs.
- To outline strategies for preventing kidney damage during cancer therapy.
- To emphasize the importance of accurate renal function assessment for optimizing drug tolerance.
Main Methods:
- Review of literature on anticancer drug-induced nephrotoxicity.
- Discussion of mechanisms of renal damage.
- Presentation of methods for renal function evaluation and dosage adjustment.
Main Results:
- Serum creatinine is an unreliable marker for renal function assessment.
- Formulas such as Cockcroft-Gault or aMDRD are recommended for accurate renal function evaluation.
- Dosage adjustments in patients with impaired renal function are critical for improving tolerance and preventing toxicity.
Conclusions:
- Optimizing renal tolerance to antineoplastic drugs necessitates regular renal function monitoring before and during treatment.
- Accurate renal function assessment using appropriate formulas is essential.
- Dosage modification in patients with renal impairment reduces the risk of both renal and extra-renal toxicities.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 01:15
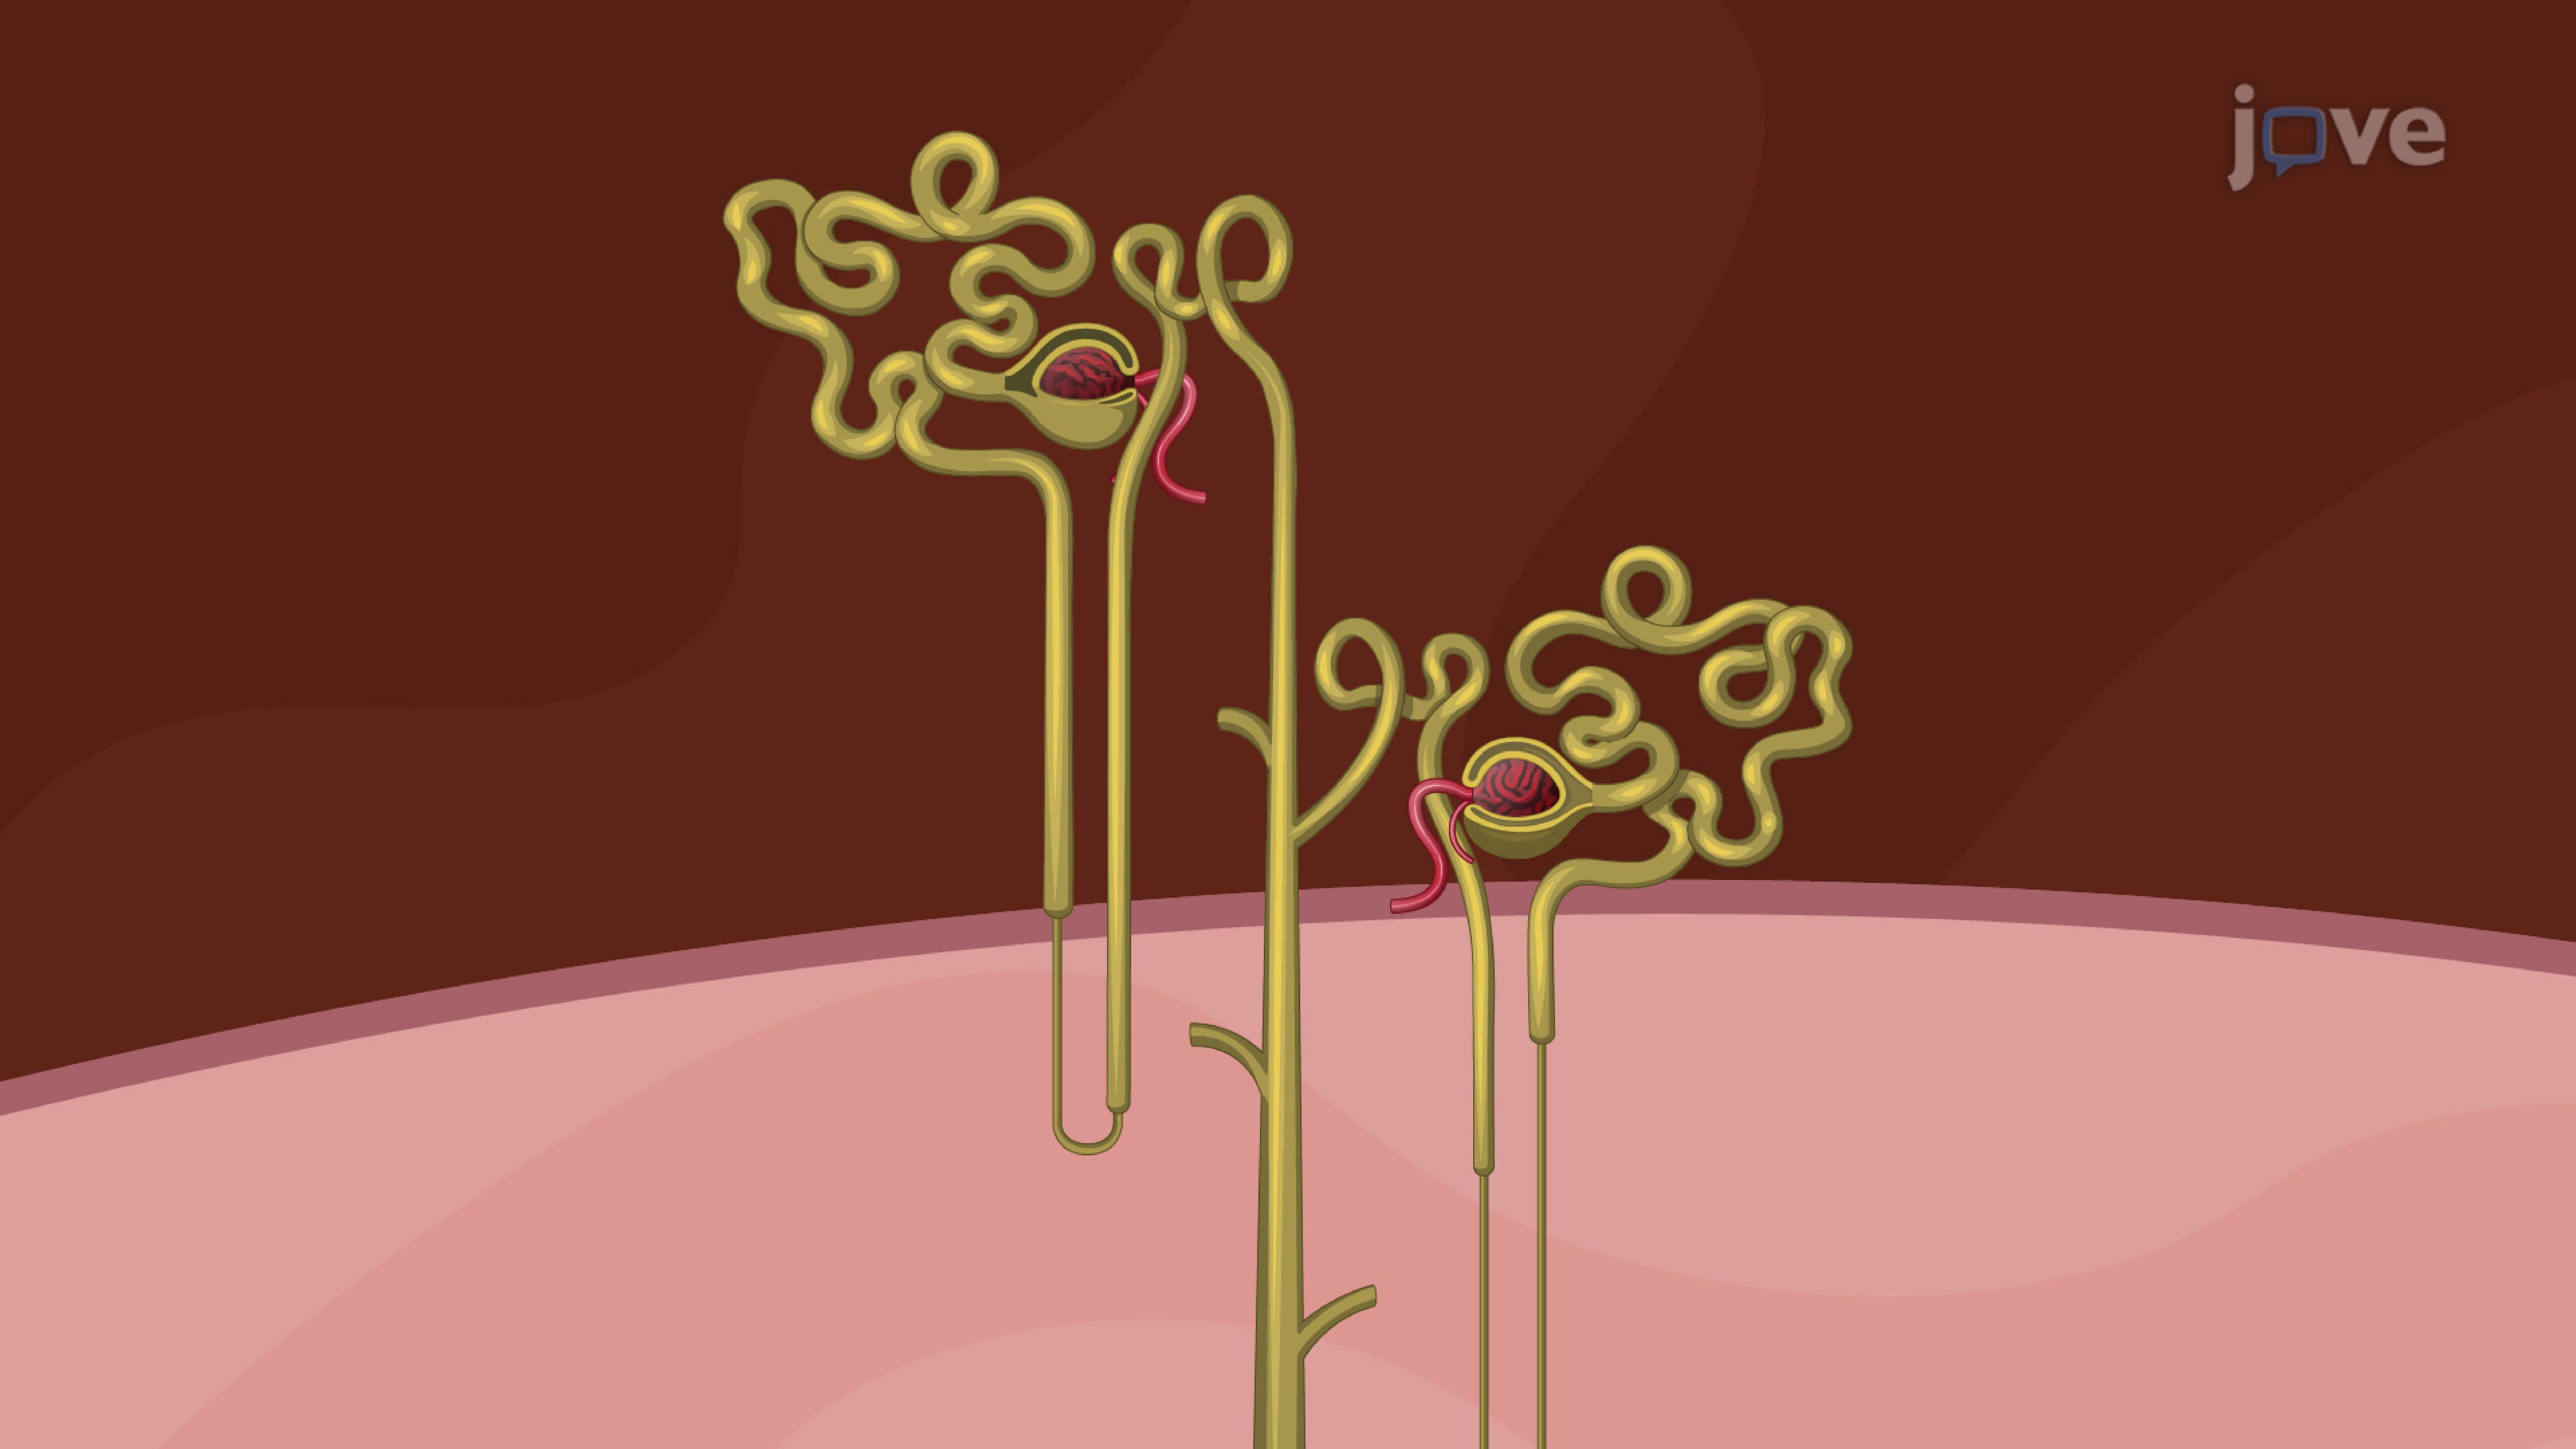
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:30
Drug toxicity: Drug–Drug Interaction