Related Experiment Video
Updated: Jul 4, 2026
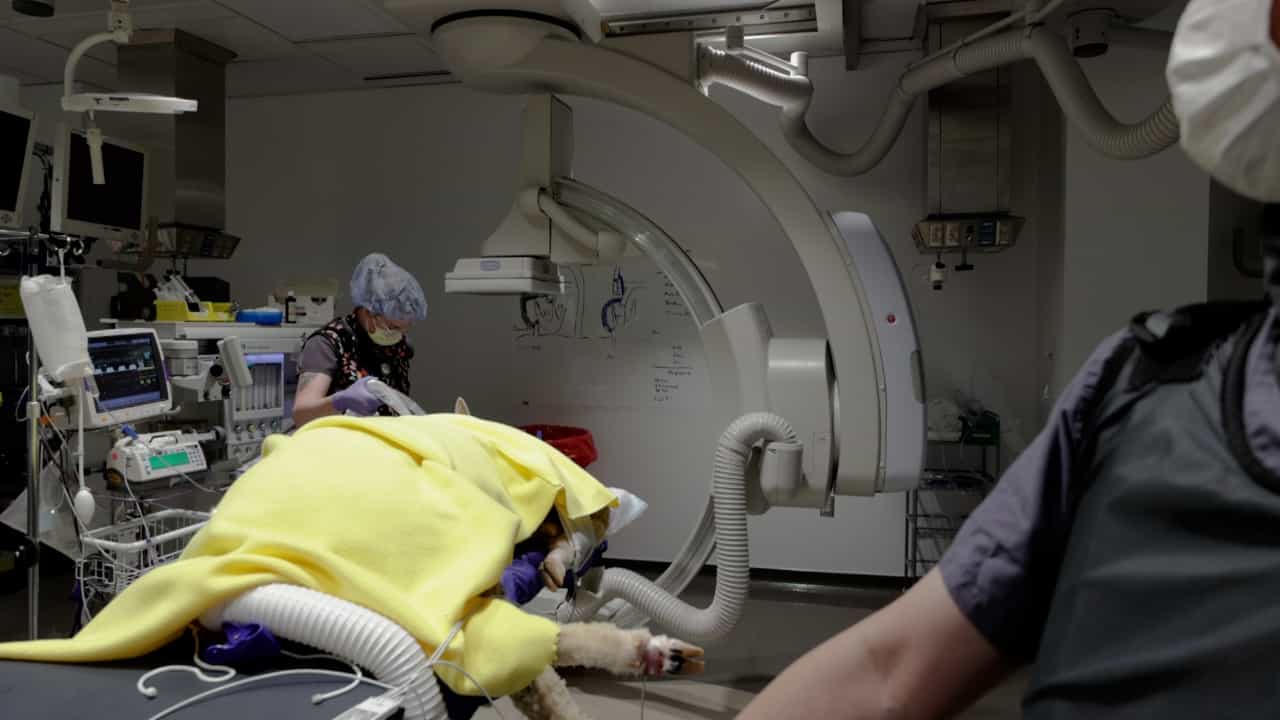
Quantifying Inferior Vena Cava Compliance and Distensibility in an In Vivo Ovine Model Using 3D Angiography
Published on: April 26, 2024
Evaluation of wall motion and dynamic geometry of the inferior vena cava using intravascular ultrasound: implications
Erin H Murphy1, Eric D Johnson, Frank R Arko
1Division of Vascular and Endovascular Surgery, University of Texas Southwestern Medical Center, Dallas, TX 75903, USA.

Purpose:
To use intravascular ultrasound (IVUS) to define the wall motion of the inferior vena cava (IVC) during normal respiratory cycles and evaluate its dynamic geometry during Valsalva maneuvers.
Methods:
Between September 2005 and October 2006, 10 patients who were having IVC filters placed underwent IVUS prior to filter implantation. With the anesthetized patient in a supine position, a 10-second IVUS recording of IVC motion below the renal veins was made during both normal respiratory cycles and Valsalva maneuvers. Diameters (n = 100 measurements) were measured from the epicenter of the lumen in both a long and short axis. Changes in diameters were evaluated using a Student t test for paired data; variations in IVC wall motion circumference of the vessel were compared using an analysis of variance for repeated measurements. Intra-/interobserver variability was analyzed with Bland-Altman plots.
Results:
The mean IVC diameter was 14.3+/-4.1 mm in the short axis and 23.2+/-3.5 mm in the long axis. There was significant variation in infrarenal IVC wall movement about the circumference, with 1.4+/-0.2 mm (range 0.6-1.8) displacement in the short axis and 1.0+/-0.2 mm (range 0.2-1.4) displacement in the long axis during the normal respiratory cycle (p = 0.04). In the short axis, the IVC diameter significantly increased with Valsalva from 14.3+/-4.1 to 19.6+/-1.2 mm (p = 0.0001); in the long axis, the diameter increased from 23.2+/-3.5 to 24+/-1.2 mm (p = 0.02). With Valsalva, there was a significantly greater change in the short axis (30.9%+/-4.8%) compared to the long axis (3.4%+/-2.2%; p = 0.0001). There were no significant differences in the interobserver and intraobserver measurements.
Conclusion:
In the supine position, the IVC is elliptical and deforms anisotropically during the normal respiratory cycle. The greatest displacement (36%) is in the short axis during a Valsalva maneuver. These profound changes within the venous system will require intracaval devices to have active fixation to prevent migration. Devices should be designed to accommodate these changes to prevent fatigue failure.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for diagnosing...