Related Experiment Video
Updated: Jul 4, 2026
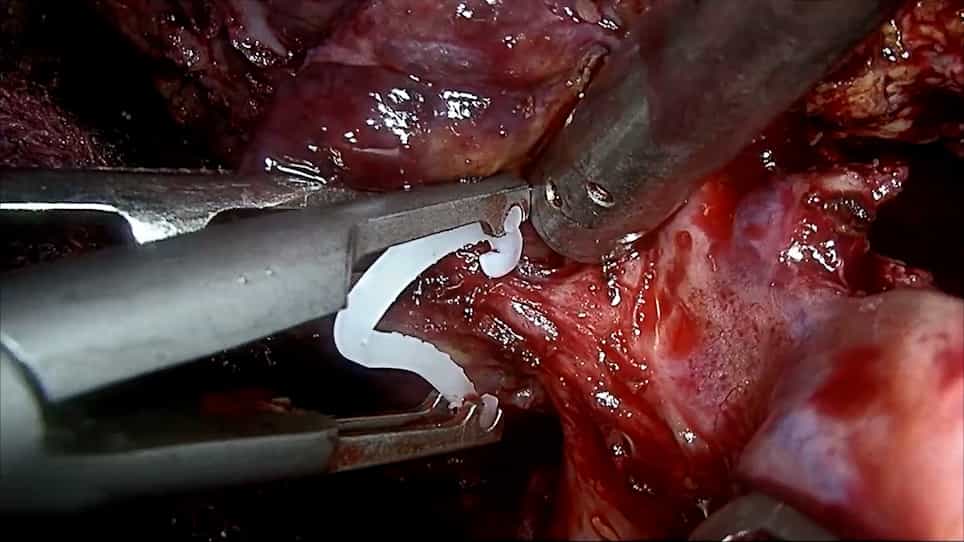

Modified Laparoscopic Anatomic Hepatectomy: Two-Surgeon Technique Combined with the Simple Extracorporeal Pringle Maneuver
Published on: June 16, 2023
Intermittent Pringle manoeuvre is not associated with adverse long-term prognosis after resection for colorectal
K H V Wong1, Z Z R Hamady, H Z Malik
1Hepatopancreatobiliary and Transplant Unit, St James's University Hospital, Leeds LS9 7TF, UK.

Background:
Intermittent clamping of the porta hepatis, or the intermittent Pringle manoeuvre (IPM), is often used to control inflow during parenchymal liver transection. The aim of this study was to determine whether IPM is associated with an adverse long-term outcome after liver resection for colorectal liver metastasis (CRLM).
Methods:
All patients undergoing resection for CRLM in 1993-2006, for whom data on IPM were recorded, were included in the study. A total of 563 patients was available for analysis.
Results:
IPM was performed in 289 (51.3 per cent) of the patients. The duration of IPM ranged from 2 to 104 (median 22) min. There were no differences in clinicopathological features or postoperative morbidity between patients who had an IPM and those who did not. The median survival of patients undergoing IPM was 55.7 months compared with 48.9 months in those not having an IPM (P = 0.406). There was no difference in median disease-free survival between the two groups (22.1 versus 19.9 months respectively; P = 0.199).
Conclusion:
IPM is not associated with an adverse long-term prognosis in patients undergoing liver resection for CRLM.
Insights
The intermittent Pringle manoeuvre (IPM) is a common technique during liver resection for colorectal liver metastasis (CRLM). This study found IPM does not negatively impact long-term survival or disease-free survival in CRLM patients.
Area of Science:
- Hepatobiliary Surgery
- Surgical Oncology
- Gastroenterology
Background:
- Intermittent clamping of the porta hepatis, or the intermittent Pringle manoeuvre (IPM), is utilized to manage inflow during liver transection.
- The safety and long-term effects of IPM in liver resection for colorectal liver metastasis (CRLM) require investigation.
Purpose of the Study:
- To evaluate the association between the intermittent Pringle manoeuvre (IPM) and long-term outcomes in patients undergoing liver resection for colorectal liver metastasis (CRLM).
Main Methods:
- Retrospective analysis of 563 patients who underwent liver resection for CRLM between 1993 and 2006.
- Data on the use and duration of IPM were recorded and analyzed.
- Comparison of clinicopathological features, postoperative morbidity, median survival, and median disease-free survival between patients who underwent IPM and those who did not.
Main Results:
- IPM was performed in 51.3% of patients, with a median duration of 22 minutes.
- No significant differences were observed in clinicopathological features or postoperative morbidity between the IPM and non-IPM groups.
- Median survival was 55.7 months with IPM versus 48.9 months without (P=0.406); median disease-free survival was 22.1 months versus 19.9 months (P=0.199).
Conclusions:
- The intermittent Pringle manoeuvre (IPM) is not linked to adverse long-term prognosis in patients undergoing liver resection for colorectal liver metastasis (CRLM).
- IPM can be safely employed without compromising patient survival or disease recurrence rates in this patient population.
