Related Experiment Video
Updated: Jul 4, 2026
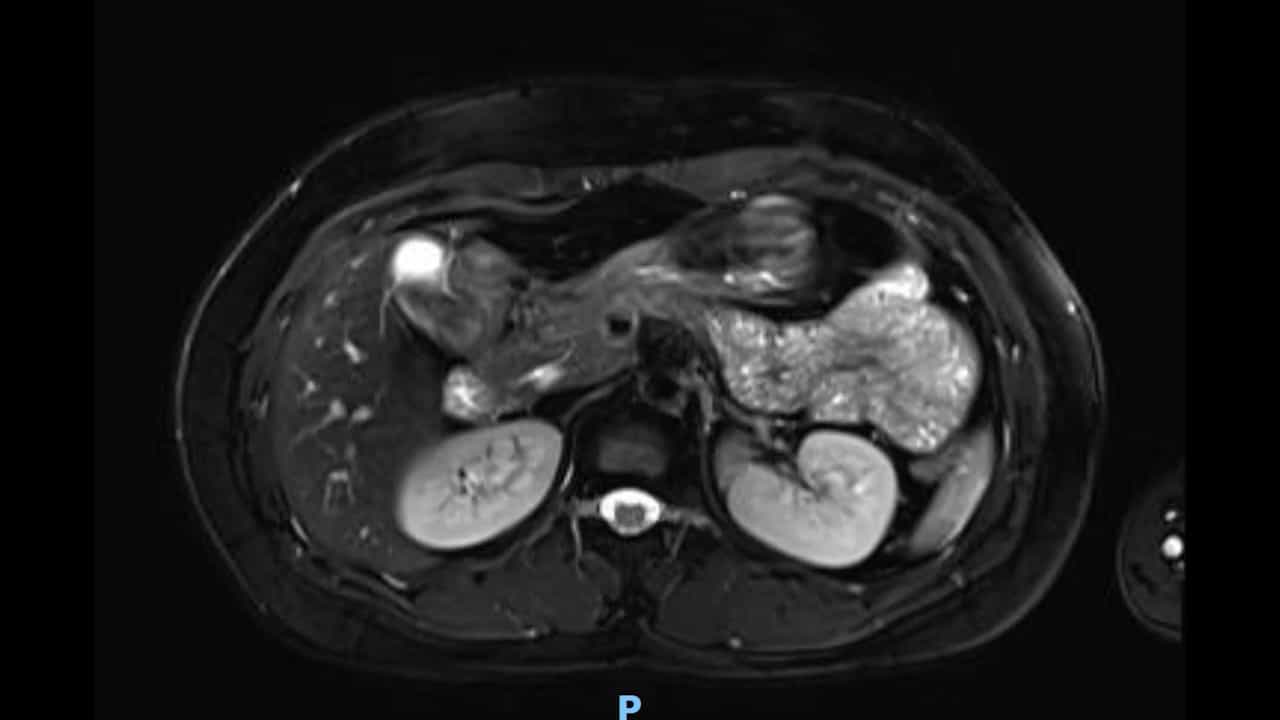

Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Spontaneous perforation of choledochal cyst and hyperemesis gravidarum
Philip Joseph1, Ravish Sanghi Raju, Frederick L Vyas
1Department of General Surgery Unit IV (Hepato-Biliary Pancreatic Surgery), Christian Medical College, Vellore, Tamil Nadu, India. sur4@cmcvellore.ac.in

A 28-year-old primigravida at seven weeks gestation presented to the Accident & Emergency Department complaining of vomiting for five days. She was admitted and managed as a case of hyperemesis gravidarum. Two days later she developed abdominal distension. Ultrasound scan revealed ascites and common bile duct dilatation. The ascitic fluid was bile stained. At emergency laparotomy spontaneous perforation of the supraduodenal part of the common bile duct was seen. This was closed around a T-tube. She then underwent medical termination of pregnancy. The post-operative T-tube cholangiogram was suggestive of a type I choledochal cyst. Three months later this was excised and biliary enteric continuity restored by performing a hepaticojejunostomy. To the best of our knowledge, spontaneous rupture of a choledochal cyst in a patient of hyperemesis gravidarum has not been reported before. In this article, we discuss treatment options for choledochal cyst during pregnancy.
A 28-year-old primigravida at seven weeks gestation presented to the Accident & Emergency Department complaining of vomiting for five days. She was admitted and managed as a case of hyperemesis gravidarum. Two days later she developed abdominal distension. Ultrasound scan revealed ascites and common bile duct dilatation. The ascitic fluid was bile stained. At emergency laparotomy spontaneous perforation of the supraduodenal part of the common bile duct was seen. This was closed around a T-tube. She then underwent medical termination of pregnancy. The post-operative T-tube cholangiogram was suggestive of a type I choledochal cyst. Three months later this was excised and biliary enteric continuity restored by performing a hepaticojejunostomy. To the best of our knowledge, spontaneous rupture of a choledochal cyst in a patient of hyperemesis gravidarum has not been reported before. In this article, we discuss treatment options for choledochal cyst during pregnancy.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:20
Cholecystitis
 01:25
Hiatal Hernia
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:07
Intestinal Obstruction II: Pathophysiology