Related Experiment Video
Updated: Jul 4, 2026


An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Rationale for low-dose systemic hormone replacement therapy and review of estradiol 0.5 mg/NETA 0.1 mg
Odd Erik Johansen1, Erik Qvigstad
1Medical Department, Asker and Baerum Hospital, PO Box 83, 1309, Rud, Norway. odd.erik.johansen@broadpark.no

Abstract:
The menopausal transition is associated with several symptoms, for which both non-pharmacological and pharmacological measures are available to provide relief. However, present knowledge indicates that the former is not highly effective, and that the latter, in terms of systemic oestrogen and progestogen-based hormone replacement therapy (HRT), although being effective (e.g. on vasomotor symptoms, bleeding control, bone mineral density, vaginal atrophy and quality of life), can be associated with some caveats. Amongst these are an increased risk for coronary heart disease, breast cancer, venous thromboembolism and stroke. In recent years, literature has indicated a dose dependency for HRT on some of the caveats, hence authorities (Food and Drug Administration, and the European Medicines Agency) and menopause societies (International Menopause Society and North American Menopause Society) now recommend that women deemed in need of HRT should receive the lowest possible dose without compromising the effect of symptom relief. Estradiol 0.5 mg/norethisterone acetate (NETA) 0.1 mg, despite being a lower dose than conventional hormones, is a compound, among a few other low-dose options, that can be used in such therapy. As a first-line oral option, it has demonstrated its effectiveness (which seems comparable to other compounds), with high tolerability and, apparently, no safety concerns, in a 6-month study. Further long-term clinical trials and observational studies are mandatory in order to capture any potential harm as well as to elucidate this compound's full potential. Following a thorough literature search using PubMed and MEDLINE from the earliest publication dates through to January 2008, including results from various types of clinical trials and statements on HRT, we review the rationale for these recommendations. We also review the effects and safety of a novel 'ultra-low-dose' oral continuous combined HRT tablet, estradiol 0.5 mg/NETA 0.1 mg.

Related Concept Videos
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Target Cell Response to Hormones
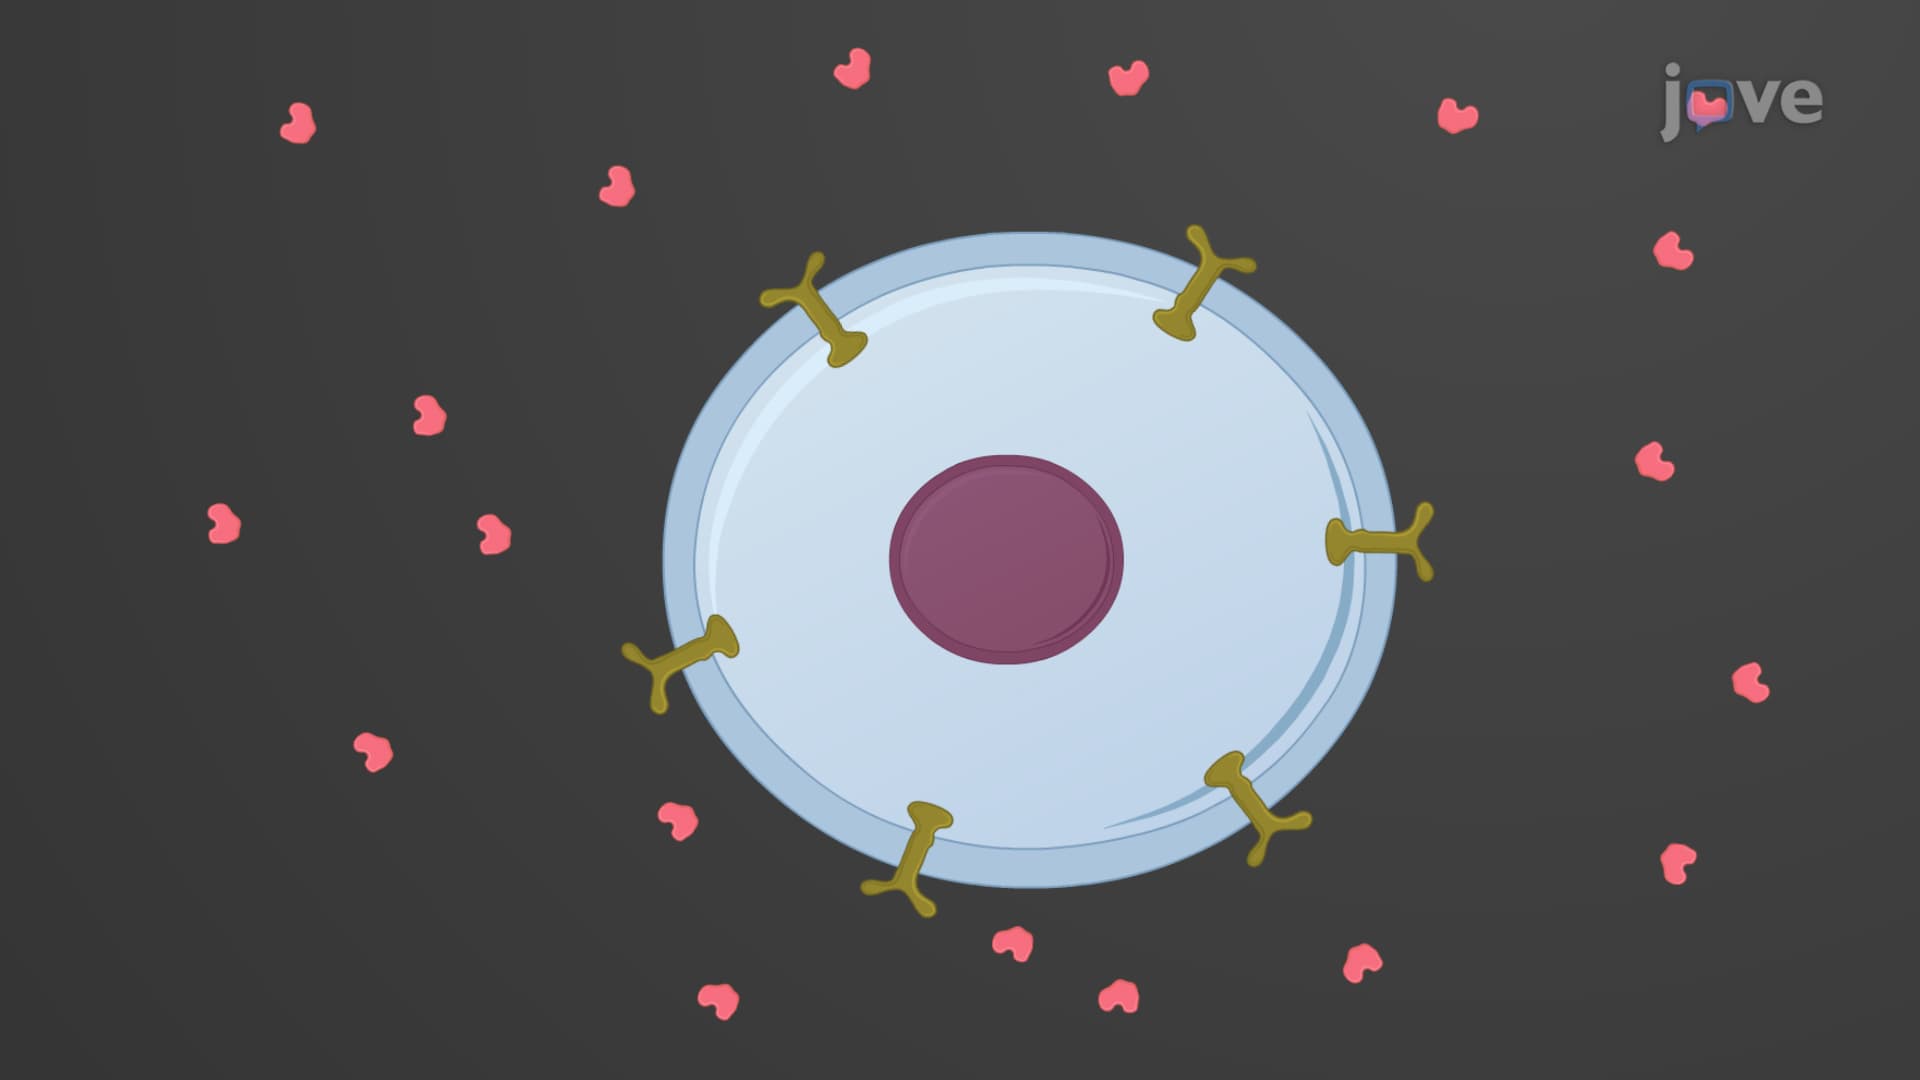
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:01
Dosage Regimen: Fixed Dose
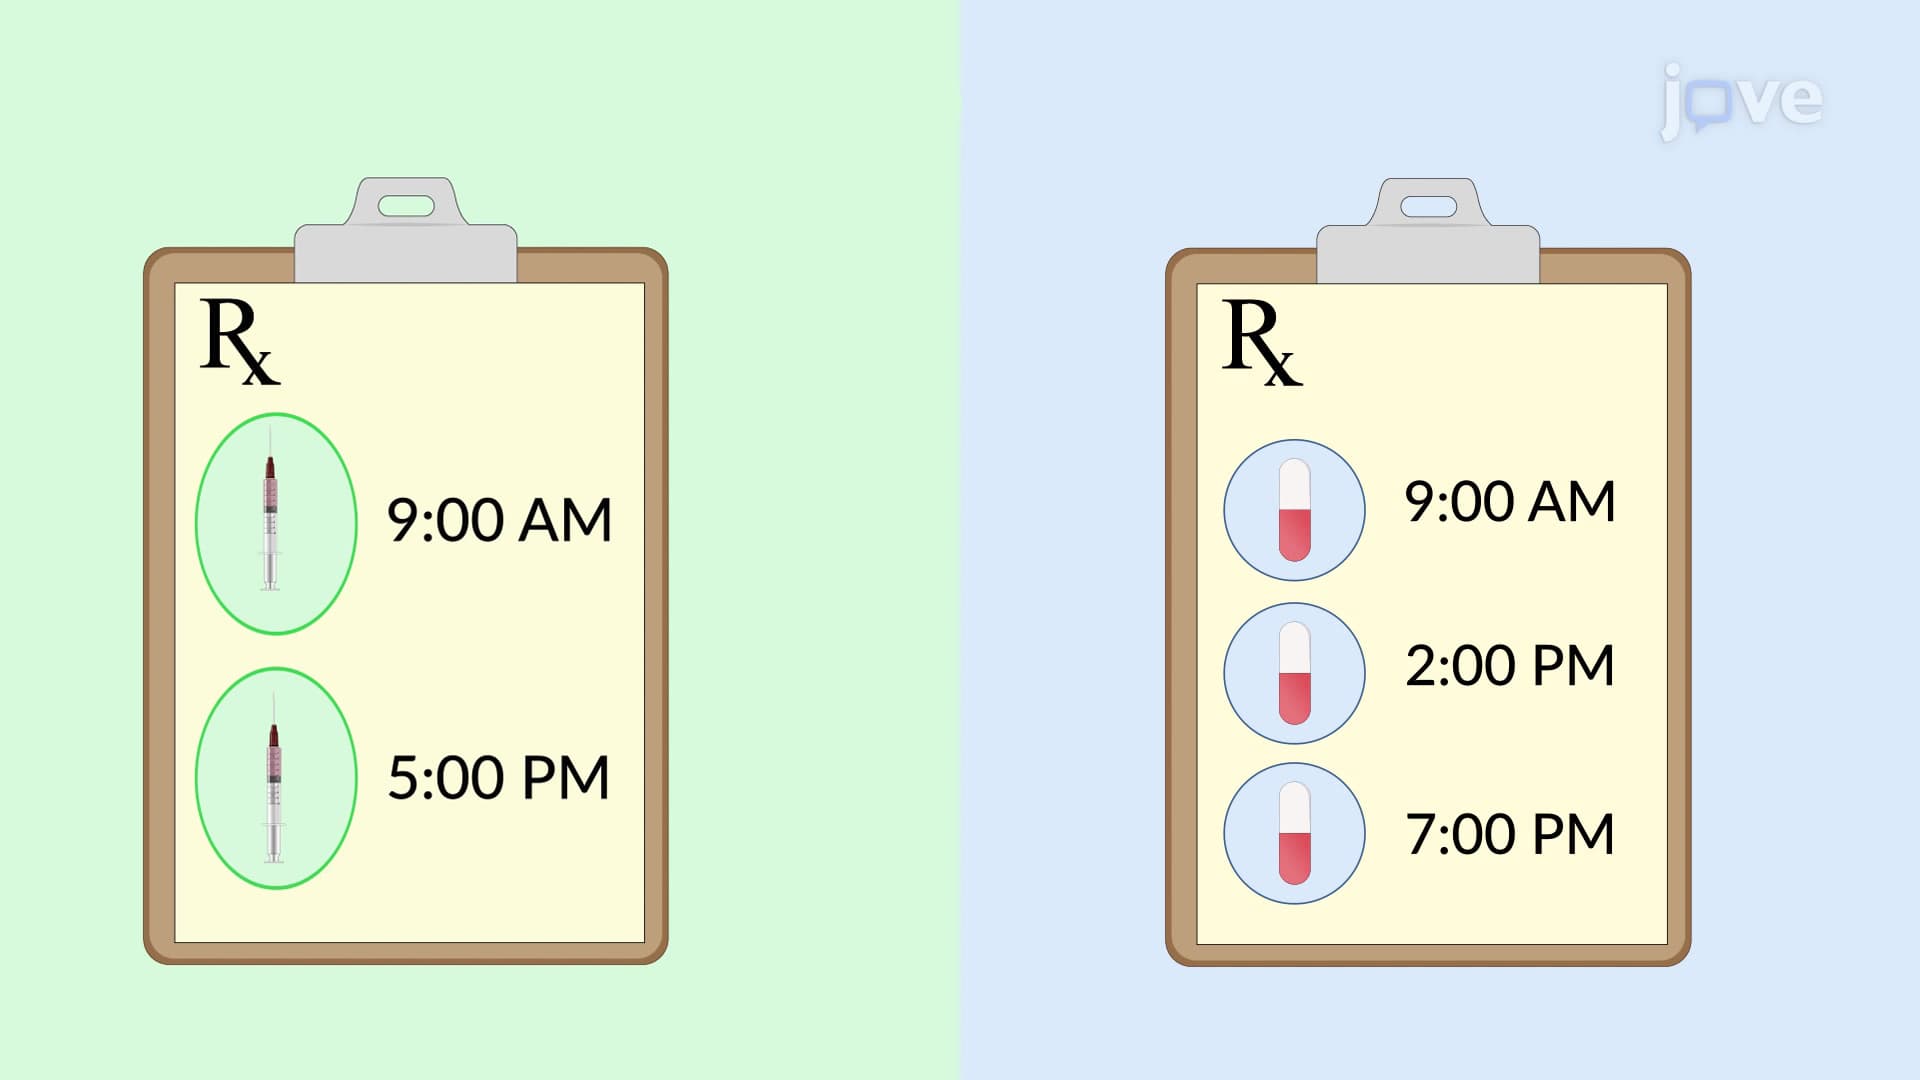
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:40
Hormonal Regulation