Related Experiment Video
Updated: Jul 4, 2026
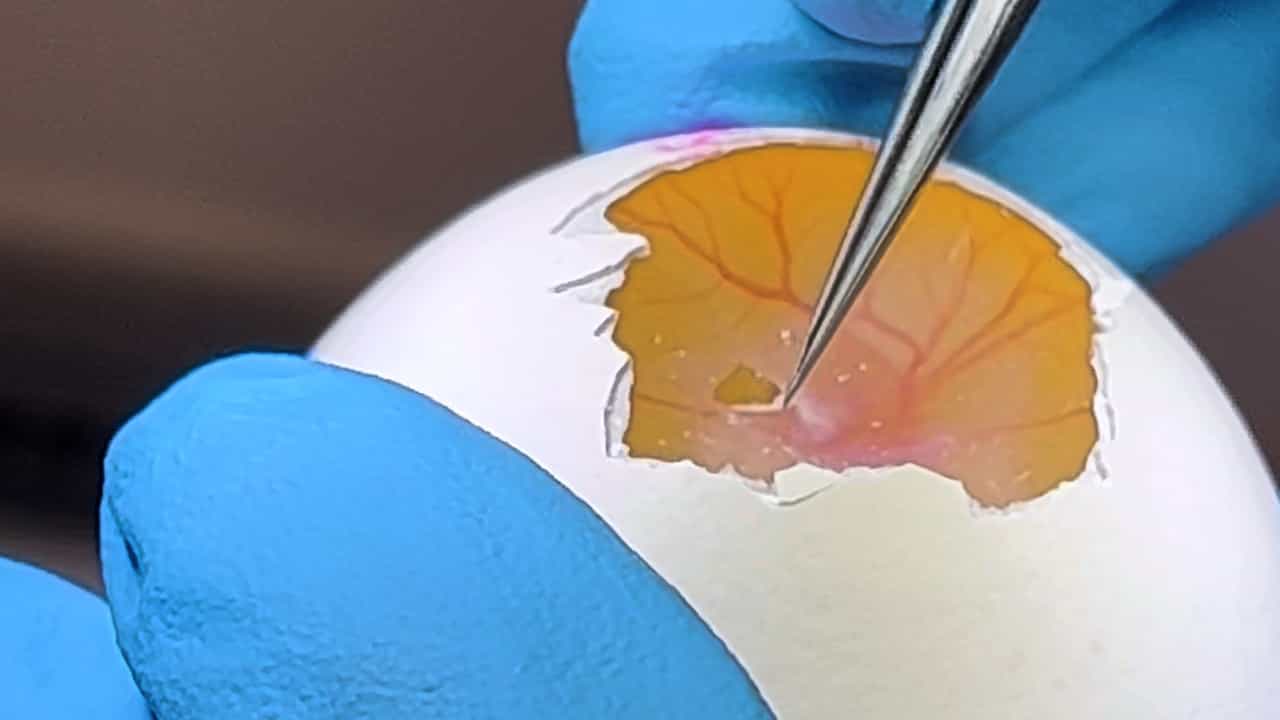
Left Atrial Ligation in the Avian Embryo as a Model for Altered Hemodynamic Loading During Early Vascular Development
Published on: June 16, 2023
Isolated congenital atrioventricular block diagnosed in utero: natural history and outcome
Johannes M P J Breur1, Livia Kapusta, Philip Stoutenbeek
1Department of Obstetrics, University Medical Center, Utrecht, the Netherlands. hans_breur@hotmail.com

Insights
Congenital atrioventricular block (CAVB) diagnosed in utero has high mortality, especially with fetal hydrops or heart rates below 50 bpm. Poor outcomes, including pacemaker implantation or dilated cardiomyopathy, are linked to fetal heart rates below 60 bpm.
Area of Science:
- Cardiology
- Fetal Medicine
- Pediatric Cardiology
Background:
- Isolated congenital atrioventricular block (CAVB) diagnosed in utero presents significant morbidity and mortality risks.
- Prognosis is particularly poor with fetal heart rates below 55 beats per minute (bpm) or the development of fetal hydrops.
Purpose of the Study:
- To describe the natural history and outcomes of 24 infants with isolated CAVB diagnosed prenatally.
- To review existing literature on CAVB.
- To identify risk factors predicting outcomes in isolated CAVB.
Main Methods:
- Retrospective multicenter study involving 24 patients diagnosed with isolated CAVB in utero.
- Analysis of fetal heart rates, gestational age at diagnosis, development of fetal hydrops, and subsequent infant outcomes.
Main Results:
- CAVB was detected at a mean gestational age of 24.7 weeks; 10 fetuses presented with complete heart block initially.
- Fetal hydrops occurred in 42% of cases, associated with lower heart rates (47 bpm vs. 57 bpm).
- Mortality was 21%, linked to heart rates <50 bpm and fetal hydrops; 83% experienced poor outcomes (death, pacemaker, or dilated cardiomyopathy) associated with heart rates <60 bpm.
Conclusions:
- Isolated CAVB diagnosed in utero carries a high risk of morbidity and mortality.
- Fetal hydrops and lower fetal heart rates (<50 bpm) are associated with increased mortality.
- Fetal heart rates below 60 bpm predict the need for pacemaker implantation and/or the development of dilated cardiomyopathy.
Background:
Isolated congenital atrioventricular block (CAVB) diagnosed in utero is associated with a high morbidity and mortality. Prognosis is especially poor when heart rate drops below 55 beats per minute (bpm) and when fetal hydrops develops. We describe the natural history and outcome of 24 infants with isolated CAVB diagnosed in utero, review the literature, and assess the risk factors that could predict outcome.
Methods:
This was a retrospective multicenter study of 24 patients with isolated CAVB diagnosed in utero.
Results:
CAVB was detected at a mean gestational age (GA) of 24.7 +/- 5.1 weeks. Ten fetuses initially presented with complete heart block. Low heart rate or incomplete heart block was the first documentation of bradyarrhythmia in the other 14 fetuses. In 11 of them, CAVB developed during pregnancy after a median time of 3 (range 1-16) weeks. Fetal hydrops developed in 10 of 24 (42%) fetuses at a mean GA of 27.6 +/- 5.1 weeks. Hydropic fetuses showed lower heart rates during pregnancy (47 +/- 10 bpm) than non-hydropic fetuses (57 +/- 10 bpm). There were three intrauterine deaths; all were hydropic and female. Nine viable females and 12 males were born at a mean GA of 37.1 +/- 6.1 weeks with an average birth weight of 3097 +/- 852 g. Fifteen CAVB patients required pacemaker (PM) intervention, 10 of them immediately after birth. Dilated cardiomyopathy (DCM) developed in three infants of whom two died of congestive heart failure, shortly after the diagnosis was made; one is still alive. Mortality before or after birth was 21%, and was associated with heart rates below 50 bpm and development of fetal hydrops. Poor outcome, defined as death, PM implantation, or development of DCM, occurred in 83% of cases and was associated with heart rates below 60 bpm during pregnancy.
Conclusions:
Isolated CAVB diagnosed in utero is associated with high morbidity and mortality. Patients who develop fetal hydrops show lower heart rates during pregnancy than patients who do not. A fetal heart rate below 50 bpm and development of fetal hydrops is associated with increased mortality. Rates below 60 bpm are associated with PM requirement and/or DCM.

Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Mitral Stenosis I: Introduction
 01:27
Development of the Heart
As the embryo undergoes lateral folding, these paired tubes approach each other, merging into a single primitive heart tube by...
 01:20
Mitral Regurgitation I: Introduction
 01:27
Mitral Valve Prolapse I: Introduction