Related Experiment Video
Updated: Jul 4, 2026


Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Impact of cardiothoracic resident turnover on mortality after cardiac surgery: a dynamic human factor
Jeffrey H Shuhaiber1, Kimberley Goldsmith, Samer A M Nashef
1Papworth Hospital NHS Trust and MRC Biostatistics Unit, Institute of Public Health, Cambridge University, Cambridge, United Kingdom. jeffrey01@mac.com

Background:
The study was designed to determine whether cardiac surgical outcomes are affected during times of major turnover of cardiothoracic resident surgical staff and at the beginning versus the end of their training periods.
Methods:
This observational cohort study analyzed data from cardiac operations between April 1996 and March 2006 at a single institution. In-hospital mortality and other outcomes were compared between operations done during months of major change in resident staff rotation (July, August, January, February, n = 5,517) and the rest of the year (n = 10,773). We also compared outcomes at the beginning and end of surgical rotation for cardiothoracic residents. Adjustment was made for EuroSCORE (European System for Cardiac Operative Risk Evaluation), year of operation, and surgeon resident status. Analyses were done within surgery procedure subgroups of isolated coronary artery bypass graft surgery (CABG) and complex operations (CABG combined with other procedures).
Results:
Patient populations in the groups were similar. After risk adjustment, there was a significant increase in hospital mortality for the complex cases during months of resident staff change compared with rest of the year (odds ratio 1.3, 95% confidence interval: 1.3, 1.4; p = 0.02). There was, however, no significant difference in mortality for the CABG only cases (odds ratio 1.1, 95% confidence interval: 0.8, 1.4; p = 0.61). Risk-adjusted mortality after operations done by residents was the same at the start and finish of their surgical rotation. During the change months, the surgery time was 2.2 minutes longer on average in CABG operations (95% confidence interval: 0.3, 4.0; p = 0.02), and no different in combined cases.
Conclusions:
Periods of major change in resident surgical staff are associated with increased risk-adjusted in-hospital mortality after complex cardiac operations but not after CABG alone.
Related Concept Videos
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
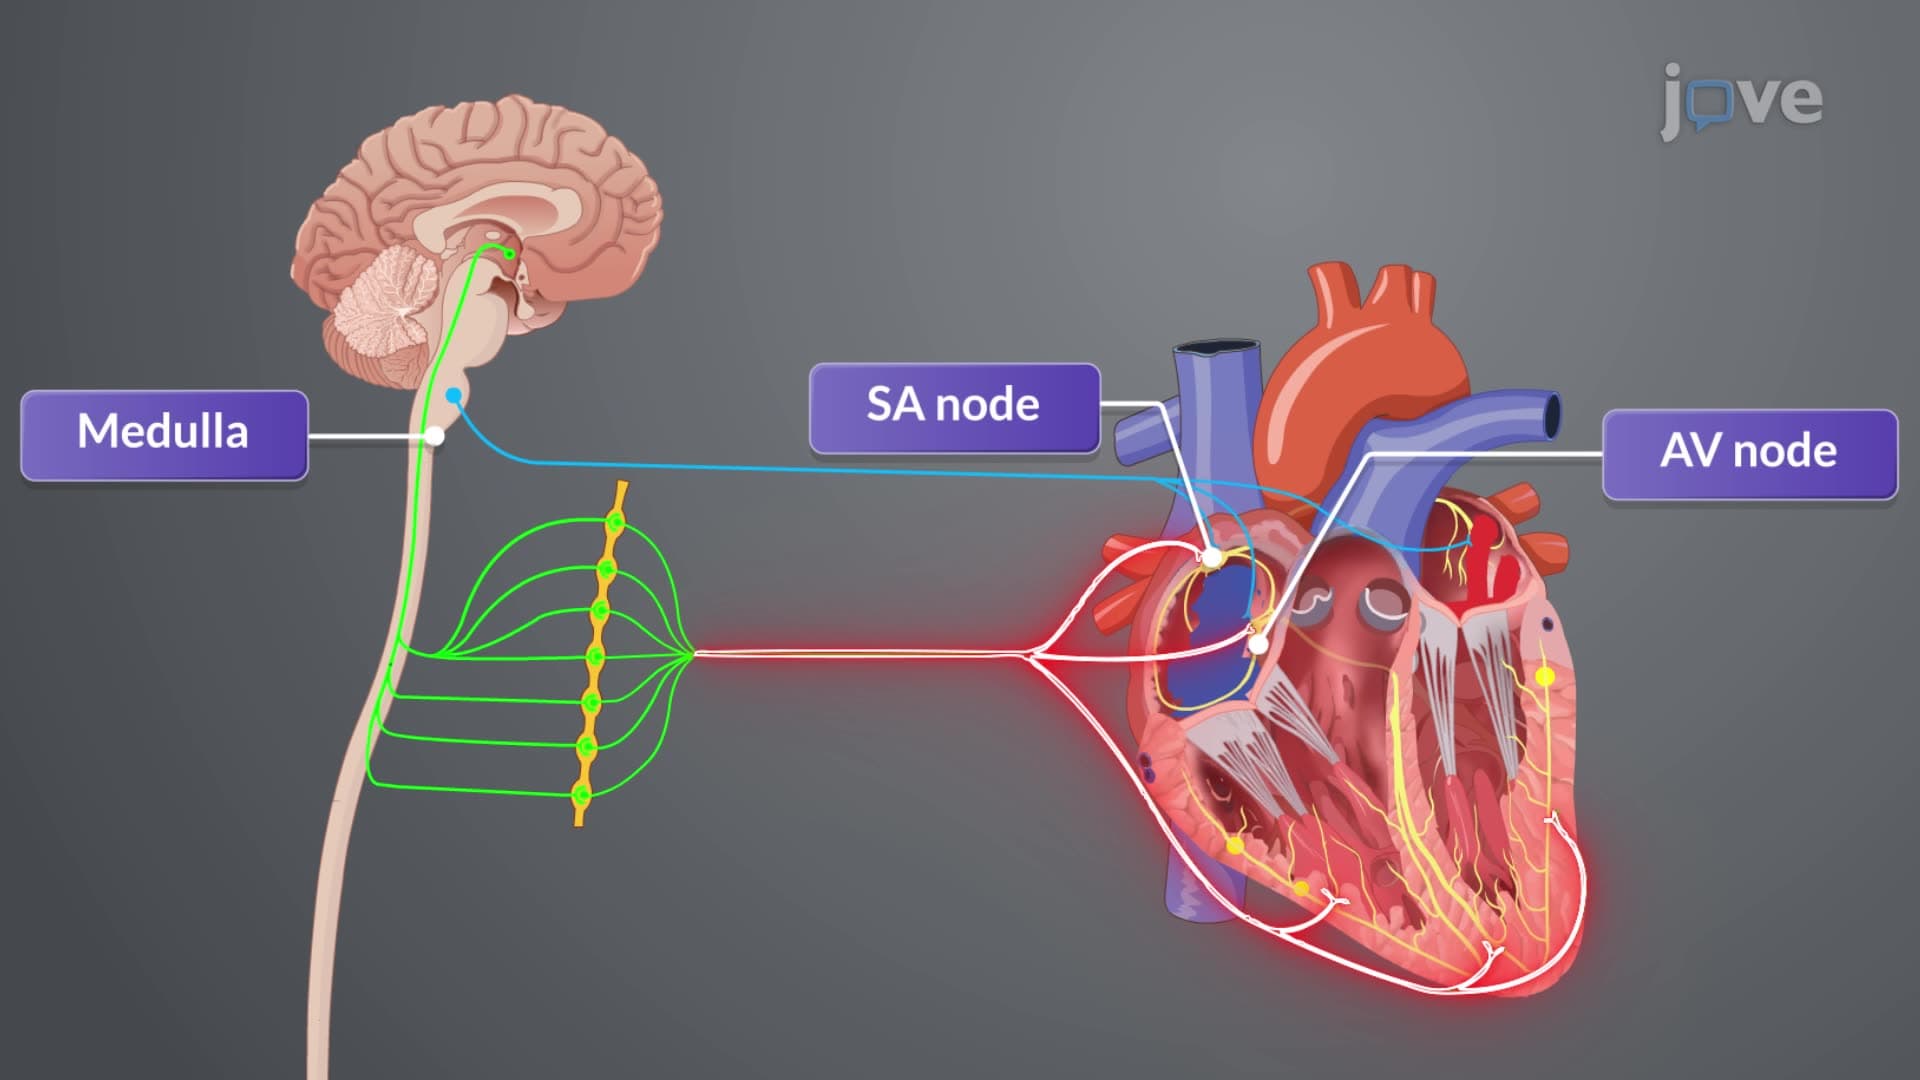
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:17
Pathophysiology of Heart Failure
 01:30
Factors Influencing Heart Rate
Let us explore the significant factors affecting heart rate, including age, body temperature, posture, acute pain, chemical influences,...