Related Experiment Video
Updated: Jul 4, 2026

Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Management of diabetic ketoacidosis in children and adolescents
Nicole A Sherry1, Lynne L Levitsky
1Pediatric Endocrine Unit, Massachusetts General Hospital for Children, Harvard University, Boston, Massachusetts 02114, USA. nsherry@partners.org

Abstract:
Diabetic ketoacidosis (DKA) is a life-threatening complication of diabetes mellitus. While it can occur in all types of diabetes mellitus, it is seen most often in patients with type 1 diabetes, either at presentation or as a result of non-compliance with medical therapy. DKA is characterized by hyperglycemia, acidosis, dehydration, and electrolyte abnormalities, which result from a deficiency of insulin and an excess of counter-regulatory hormones. Therapy is aimed at repleting fluids, and correcting acidosis and electrolyte disturbances by administration of intravenous fluid and intravenous insulin. Rapid correction should be avoided as it may result in untoward effects, including cerebral edema. Frequent monitoring of neurologic status and metabolic parameters aids in avoidance or early detection of complications. While much is still not understood about the most serious complication, cerebral edema, recent studies suggest that its development may be tied to a loss of cerebral autoregulation and a vasogenic mechanism of edema formation. Treatment of cerebral edema includes fluid restriction and administration of mannitol. Once DKA has resolved, subcutaneous insulin is initiated with careful consideration of its pharmacokinetics to avoid a period of insulin deficiency and metabolic decompensation.
Related Concept Videos
 01:25
Diabetic Ketoacidosis l: Introduction
 01:22
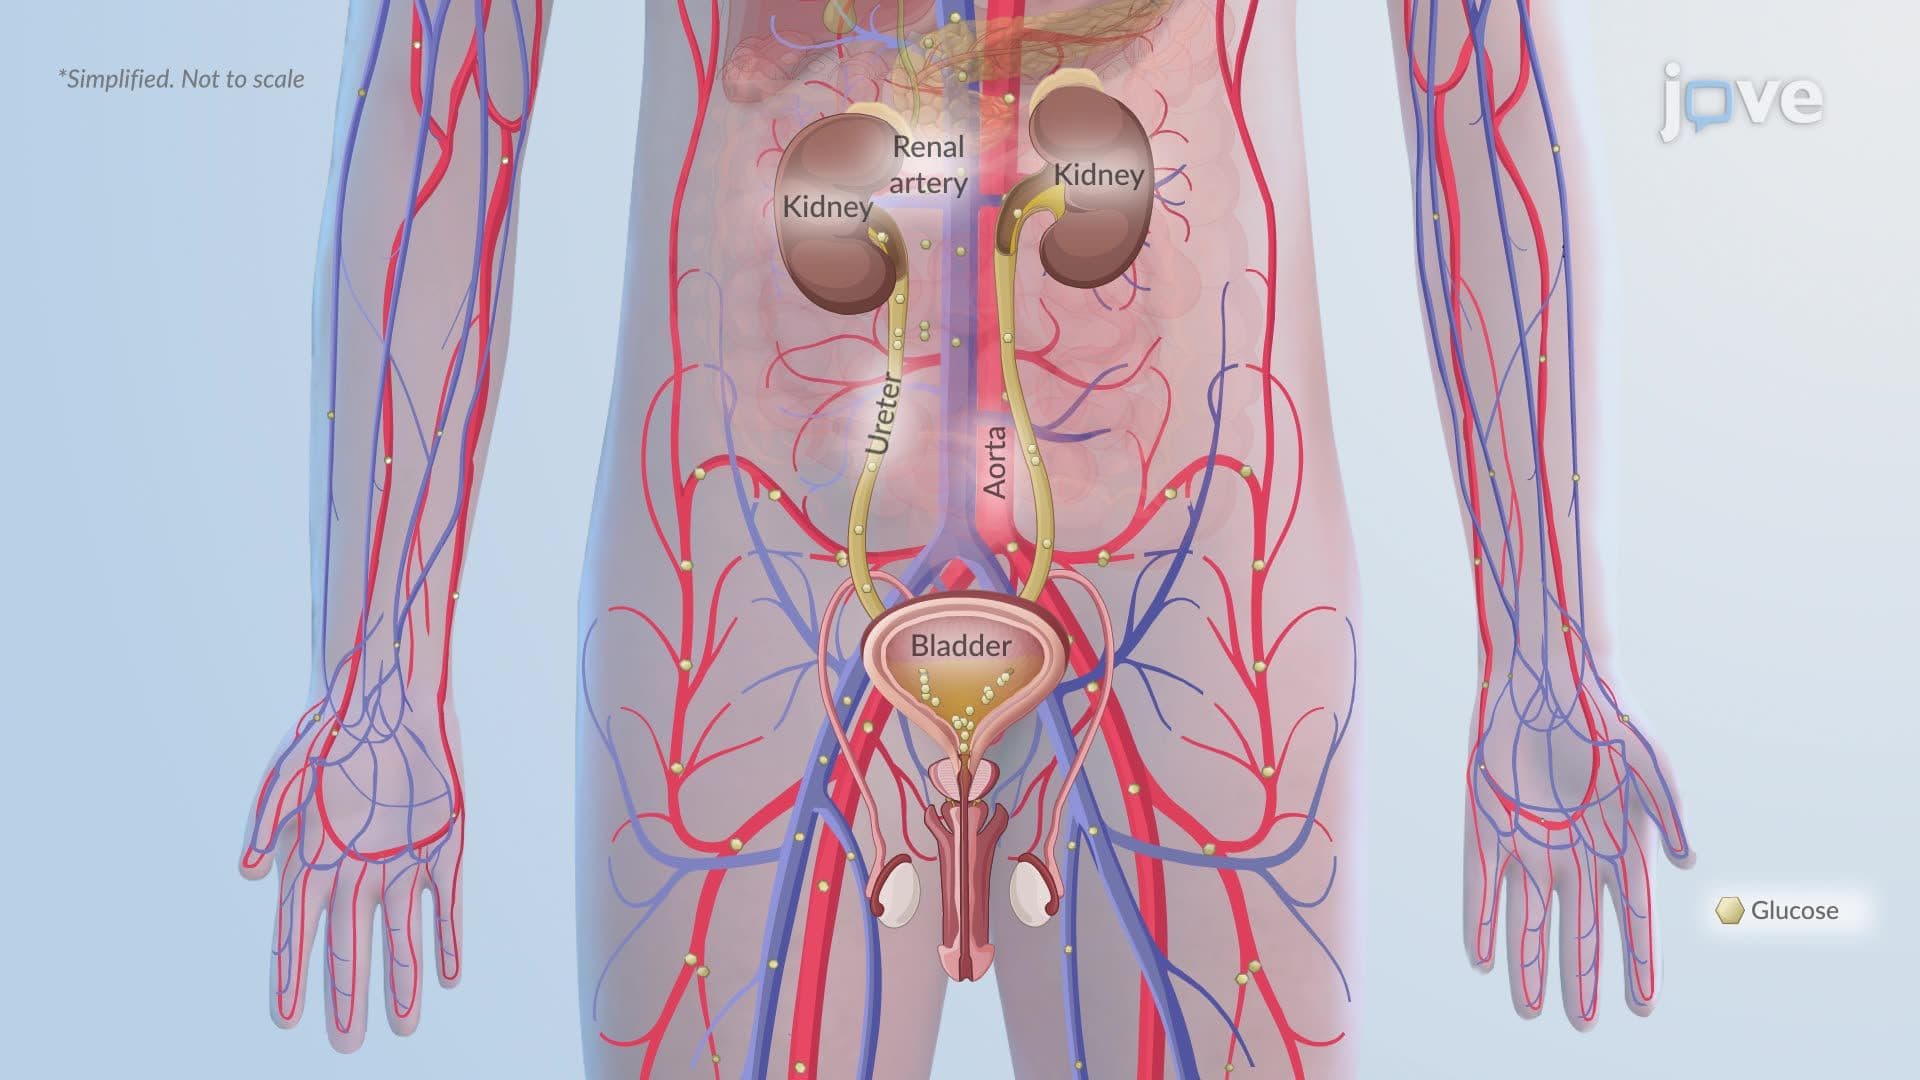
Diabetic Ketoacidosis ll: Pathophysiology
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:22
Complications of Diabetes Mellitus
 01:15
Hypoglycemia and Glucagon
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...