Related Experiment Video
Updated: Jul 4, 2026
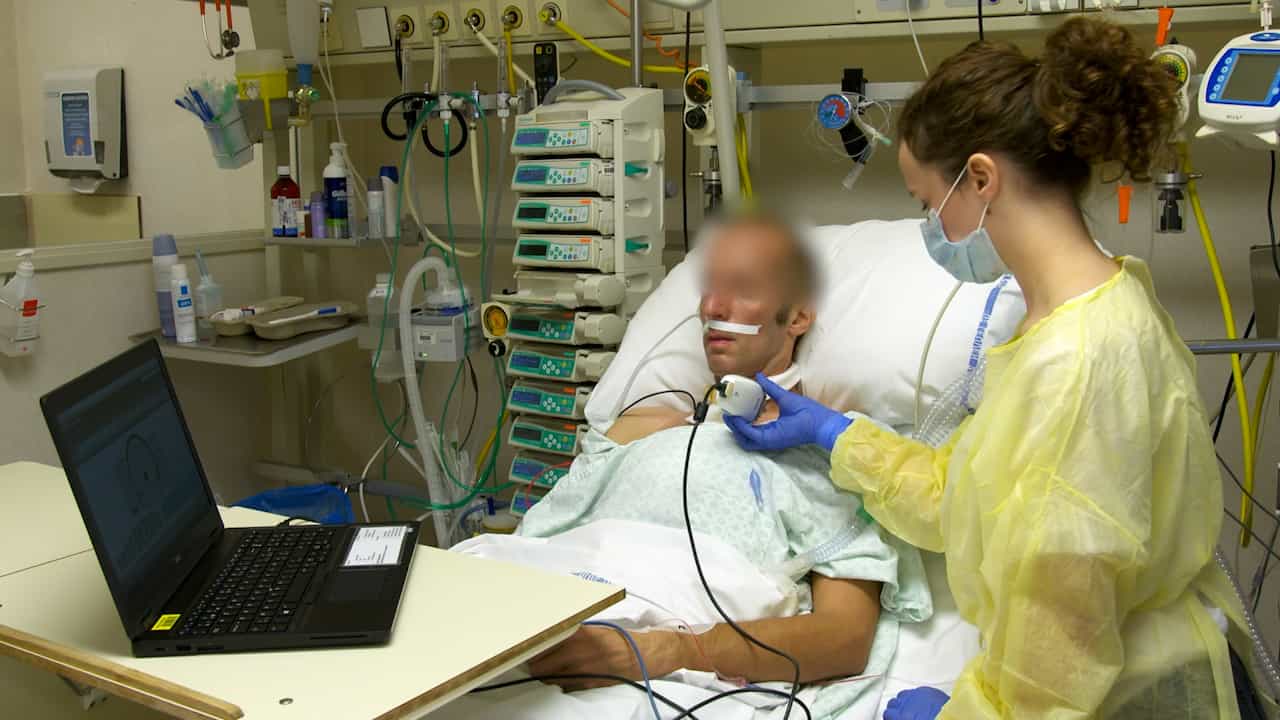

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Early intensive care unit mobility therapy in the treatment of acute respiratory failure
Peter E Morris1, Amanda Goad, Clifton Thompson
1Section on Pulmonary, Critical Care, Allergy and Immunologic Diseases, Wake Forest University School of Medicine, Winston Salem, NC, USA. pemorris@wfubmc.edu

Objective:
Immobilization and subsequent weakness are consequences of critical illness. Despite the theoretical advantages of physical therapy to address this problem, it has not been shown that physical therapy initiated in the intensive care unit offers benefit.
Design And Setting:
Prospective cohort study in a university medical intensive care unit that assessed whether a mobility protocol increased the proportion of intensive care unit patients receiving physical therapy vs. usual care.
Patients:
Medical intensive care unit patients with acute respiratory failure requiring mechanical ventilation on admission: Protocol, n = 165; Usual Care, n = 165.
Interventions:
An intensive care unit Mobility Team (critical care nurse, nursing assistant, physical therapist) initiated the protocol within 48 hrs of mechanical ventilation.
Measurements And Main Results:
The primary outcome was the proportion of patients receiving physical therapy in patients surviving to hospital discharge. Baseline characteristics were similar between groups. Outcome data are reflective of survivors. More Protocol patients received at least one physical therapy session than did Usual Care (80% vs. 47%, p < or = .001). Protocol patients were out of bed earlier (5 vs. 11 days, p < or = .001), had therapy initiated more frequently in the intensive care unit (91% vs. 13%, p < or = .001), and had similar low complication rates compared with Usual Care. For Protocol patients, intensive care unit length of stay was 5.5 vs. 6.9 days for Usual Care (p = .025); hospital length of stay for Protocol patients was 11.2 vs. 14.5 days for Usual Care (p = .006) (intensive care unit/hospital length of stay adjusted for body mass index, Acute Physiology and Chronic Health Evaluation II, vasopressor). There were no untoward events during an intensive care unit Mobility session and no cost difference (survivors + nonsurvivors) between the two arms, including Mobility Team costs.
Conclusions:
A Mobility Team using a mobility protocol initiated earlier physical therapy that was feasible, safe, did not increase costs, and was associated with decreased intensive care unit and hospital length of stay in survivors who received physical therapy during intensive care unit treatment compared with patients who received usual care.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: