Related Experiment Video
Updated: Jul 3, 2026
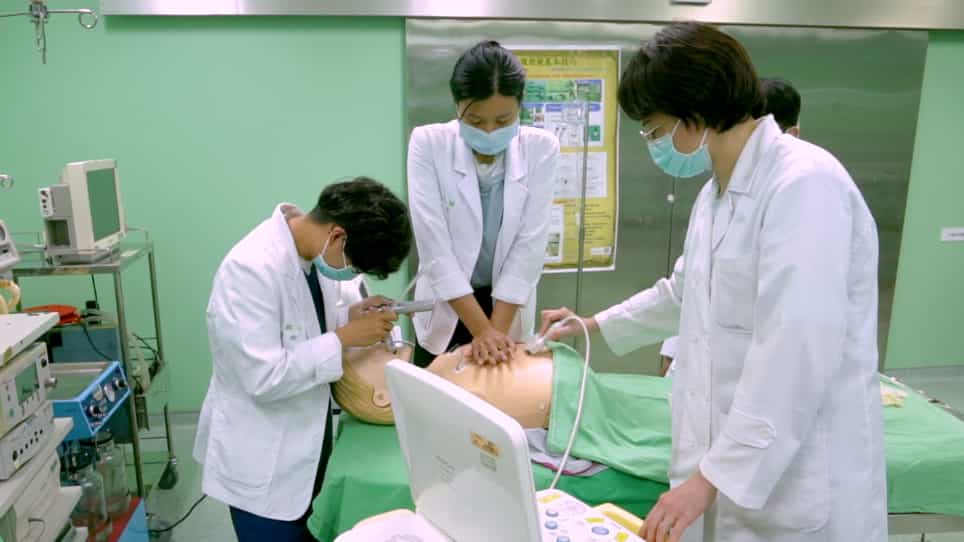

Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
Chest compression quality and rescuer fatigue with increased compression to ventilation ratio during single rescuer
Ikram U Haque1, Jai P Udassi, Sharda Udassi
1Division of Pediatric Critical Care Medicine, Department of Pediatrics, University of Florida College of Medicine, Gainesville, FL 32610-0296, USA. haqueiu@peds.ufl.edu

Insights
The 30:2 compression:ventilation ratio in pediatric CPR achieved more compression cycles without impacting depth or rate. However, some rescuers struggled to meet depth guidelines, regardless of the ratio used.
Area of Science:
- Pediatric resuscitation science
- Cardiopulmonary resuscitation techniques
Background:
- The optimal compression:ventilation (C:V) ratio for pediatric cardiopulmonary resuscitation (CPR) remains under investigation.
- The recommended 30:2 C:V ratio's impact on rescuer performance and physiological parameters in pediatric CPR is not fully understood.
Purpose of the Study:
- To evaluate the effects of the 30:2 C:V ratio on chest compression rate, depth, pressure, and rescuer fatigue during pediatric CPR.
- To compare the 30:2 C:V ratio with the 15:2 C:V ratio in simulated pediatric resuscitation scenarios.
Main Methods:
- A randomized crossover observational study design was employed.
- Adolescent and infant manikins were used to digitally record CPR metrics.
- Certified volunteers performed CPR using either the 30:2 or 15:2 ratio, with heart rate and respiratory rate monitored.
Main Results:
- The 30:2 C:V ratio resulted in a higher number of total compression cycles compared to the 15:2 ratio across all manikin sizes.
- No significant differences were observed in compression depth or peak compression pressure between the two ratios.
- Rescuer heart rate increased significantly during 30:2 CPR in adolescent and one-hand infant manikin groups, but subjective fatigue was not significantly different.
Conclusions:
- The 30:2 C:V ratio allows for more compression cycles in single-rescuer pediatric basic life support (BLS) without compromising compression depth, pressure, or rate.
- While increased heart rate was noted with the 30:2 ratio on larger manikins, subjective fatigue differences were minimal.
- A significant proportion of rescuers failed to achieve recommended compression depths, irrespective of the C:V ratio, particularly in adolescent and two-finger infant manikin scenarios.
Objective:
The effects of the recommended 30:2 compression:ventilation (C:V) ratio on chest compression rate (CR), compression depth (CD), compression pressure (CP) and rescuer fatigue is unknown during pediatric CPR. We hypothesized that a 30:2 C:V ratio will decrease compression depth and compression pressure and increase rescuer fatigue compared with a 15:2 ratio.
Design:
Randomized crossover observational study.
Methods:
Adolescent, child and infant manikins were modified to digitally record compression rate, compression depth, compression pressure and total compression cycles (CC). BLS or PALS certified volunteers were randomized to five CPR groups: adolescent (AD), child 1-hand (OH), child 2-hand (TH), infant two-finger (TF) and infant two-thumb (TT). Each rescuer performed each ratio for 5 min with the order randomized. Rescuer heart rate (HR) and respiratory rate (RR) were recorded continuously during CPR and used to determine the recovery time (RT) for HR/RR to return to baseline. Data (mean+/-S.D.) were contrasted by paired differences for quantitative data and the sign rank test for ordinal data.
Results:
Eighty subjects (16 per group) were randomized. The peak compression pressure and compression rate were not different within any group, but total compression cycle were higher in all 30:2 groups. Compression depth (mm) was not significantly different within any group. The rescuer's HR (bpm) increased significantly during 30:2 CPR in AD and OH group with no significant differences in RR and recovery time. Subjects reported that 15:2 CPR was easier to perform (P<0.001).
Conclusion:
During single rescuer pediatric BLS, more compression cycles were achieved with 30:2 C:V ratio without effect on compression depth, pressure and rate. Increased HR with 30:2 C:V ratio was noted during larger manikin CPR without subjective difference of reported fatigue. Most rescuers in AD and TF group did not achieve recommended compression depth regardless of C:V ratio.

Related Concept Videos
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:23
Acute Respiratory Failure-IV