Related Experiment Video
Updated: Jul 3, 2026

Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Posttraumatic posterior urethral strictures in children--management and intermediate-term follow-up in tertiary care
Manish Singla1, Mrigank S Jha, K Muruganandam
1Department of Urology and Renal Transplantation, Sanjay Gandhi Post Graduate Institute of Medical Sciences, Lucknow, UP, India.

Insights
Transperineal anastomotic urethroplasty is effective for pediatric posterior urethral strictures, achieving a 100% success rate after secondary procedures. Previous urethral manipulation did not significantly impact outcomes.
Area of Science:
- Pediatric Urology
- Traumatic Urethral Strictures
- Surgical Reconstruction
Background:
- Posttraumatic posterior urethral strictures are a significant challenge in pediatric urology.
- Management requires careful consideration of surgical approach and patient factors.
Purpose of the Study:
- To evaluate the management and intermediate-term outcomes of posttraumatic posterior urethral strictures in children.
- To assess the effectiveness of transperineal anastomotic urethroplasty.
Main Methods:
- Retrospective review of 28 pediatric patients (<18 years) treated for posttraumatic posterior urethral strictures between 2000-2006.
- Analysis of trauma cause, injury extent, imaging, prior treatments, and outcomes over a median 36-month follow-up.
Main Results:
- Transperineal anastomotic urethroplasty achieved a 75% initial success rate in 27 patients.
- All treatment failures were successfully managed with secondary endoscopic procedures or redo urethroplasty, yielding a 100% final success rate.
- Previous urethral manipulation did not significantly affect intermediate-term results.
Conclusions:
- Transperineal anastomotic urethroplasty is a viable primary treatment for most pediatric posttraumatic posterior urethral strictures.
- The transpubic approach is recommended for more complex strictures.
- Intermediate-term outcomes are not adversely affected by prior urethral manipulations.
Objectives:
To evaluate the management and intermediate-term follow-up of posttraumatic posterior urethral strictures in children.
Methods:
From March 2000 to November 2006, the surgical records of 28 children (< or = 18 years) who had been admitted for treatment of posttraumatic posterior urethral strictures were retrospectively reviewed. The patients had been followed up for a median of 36 months (range 3-58). The cause of trauma, extent of urinary tract injury, radiologic examination findings, previous treatment, and its effect on the final outcome, treatment complications,, and failures were evaluated.
Results:
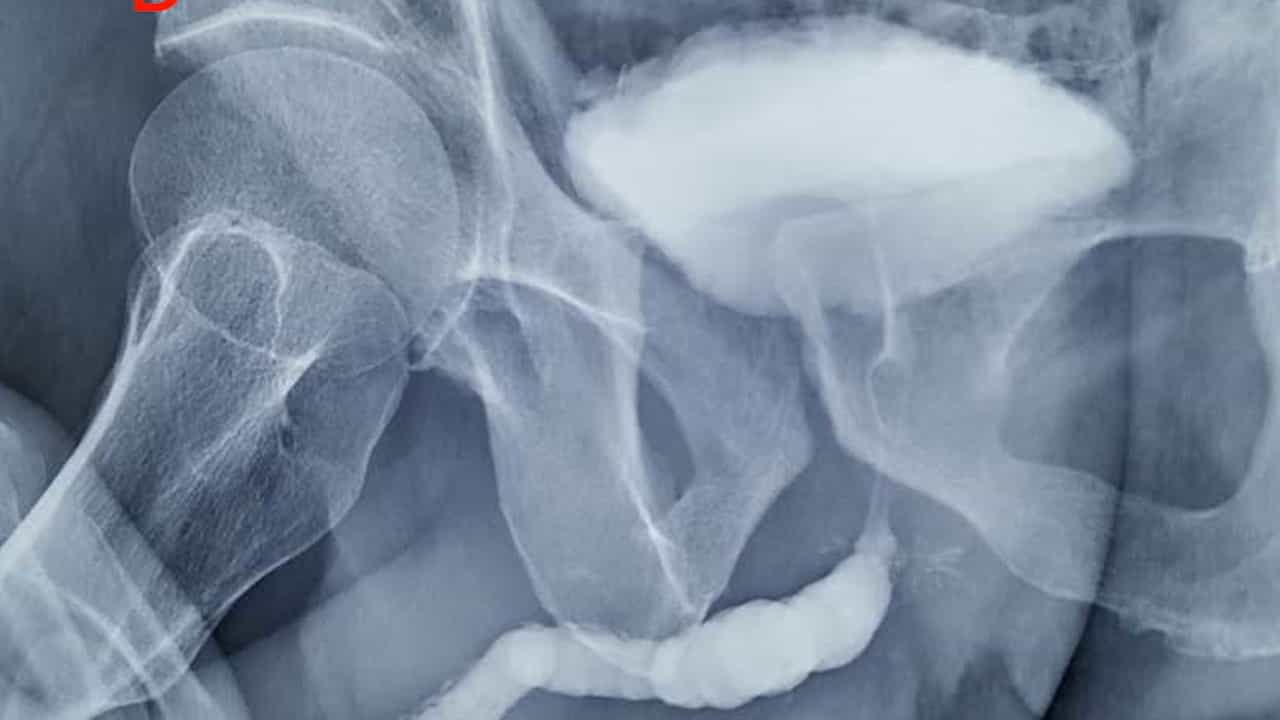
The mean age of the patients was 12.1 years (range 5-18) at the injury. The estimated radiographic mean stricture length before surgery was 3.41 cm (range 2-6). Of the 28 patients, 27 were treated with transperineal anastomotic urethroplasty, with a success rate of 75%. All treatment failures were at the anastomotic site and occurred within the first year of anastomotic urethroplasty. The failed repairs (7 cases) were successfully managed endoscopically in 4 patients and by redo urethroplasty in 3, for a final success rate of 100%. Of the 28 patients, 15 (80%) with urethral manipulation before anastomotic urethroplasty had a satisfactory result compared with 69.3% of patients without previous surgical treatment. The difference was not statistically significant.
Conclusions:
Most posttraumatic posterior urethral strictures in children can be managed through the perineal route. The transpubic approach should be reserved for more complex posterior strictures. Previous urethral manipulations did not affect the intermediate-term results of anastomotic urethroplasty.
Related Concept Videos
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:30
Urinary Tract Calculi III: Medical Management
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:17
Urinary Tract Infection IV: Nursing Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations