Related Experiment Video
Updated: Jul 3, 2026
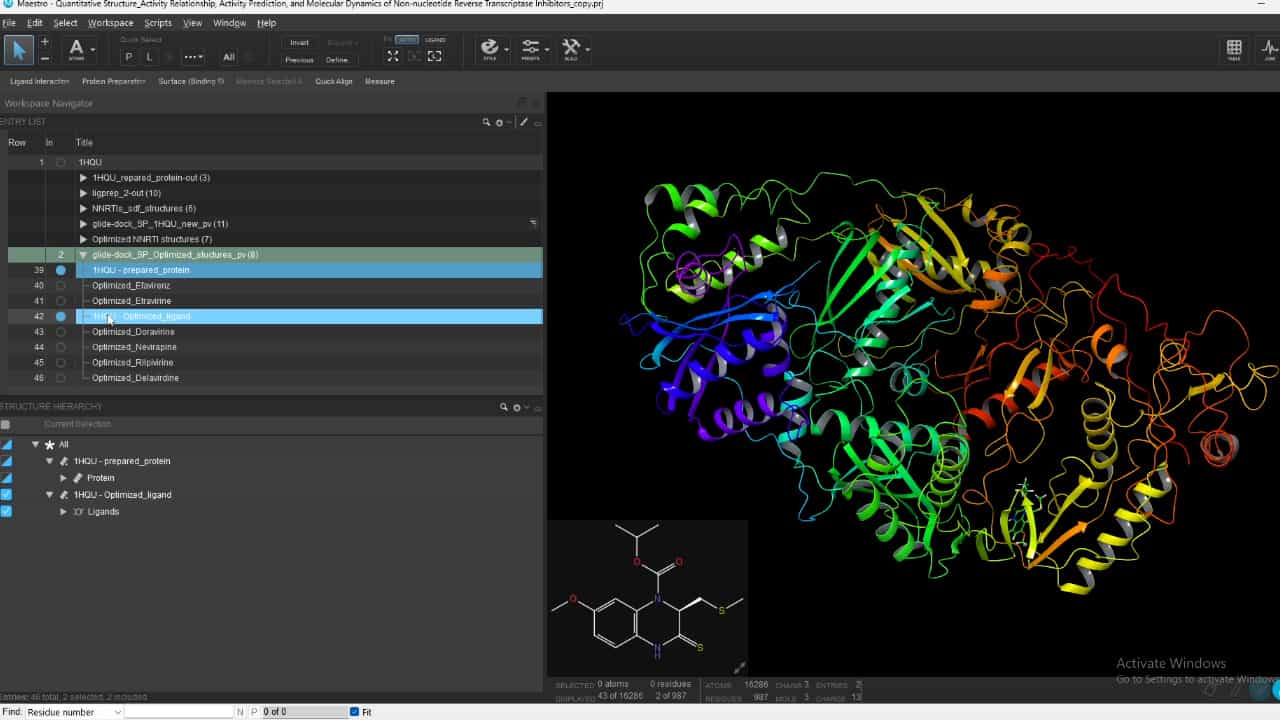

Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Etravirine for the treatment of HIV infection
E Seminari1, A Castagna, A Lazzarin
1Clinical Epidemiology and Biometric Unit, Fondazione IRCCS Policlinico San Matteo Pavia, P.le Golgi 2, I-27100 Pavia, Italy. e.seminari@smatteo.pv.it

Abstract:
Etravirine (TMC125) is a next-generation non-nucleoside reverse transcriptase inhibitor (NNRTI) that is being developed for the treatment of HIV-1 infections. The drug was recently approved by the US FDA to be used in combination with other anti-HIV medications. Etravirine is a highly flexible diarylpyrimidine compound, with favorable binding interactions toward mutant HIV strains as well as wild-type virus. This conformation confers an increased genetic barrier to resistance compared with other NNRTIs: multiple mutations are required before there is a decrease in susceptibility to etravirine; whereas, only one mutation (K103N) is typically needed to confer high-level resistance to the first-generation NNRTIs. In vitro, etravirine is predominantly metabolized by cytochrome P450 (CYP)3A4 and CYP2C (2C9, 2C18 and 2C19). In vivo, the most important metabolic pathway for etravirine is methyl hydroxylation, with subsequent glucuronidation of the metabolites. Etravirine is an inducer of CYP3A4 and a weak inhibitor of CYP2C9, CYP2C19 and P-glycoprotein. In Phase II and III trials in treatment-experienced patients, treatment with etravirine led to better virological suppression than placebo. In the DUET I and II trials (Phase III), approximately 60% of the etravirine group achieved a confirmed viral load of less than 50 copies/ml at week 24, compared with approximately 40% in the placebo arm. The mean change in viral load at week 24 was -2.34 (standard deviation: 1.31) and -1.68 (1.40) log(10) copies/ml in the etravirine and placebo groups, respectively. The presence of three or more NNRTI-associated mutations at baseline negatively influenced the outcome. There were no safety concerns and no major differences in frequency or severity of side effects between etravirine and placebo groups, with the exception of rash. Furthermore, the overall rate of discontinuation due to any adverse event was similar between the etravirine and placebo groups. The most common adverse events reported were rash and nausea.

Related Concept Videos
 01:22
Antiviral Nucleoside Inhibitors
 01:10
Retrovirus Life Cycles
 02:33
Retroviruses
 01:25
Inhibitors Of Virion Release
 01:30
Inhibitors of Viral Protein Synthesis
 01:29
Subviral Agents