Related Experiment Video
Updated: Jul 2, 2026

System for Efficacy and Cytotoxicity Screening of Inhibitors Targeting Intracellular Mycobacterium tuberculosis
Published on: April 5, 2017
Pharmacokinetics of rosuvastatin when coadministered with rifampicin in healthy males: a randomized, single-blind,
Wei Zhang1, Sheng Deng, Xiao-Ping Chen
1Pharmacogenetics Research Institute, Institute of Clinical Pharmacology, Central South University, Changsha, Hunan, China.

Background:
Rifampicin (rifampin) has been reported to have drug-drug interaction with several 3-hydroxy-3-methylglutaryl coenzyme A reductase inhibitors due to its ability to influence the function of cytochrome P450 enzymes or transporters. Rosuvastatin is absorbed from the blood into the liver by organic anion transporting polypeptide 1B1 and is then metabolized by cytochrome P450 isozyme 2C9.
Objective:
The aim of this study was to examine the effect of rifampicin on the pharmacokinetics of rosuvastatin.
Methods:
This was a randomized, single-blind, placebo-controlled, crossover study, with a 4-week washout period. Healthy male volunteers were treated for 6 days with rifampicin 450 mg or placebo once daily. On days 0 and 7, a single oral dose of rosuvastatin 20 mg was administered. Plasma concentrations of rosuvastatin were measured by liquid chromatography-tandem mass spectrometry.
Results:
A total of 18 healthy Chinese male volunteers (mean [SD] age, 21 [2] years; weight, 62 [7] kg; and body mass index was within the normal range [22.0-24.0 kg/m2]) were included in the study. The plasma concentrations of rosuvastatin were not significantly changed by pretreatment with rifampicin, although there was considerable interindividual variation in the plasma concentration of rosuvastatin. During the rifampicin phase, the AUC(0-infinity) of rosuvastatin decreased in 10 and increased in 8 of the 18 subjects. In 3 of the 8 subjects, the AUC(0-infinity) of rosuvastatin during the rifampicin phase was > or = 50% compared with the placebo phase; and only 1 increased by more than double (183%). Of those in the decreased group (n = 10), the AUC(0-infinity) values were decreased by >50% in 3 subjects and were not decreased by >30% in the remaining 7 subjects. The mean AUC(0-infinity) of rosuvastatin was 95.8% (110.4 [41.4] vs 115.3 [30.9] ng/mL . h(-1)) of the corresponding value during the placebo phase (P = NS). There was no statistically significant difference in either C(max) or t(1/2) of rosuvastatin between the rifampicin-treated and placebo groups (18.5 [6.3] vs 16.5 [5.5] ng/mL; 12.8 [3.0] vs 13.3 [2.8] h). The oral clearance of rosuvastatin was not significantly affected by rifampicin pretreatment either (0.4 [0.3] vs 0.3 [0.2] L . h; P = 0.072).
Conclusion:
The pharmacokinetics of rosuvastatin were not significantly changed by coadministration of rifampicin in this small group of healthy male volunteers.

Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:26
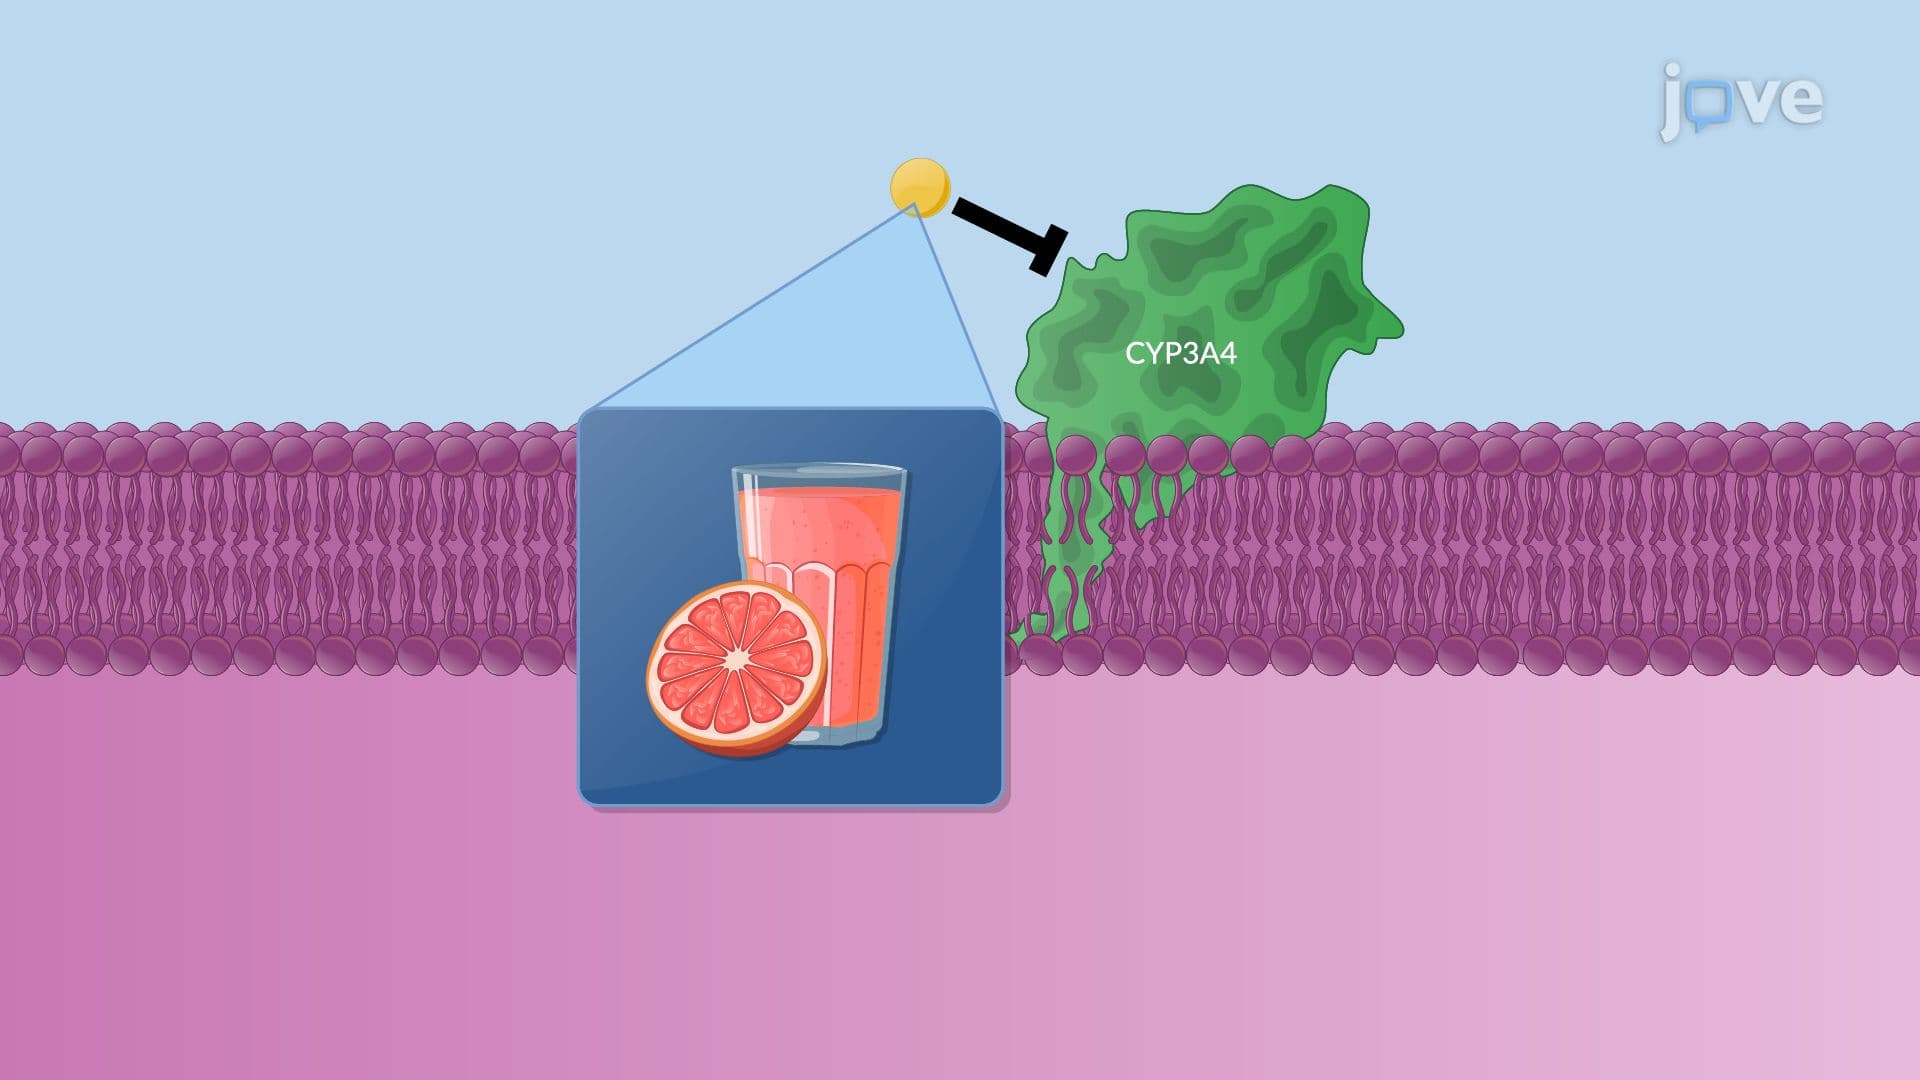
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:30
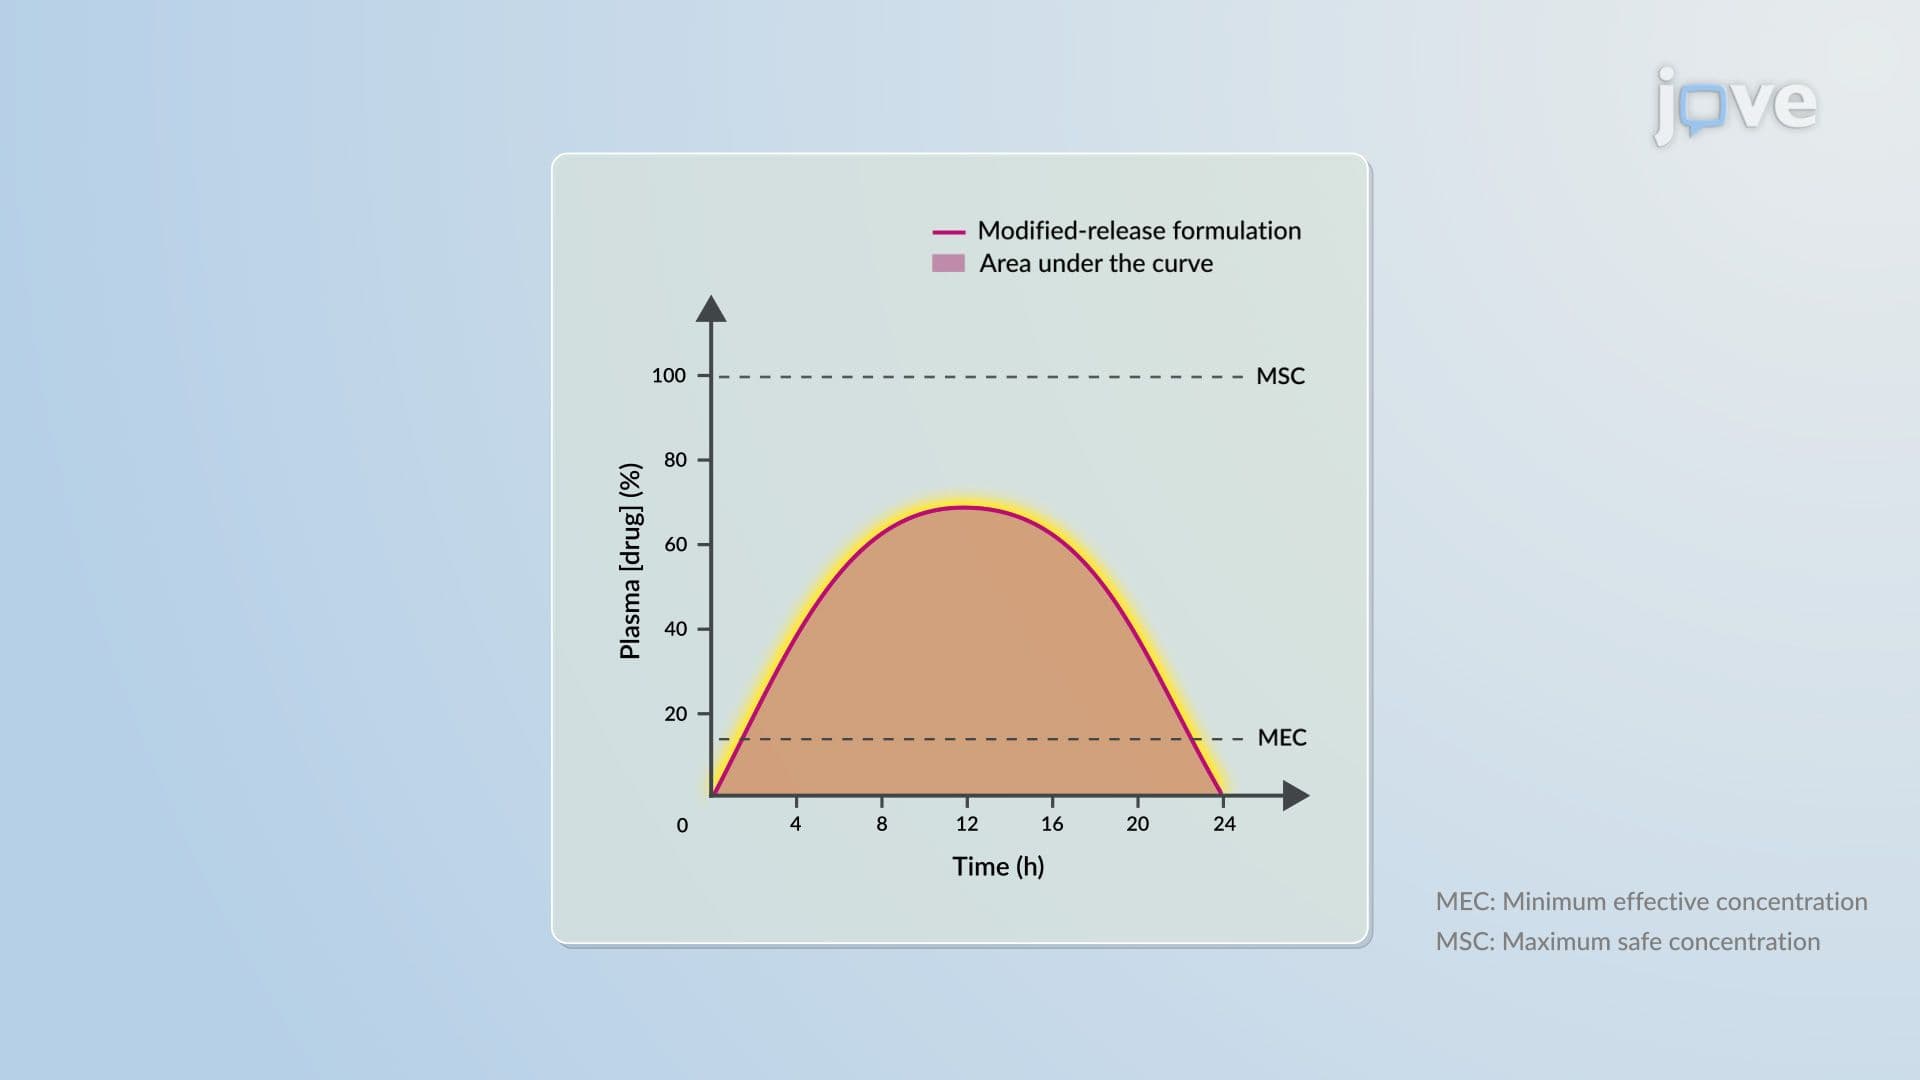
Modified-Release Drug Delivery Systems: Bioavailability