Related Experiment Video
Updated: Jul 2, 2026
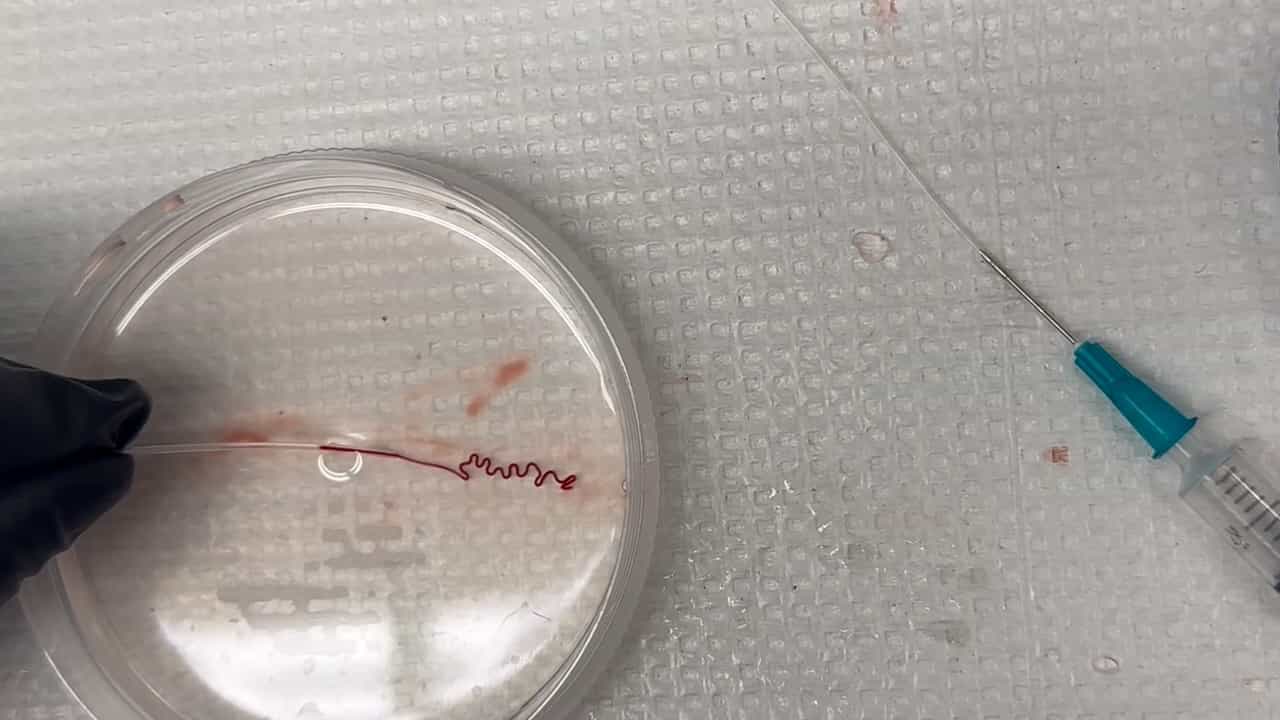

The Stroke Preclinical Assessment Network Multi-Laboratory Model of Thromboembolic Stroke with Thrombolysis: TE-MCAo
Published on: December 19, 2025
New pathways for evaluating potential acute stroke therapies
Marc Fisher1, Kenneth Cheung, George Howard
1Department of Neurology, University of Massachusetts Medical School, Worcester, MA, USA. fisherm@ummhc.org

Abstract:
Pharmacological therapy for acute ischemic stroke remains limited to one successful, approved treatment: tissue plasminogen activator within 3 h of stroke onset. Many neuroprotective drugs and a few other thrombolytics were evaluated in clinical trials, but none demonstrated unequivocal success and were approved by regulatory agencies. The development paradigm for such therapies needs to provide convincing evidence of efficacy and safety to obtain approval by the Food and Drug Administration (FDA). The FDA modernization act of 1997 stated that such evidence could be derived from one large phase III trial with a clinical endpoint and supportive evidence. Drugs being developed for acute ischemic stroke can potentially be approved under this act by coupling a major phase III trial with supportive evidence provided by a phase IIB trial demonstrating an effect on a relevant biomarker such as magnetic resonance imaging or computed tomography assessment of ischemic lesion growth. Statistical approaches have been developed to optimize the design of such an imaging-based phase IIB study, for example approaches that modify randomization probabilities to assign larger proportions of patients to the 'winning' strategy (i.e. 'pick the winner' strategies) with an interim assessment to reduce the sample size requirement. Demonstrating a treatment effect on a relevant imaging-based biomarker should provide supportive evidence for a new drug application, if a subsequent phase III trial with a clinical outcome demonstrates a significant treatment effect.
Insights
Developing new acute ischemic stroke treatments requires robust evidence. Combining large clinical trials with imaging biomarker data from phase IIB studies can support FDA approval for novel neuroprotective drugs.
Area of Science:
- Neurology
- Pharmacology
- Medical Imaging
Background:
- Current pharmacological treatments for acute ischemic stroke are limited, with only tissue plasminogen activator approved within a narrow time window.
- Numerous neuroprotective drugs and thrombolytics have failed to gain regulatory approval due to insufficient evidence of efficacy and safety.
Purpose of the Study:
- To propose an optimized development paradigm for novel acute ischemic stroke therapies.
- To leverage the FDA Modernization Act of 1997 for drug approval pathways.
- To integrate clinical trial data with imaging biomarker evidence for enhanced drug evaluation.
Main Methods:
- Utilizing phase IIB trials to demonstrate treatment effects on imaging biomarkers like MRI or CT assessments of ischemic lesion growth.
- Employing statistical approaches, such as 'pick the winner' strategies with interim assessments, to optimize phase IIB study design and reduce sample size.
- Coupling a large phase III clinical trial with supportive phase IIB imaging data for regulatory submission.
Main Results:
- Optimized statistical designs for imaging-based phase IIB studies can enhance efficiency and reduce sample size requirements.
- Demonstrating a significant treatment effect on imaging biomarkers provides crucial supportive evidence for new drug applications.
- This approach aims to strengthen the evidence base for novel acute ischemic stroke therapies.
Conclusions:
- A combined strategy of large phase III clinical trials and supportive phase IIB imaging biomarker data can facilitate FDA approval for new acute ischemic stroke drugs.
- This paradigm offers a more efficient pathway for developing and approving effective neuroprotective therapies.
- Successful demonstration of treatment effect on imaging biomarkers can bolster the case for clinical efficacy in subsequent phase III trials.
