Related Experiment Video
Updated: Jul 2, 2026


Isolation and Analysis of Aortic Arch and Root Lesions in an Atherosclerotic Mouse Model
Published on: February 14, 2025
Aortic arch atheroma
Jorge A Zavala1, Pierre Amarrenco, Stephen M Davis
1National Stroke Research Institute, Heidelbergh Heights, Victoria, Australia.

Severe atheroma of the aortic arch has now been established as an important risk factor and mechanism for stroke and peripheral embolism. The odds ratio for stroke or peripheral embolism in patients with severe arch atheroma is greater than four, and for mobile atheroma it is greater than 12. The prevalence of severe arch atheroma among patients presenting with acute ischaemic stroke, at over 20%, is in the same order as that of atrial fibrillation and carotid atherosclerosis. In patients with ischaemic stroke for which no cause has been identified, it is reasonable to determine as to whether they have severe arch atheroma by performing a transoesophageal echocardiogram. Recurrent stroke is common in patients with aortic arch atheroma that are thicker than 4 mm or with mobile components, particularly in the elderly, cigarette smokers, and those with hypertension or diabetes. Patients found to have severe atheroma are at high risk of recurrent events (14.2% per year) and may, therefore, need an aggressive secondary prevention strategy. Currently, there is uncertainty as to what this should be, but either combination antiplatelet therapy (aspirin plus clopidogrel) or anticoagulation with warfarin (target INR 2.0-3.0) are commonly used. Which of these is most effective will be evident after the completion of the aortic arch related cerebral hazard trial.
Severe atheroma of the aortic arch has now been established as an important risk factor and mechanism for stroke and peripheral embolism. The odds ratio for stroke or peripheral embolism in patients with severe arch atheroma is greater than four, and for mobile atheroma it is greater than 12. The prevalence of severe arch atheroma among patients presenting with acute ischaemic stroke, at over 20%, is in the same order as that of atrial fibrillation and carotid atherosclerosis. In patients with ischaemic stroke for which no cause has been identified, it is reasonable to determine as to whether they have severe arch atheroma by performing a transoesophageal echocardiogram. Recurrent stroke is common in patients with aortic arch atheroma that are thicker than 4 mm or with mobile components, particularly in the elderly, cigarette smokers, and those with hypertension or diabetes. Patients found to have severe atheroma are at high risk of recurrent events (14.2% per year) and may, therefore, need an aggressive secondary prevention strategy. Currently, there is uncertainty as to what this should be, but either combination antiplatelet therapy (aspirin plus clopidogrel) or anticoagulation with warfarin (target INR 2.0-3.0) are commonly used. Which of these is most effective will be evident after the completion of the aortic arch related cerebral hazard trial.


Related Concept Videos
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Atherosclerosis I: Introduction
 01:30
Aneurysm I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:14
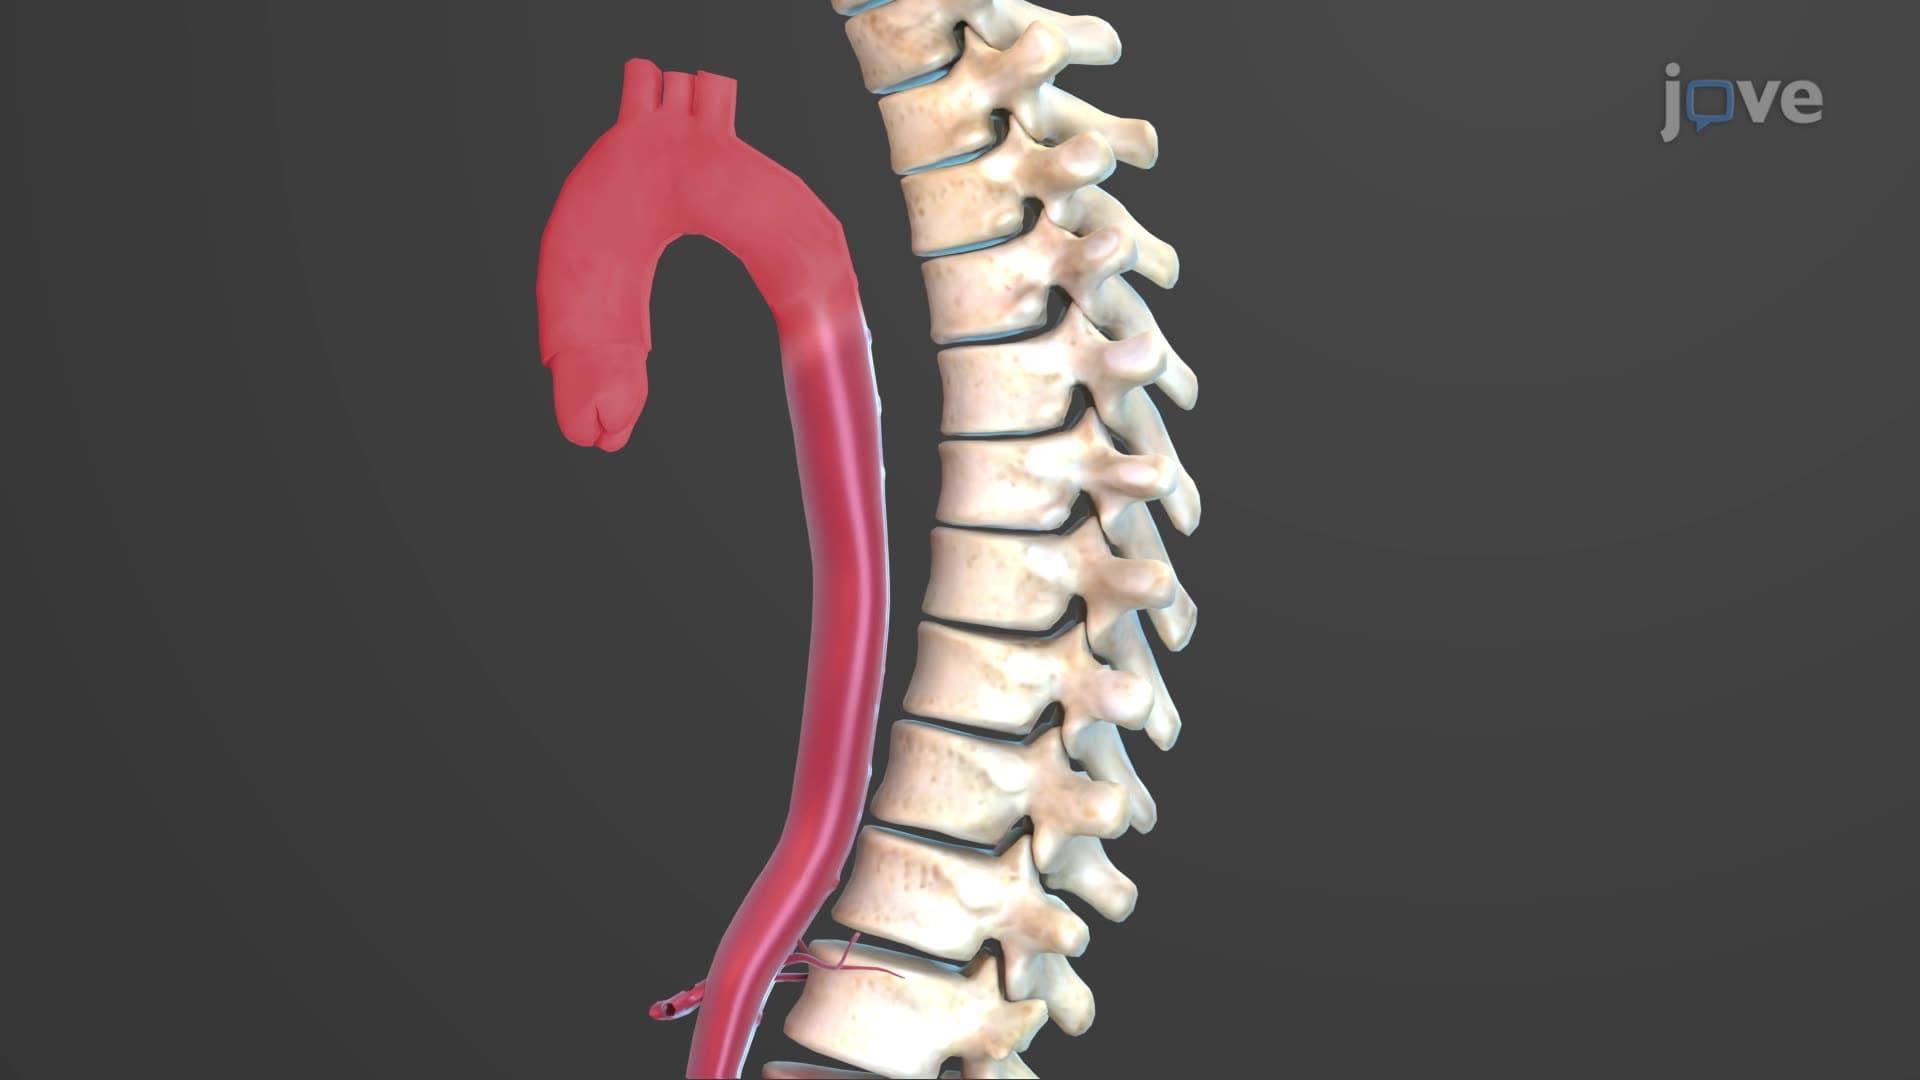
The Aorta
The average diameter of the aorta is approximately 2-3 cm, but the size can vary depending on the section of the aorta and the individual's age, sex, and body size. The aorta is...