Related Experiment Video
Updated: Jul 2, 2026


Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
Diagnostic problems in anal pathology
Teri A Longacre1, Christina S Kong, Mark L Welton
1Department of Pathology, Stanford University, Stanford, CA 94305, USA. longacre@stanford.edu

Abstract:
Anal squamous cell carcinoma and its precursor lesions are increasing in incidence in the United States and Europe. This trend predates human immunodeficiency virus/acquired immune deficiency syndrome and has been associated with persistent high-risk human papilloma virus (HPV) genotype infection, previous lower genital tract dysplasia/carcinoma, high frequency anoreceptive intercourse, heavy cigarette smoking, immunosuppression in solid organ transplant and immune disorders, and human immunodeficiency virus seropositivity. Screening protocols for at-risk patients are under active investigation and pathologists are often asked to assess anal canal and perianal biopsies for the presence of dysplasia and/or invasive carcinoma. Because underdiagnosis and overdiagnosis of anal cancer and precancer may lead to inappropriate treatment, it is important for the pathologist to be aware of current screening strategies, specific risk lesions, and the role of pathology in initial diagnosis and evaluation of anal biopsy and/or resection specimens. Standardized histologic criteria and uniform terminology should be used for reporting all anal canal and perianal squamous intraepithelial lesions. HPV subtyping, anal cytology, and recently identified biomarkers, such as p16 and Becton Dickinson ProEx C may provide additional information in problematic cases, but it is important to be aware of the limitations of these assays. HPV has been linked to all the major histologic subtypes of anal carcinoma (eg, basaloid, cloacogenic, transitional, etc.) and this association is strongest for anal canal lesions. With the possible exception of the microcystic pattern, histologic subtype does not seem to predict prognosis; and anal squamous cell carcinomas should be classified as either keratinizing or nonkeratinizing. Poorly differentiated squamous cell carcinomas have a worse prognosis and should be distinguished from poorly differentiated adenocarcinoma, melanoma, and neuroendocrine tumors. Very well differentiated squamous cell carcinoma with pushing margins (so-called giant condyloma of Buschke and Lowenstein) should be classified as verrucous carcinoma; this tumor shows aggressive local infiltration but does not metastasize. As all anal condylomata may harbor foci of high-grade dysplasia or invasive carcinoma, careful sectioning and complete histologic examination is required.
More Related Videos
 04:57
Comparative Analysis of Automatic Fecal Analyzer versus Direct Wet Smear Microscopy for Detecting Parasitic Infections in Stool Samples
Published on: April 25, 2025
 07:41
Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:19
Appendicitis
 01:27
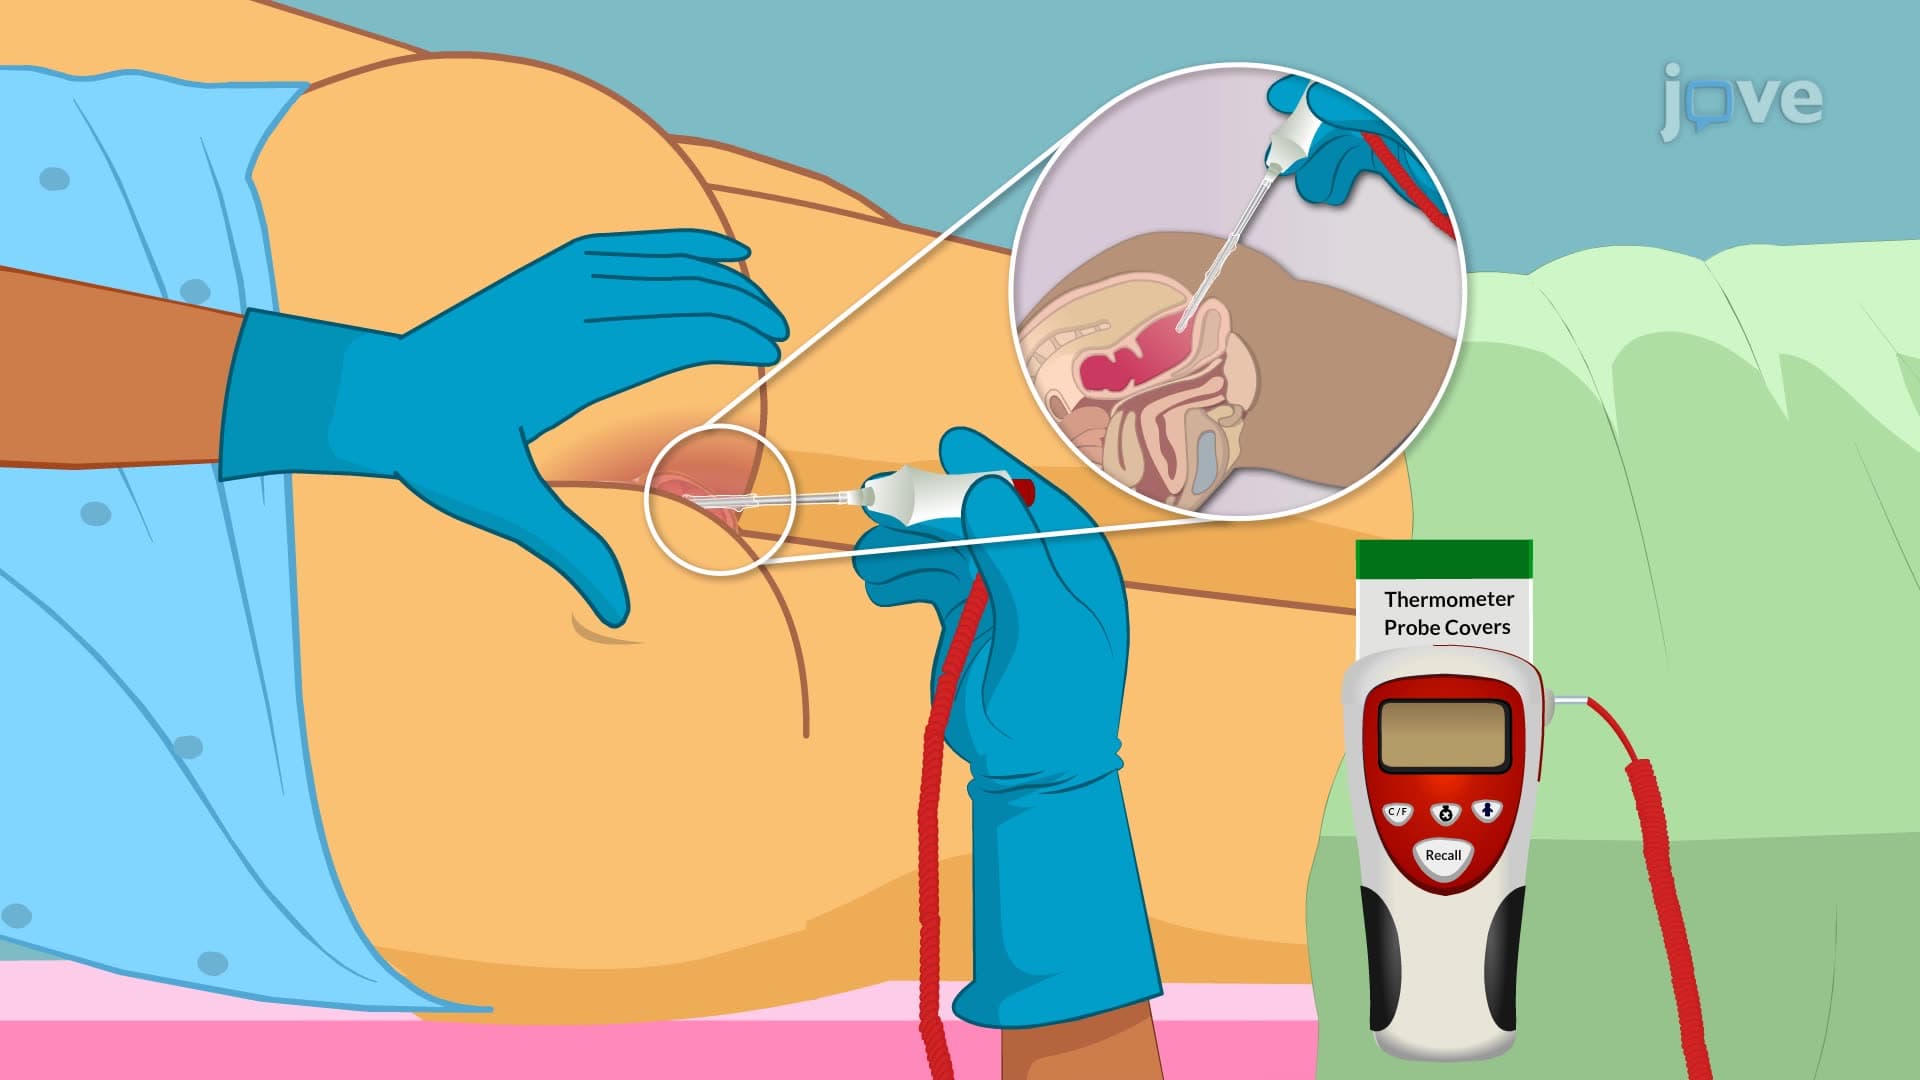
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:26
Inflammatory Bowel Disease I: Introduction
 01:30
Serum Laboratory Studies, Stool Test, Breath Test