Related Experiment Video
Updated: Jul 2, 2026


Evaluation of Keratinocyte Proliferation on Two- and Three-dimensional Type I Collagen Substrates
Published on: April 22, 2019
[Type I and II collagens and mast cells expression in the skin lesions from the patients with localized scleroderma]
Dorota Wielowieyska-Szybińska1, Anna Wojas-Pelc, Grzegorz Dyduch
1Katedra i Klinika Dermatologii, Collegium Medicum, Uniwersytet Jagielloński, Kraków.

Abstract:
Morphea en plaques (MP) and atrophoderma Pasini-Pierini (APP) are by most researchers regarded as specific types of localized scleroderma (LS), but their clinical picture is completely different. Fibrosing process is very complicated, and is connected with presence of collagen (I and III type) and extracellulare matrix deposits in the dermis. Probably mast cells also play an important role in this process. The aim of the study is estimation of the expression of type I and III collagens and number of mast cells in lesions from patients with APP and MP. 36 patients were enrolled to the study. Immunohistochemical tests were performed to observe presence of type I and III collagens and presence of mast cells in the dermis. We observed that patients with APP showed lower expression of the I and III type collagens in the dermis than patients with MP. Expression of I type collagen decreases with time only among patients with MP. There was no similar relation for type III collagen. High and very high expression of type I and III collagen was observed more frequently in the active phase of the disease in patients with MP. Number of mast cells was higher in patients with APP than in MP. The number of the mast cells increases with time of disease in patients with MP, and there is correlation between high number of mast cells and low expression of the I and III collagens in the patients with MP.
Insights
Localized scleroderma subtypes, morphea en plaques (MP) and atrophoderma Pasini-Pierini (APP), show distinct collagen and mast cell differences. MP exhibits higher collagen expression, while APP has more mast cells, indicating varied fibrotic processes.
Area of Science:
- Dermatology
- Pathology
- Immunohistochemistry
Background:
- Morphea en plaques (MP) and atrophoderma Pasini-Pierini (APP) are classified as localized scleroderma (LS) types.
- Despite classification, MP and APP present distinct clinical manifestations.
- Both conditions involve complex fibrotic processes in the dermis, including collagen and extracellular matrix deposition, with potential mast cell involvement.
Purpose of the Study:
- To quantitatively assess the expression of type I and III collagens.
- To determine the number of mast cells within skin lesions of patients diagnosed with APP and MP.
- To investigate the relationship between collagen expression, mast cell counts, and disease characteristics in APP and MP.
Main Methods:
- Immunohistochemical analysis was employed to detect and quantify type I and III collagens.
- Mast cell populations were identified and counted in dermal biopsies.
- 36 patients with either APP or MP were included in the study.
Main Results:
- Patients with APP demonstrated significantly lower expression of type I and III collagens compared to those with MP.
- Type I collagen expression decreased over time exclusively in MP patients; no similar trend was observed for type III collagen.
- High collagen expression (types I and III) was more prevalent in the active disease phase of MP.
- Mast cell counts were elevated in APP patients relative to MP patients.
- In MP, mast cell numbers increased with disease duration, correlating with lower collagen expression.
Conclusions:
- Distinct differences in collagen deposition and mast cell infiltration exist between APP and MP.
- The findings suggest divergent pathomechanisms underlying the fibrotic processes in these localized scleroderma subtypes.
- Further research into the roles of collagen and mast cells could inform targeted therapeutic strategies for MP and APP.

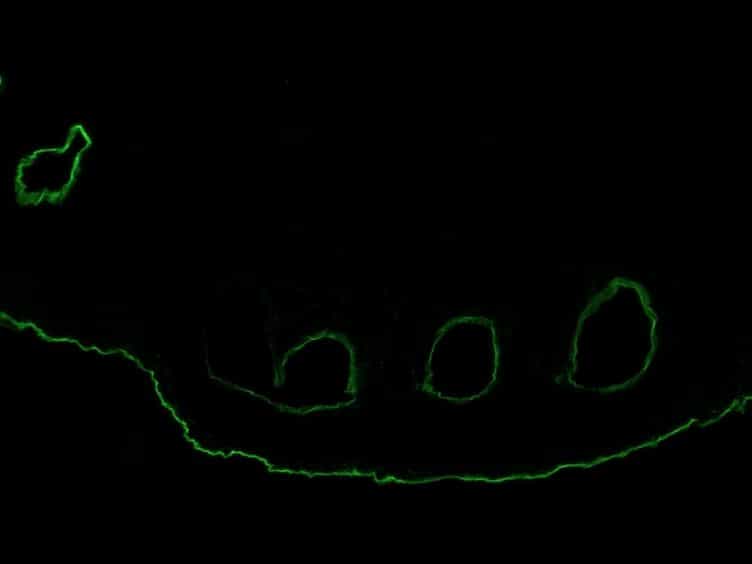
Related Concept Videos
 01:11
Fibril-associated Collagen
For example, the type II collagen fibrils in cartilage have covalently bound type IX fibril-associated collagens at regular intervals. Other types of fibril-associated collagens are...
 01:05
Type IV Collagen of Basal Lamina
A type IV collagen molecule has six alpha chains which can exist in...
 01:13
Collagens are the Major Structural Proteins of ECM
Connective tissue proper includes loose...
 01:28
Phases of Wound Repair
Formation of Blood Clot
In case of deep injuries, trauma to blood vessels results in blood loss. In the meantime, phospholipids released from the ruptured endothelial cellular membrane are converted into arachidonic...
 01:11
Introduction to Connective Tissues
 01:15
Reticular Dermis
Reticular Layer
Underlying the papillary layer is the much thicker reticular layer, composed of dense, irregular connective...