Related Experiment Video
Updated: Jul 1, 2026

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
[Obtain best usage of meropenem dose in severe infections. Results of an observational multicenter study]
B Alvarez-Sánchez1, F Alvarez-Lerma, Jl Romero
1Servicio de Medicina Intensiva, Hospital General Universitario, Alicante. alvarez_ber@gva.es

Objective:
To describe the effectiveness and tolerability of the dose adjustment of meropenem in empirical treatment of nosocomial infections in critically-ill patients admitted to intensive care medicine services.
Methods:
Prospective, observational and multicenter study in patients admitted to 17 intensive care medicine services with nosocomial infection, who were initially treated with meropenem, 1 g every 8 h, were eligible. The initial dose was adjusted to 0.5 g every 8 h if there were: a) a favorable clinical course, and b) microbiological isolation of meropenem-susceptible pathogens or absence of pathogens in cultures.
Results:
Ninety-two patients in whom meropenem doses were adjusted to 0.5 g every 8 h were included. Ventilator-associated pneumonia followed by bacteremia was the most frequently treated infections. Microbiological studies were positive in 53 patients, with a predominance of gram-positive bacteria (53.7%), especially methicillin-susceptible Staphylococcus aureus, followed by gram-negative bacteria (42.7 %). A total of 18 patients were not evaluable at the end of treatment. Sixty-seven (90.5 %) of the 74 evaluable patients had a favorable clinical course (54 patients cured and 13 improved). In 50 out of 53 microbiologically evaluable cases, eradication or apparent eradication of initial microorganisms was achieved. In 3 cases, the initial pathogen persisted: Acinetobacter baumannii (2 cases) and Pseudomonas aeruginosa (1 case). On three occasions, new pathogens developed during treatment: A. baumannii (2 cases) and methicillin-resistant S. aureus (1 case). Adverse events occurred in 3 patients (4%), none of which was considered severe, and withdrawal of meropenem was not necessary. A total of 25 (27.2 %) patients died, three of them in relation to the infectious process.
Conclusions:
Dose adjustment of meropenem to 0.5 g every 8 h is a useful tool in the treatment of severe nosocomial infections in patients admitted to services of intensive care medicine except in cases in which causative pathogens are non-fermenting Gram-negative bacteria.
Insights
Reducing meropenem dosage to 0.5 g every 8 hours effectively treats severe nosocomial infections in critically-ill patients. This dose adjustment is safe and beneficial, except when non-fermenting Gram-negative bacteria are the cause.
Area of Science:
- Infectious Diseases
- Critical Care Medicine
- Pharmacology
Background:
- Nosocomial infections pose a significant threat to critically-ill patients in intensive care units.
- Empirical antibiotic treatment, including meropenem, is crucial but requires careful dose optimization.
- Understanding the effectiveness and tolerability of meropenem dose adjustments is vital for improving patient outcomes.
Purpose of the Study:
- To evaluate the effectiveness and tolerability of adjusting meropenem dosage in critically-ill patients with nosocomial infections.
- To assess the clinical and microbiological outcomes following meropenem dose reduction.
- To identify specific pathogens or conditions where meropenem dose adjustment may be less effective.
Main Methods:
- A prospective, observational, multicenter study involving 17 intensive care units.
- Patients initially treated with meropenem (1 g every 8 hours) for nosocomial infections were included.
- Dose was adjusted to 0.5 g every 8 hours based on favorable clinical course and susceptible pathogens or absence of pathogens.
Main Results:
- Ninety-two patients had their meropenem dose adjusted; ventilator-associated pneumonia and bacteremia were common infections.
- A high clinical success rate of 90.5% was observed in evaluable patients (74), with 54 cured and 13 improved.
- Microbiological eradication was achieved in 50 out of 53 cases; adverse events were rare (4%) and not severe.
Conclusions:
- Meropenem dose adjustment to 0.5 g every 8 hours is a valuable strategy for treating severe nosocomial infections in intensive care settings.
- This dose reduction demonstrates good tolerability and effectiveness, leading to favorable clinical outcomes.
- The strategy should be used cautiously in cases involving non-fermenting Gram-negative bacteria, as they may persist or new resistant pathogens may emerge.
Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:25
Clinical Significance of Antibiotic Resistance
 01:15
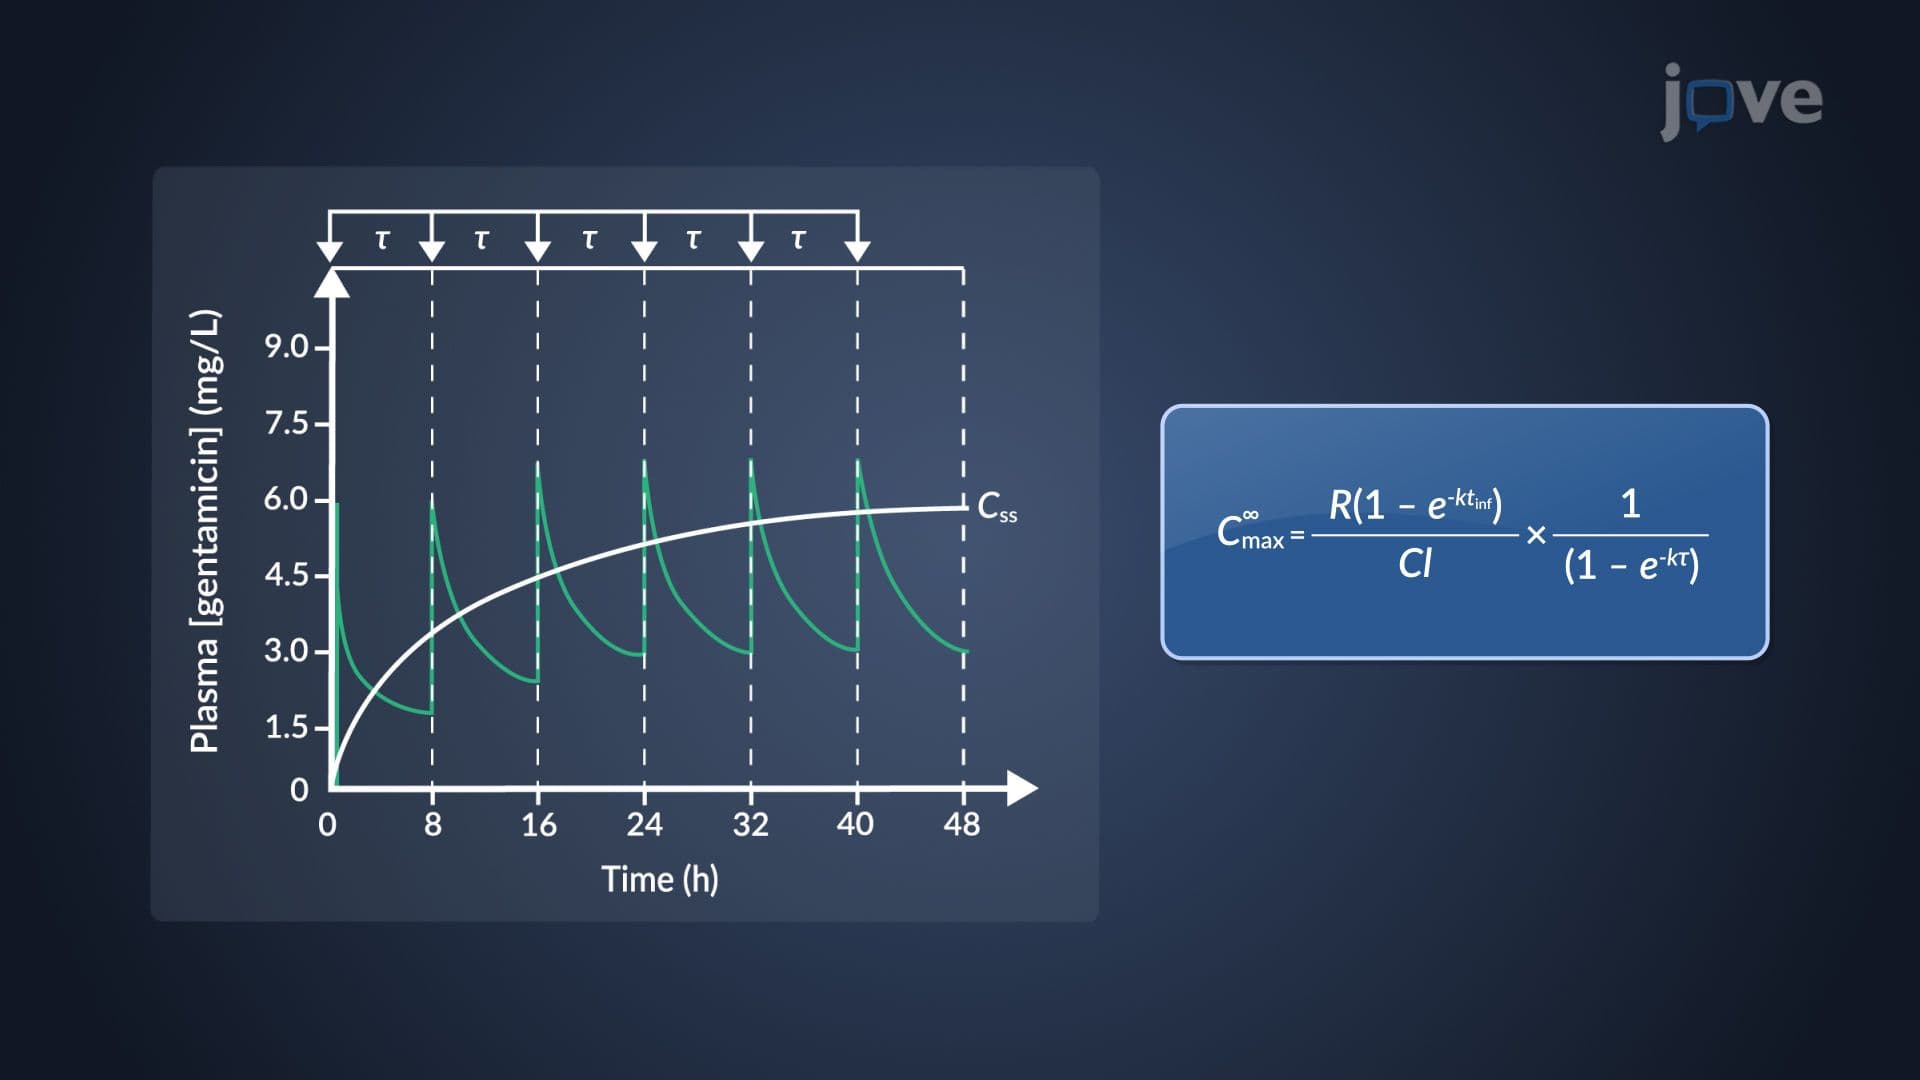
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Antimicrobial Effectiveness
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:25
Mechanism of Antibiotic Resistance in MRSA