Related Experiment Video
Updated: Jun 30, 2026
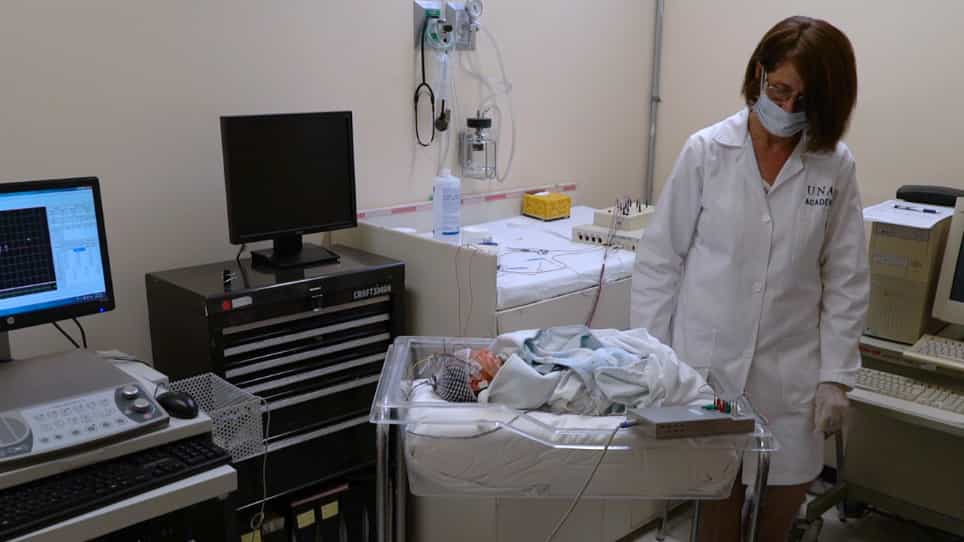

How to Obtain Reliable Visual Event-related Potentials in Newborns
Published on: October 24, 2019
Abnormal fast activity in infancy with paroxysmal downwards gaze
Harumi Yoshinaga1, Katsuhiro Kobayashi, Fumika Endo
1Department of Child Neurology, Okayama University Graduate School of Medicine and Dentistry, Shikatacho 2-5-1, Okayama, Japan. magenta@md.okayama-u.ac.jp

Insights
Paroxysmal downwards gaze (PDG) in infants, associated with occipital abnormal fast activity (AFA) on EEG, may indicate occipital region damage. This finding suggests PDG with AFA is a risk factor for developing West syndrome.
Area of Science:
- Neurology
- Pediatrics
- Epileptology
Background:
- Paroxysmal downwards gaze (PDG) is an uncommon clinical sign in infants.
- The association between PDG, electroencephalogram (EEG) findings, and neurodevelopmental outcomes requires further elucidation.
Purpose of the Study:
- To investigate the clinical significance of PDG in infants.
- To explore the relationship between PDG, EEG abnormalities, and the subsequent development of West syndrome.
Main Methods:
- Case series of 8 infants presenting with PDG.
- Clinical observation and video-EEG monitoring.
- Analysis of EEG for interictal spikes and abnormal fast activity (AFA), particularly in the occipital region.
Main Results:
- PDG onset ranged from 1 to 5 months corrected age.
- 7/8 infants had interictal spikes on EEG; 5/8 showed occipital AFA.
- 5/8 infants with PDG and occipital AFA later developed West syndrome.
- PDG was differentiated from subtle epileptic seizures via video-EEG monitoring.
Conclusions:
- PDG, especially when accompanied by occipital AFA on EEG, may signify occipital region damage.
- PDG with occipital AFA is proposed as a potential risk factor for West syndrome development.
- Early identification of PDG with occipital AFA may aid in predicting West syndrome.
Abstract:
We report here on 8 infants who showed paroxysmal downwards gaze (PDG). The time of initial appearance of PDG ranged from one month to five months (mean: 2.7 months) of corrected age. Seven out of eight patients showed interictal spikes in EEG, so they were started on prophylactic therapy with antiepileptic drugs. In five of the eight patients, PDG ceased, either spontaneously or with antiepileptic drug treatment, by four to eight months of corrected age. Six out of eight patients showed localized spikes and peculiar abnormal fast activity (AFA) in the occipital area and five of these patients later developed West syndrome. These AFA were observed on EEGs recorded at the time of initial PDG appearance, before hypsarrhythmia was observed and before tonic spasms appeared. We were able to exclude the possibility that PDG was a subtle epileptic seizure by confirming the temporal discordance between individual episodes of PDG and AFA with video-EEG monitoring. Yet topographic data showed that AFA in these patients was characteristically located in the occipital area, with a distribution similar to that of the fast activity which accompanied the tonic spasms that later developed in these patients. As a risk factor for developing WS, we propose the clinical symptom of PDG with characteristic occipital AFA visible in the EEG, both of which represent damage to the occipital region including the optic radiation.


Related Concept Videos
 01:14
Piaget's Stage 1 of Cognitive Development
Exploration...
 01:15
REM Sleep Behavior Disorder
RBD is significantly associated with...