Related Experiment Video
Updated: Jun 29, 2026

Multi-exon Skipping Using Cocktail Antisense Oligonucleotides in the Canine X-linked Muscular Dystrophy
Published on: May 24, 2016
Calcium antagonists for Duchenne muscular dystrophy
Margaret F Phillips1, Rosaline Quinlivan
1Division of Rehabilitation Medicine, University of Nottingham, Arkwright House, Derby City Hospital, Derby, UK, DE22 3NE. margaret.phillips@nottingham.ac.uk

Background:
Duchenne muscular dystrophy (DMD) is a progressive muscle condition starting in childhood, leading to severe disability and a shortened life span. It is due to severe deficiency of the protein dystrophin which performs both structural and signalling roles within skeletal and cardiac myocytes. Calcium accumulates in dystrophic muscle cells and plays a role in cell damage. It has been hypothesised that use of calcium antagonists might reduce this calcium load and its toxic effect on muscle cells.
Objectives:
To evaluate the effects of calcium antagonists on muscle function and muscle strength in people with DMD.
Search Strategy:
The Cochrane Neuromuscular Disease Group Trials Register (February 2008), MEDLINE (from January 1950 to March 2008) and EMBASE (from January 1947 to March 2008) were searched. Search terms were 'calcium antagonists' or 'calcium channel blocker' or 'dantrolene' or 'verapamil' or 'nifedipine' or 'flunarizine' or 'diltiazem' or 'amlodipine' or 'nicardipine' and 'Muscular Dystrophy, Duchenne'. Bibliographies in reports of any trials were also searched.
Selection Criteria:
All randomised or quasi-randomised controlled trials of any calcium antagonist in people with DMD.
Data Collection And Analysis:
Both authors assessed all identified trials for inclusion in the study on the basis of whether they fulfilled the selection criteria. Both authors extracted data from the trials and assessed the methodological quality. Had there been more than one trial of the same intervention and outcome of sufficient methodological quality, we had planned to undertake a meta-analysis.
Main Results:
Five randomised or quasi-randomised double-blind trials fulfilled the selection criteria, but were not sufficiently comparable to undertake a meta-analysis. The drugs studied were verapamil (8 participants), diltiazem (56 participants), nifedipine (105 participants) and flunarizine (27 participants). There were limitations in the description of blinding and randomisation, and definition of outcome measures. One trial, using verapamil, showed a difference between groups in muscle force measured by ergometry, but also revealed cardiac side effects. The numbers of people included in the trials were low, and so the studies may not have included enough people for sufficient power to detect small differences in muscle force or function between placebo and control groups. In addition, calcium antagonists were in an early stage of development and some of the second generation drugs that have a better side effect profile, such as amlodipine, have not been studied.
Authors' Conclusions:
There is no evidence to show a significant beneficial effect of calcium antagonists on muscle function in DMD.
Insights
Calcium antagonists do not show significant benefits for muscle function in Duchenne muscular dystrophy (DMD). Further research is needed as current studies are limited and some newer drugs haven
Area of Science:
- Neurology
- Pharmacology
- Genetics
Background:
- Duchenne muscular dystrophy (DMD) is a severe childhood-onset genetic disorder characterized by progressive muscle degeneration.
- DMD results from a deficiency in dystrophin, a protein crucial for muscle cell integrity.
- Intracellular calcium accumulation contributes to muscle cell damage in DMD.
Purpose of the Study:
- To assess the efficacy of calcium antagonists in improving muscle function and strength in individuals with DMD.
- To review existing randomized controlled trials investigating calcium antagonists for DMD.
Main Methods:
- Comprehensive literature search of Cochrane Neuromuscular Disease Group Trials Register, MEDLINE, and EMBASE up to March 2008.
- Inclusion criteria: randomized or quasi-randomized controlled trials of any calcium antagonist in DMD patients.
- Data extraction and quality assessment by two independent reviewers; meta-analysis planned if feasible.
Main Results:
- Five trials (verapamil, diltiazem, nifedipine, flunarizine) met inclusion criteria but were not comparable for meta-analysis.
- Trials had limitations in blinding, randomization, and outcome definitions; participant numbers were often low.
- One verapamil trial suggested a muscle force difference but noted cardiac side effects; newer agents like amlodipine were not studied.
Conclusions:
- Current evidence does not support a significant beneficial effect of calcium antagonists on muscle function in DMD.
- The limited power and methodological issues in existing trials necessitate further investigation.
- Future research could explore newer calcium antagonists with potentially improved safety profiles.


Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:21
Satellite Stem Cells and Muscular Dystrophy
 01:17
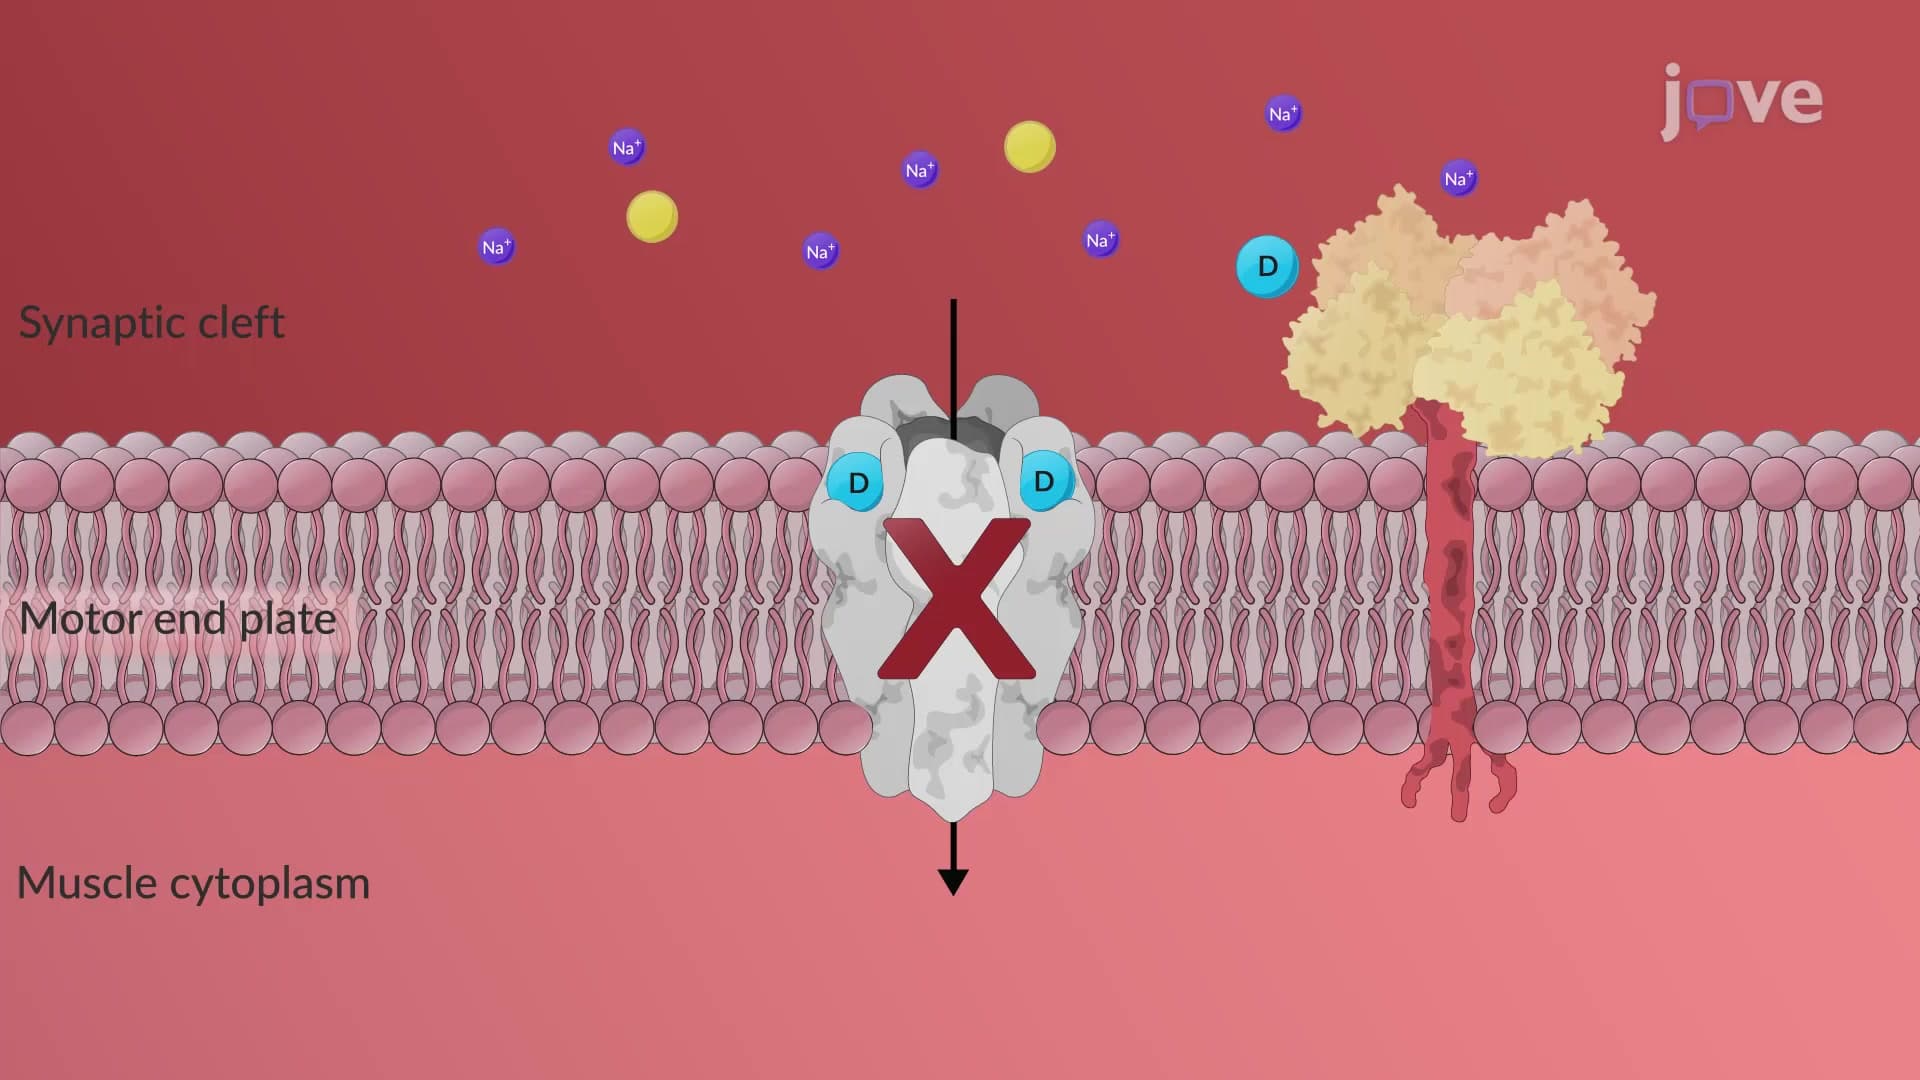
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses