Related Experiment Video
Updated: Jun 29, 2026

Left Atrial Stenosis Induced Pulmonary Venous Arterialization and Group 2 Pulmonary Hypertension in Rat
Published on: November 18, 2018
Persistent left superior vena cava: a case report and review of literature
Sandeep K Goyal1, Sujeeth R Punnam, Gita Verma
1Department of Medicine, Section of Cardiology, Boston University School of Medicine, Boston, MA, USA. sandeep.goyal@bmc.org

Insights
Persistent left superior vena cava (PLSVC) is a rare congenital vascular anomaly. Its presence can complicate cardiac access and requires specific diagnostic considerations.
Area of Science:
- Cardiovascular Medicine
- Congenital Anomalies
- Vascular Biology
Background:
- Persistent left superior vena cava (PLSVC) arises from the failure of the left superior cardinal vein to regress during embryonic development.
- This congenital vascular anomaly is uncommon but clinically significant.
Observation:
- PLSVC often occurs in isolation but can be associated with other cardiac defects such as atrial septal defect and bicuspid aortic valve.
- A dilated coronary sinus on echocardiography may indicate the presence of PLSVC.
Findings:
- The diagnosis of PLSVC is typically confirmed using saline contrast echocardiography.
- PLSVC can impede standard right-heart access through the left subclavian vein, a common approach for pacemakers and Swan-Ganz catheters.
Implications:
- Awareness of PLSVC is crucial for interventional cardiologists and cardiac surgeons.
- Accurate diagnosis and understanding of PLSVC's impact on cardiac access are essential for patient management and procedural planning.
Abstract:
Persistent left superior vena cava is rare but important congenital vascular anomaly. It results when the left superior cardinal vein caudal to the innominate vein fails to regress. It is most commonly observed in isolation but can be associated with other cardiovascular abnormalities including atrial septal defect, bicuspid aortic valve, coarctation of aorta, coronary sinus ostial atresia, and cor triatriatum. The presence of PLSVC can render access to the right side of heart challenging via the left subclavian approach, which is a common site of access utilized when placing pacemakers and Swan-Ganz catheters. Incidental notation of a dilated coronary sinus on echocardiography should raise the suspicion of PLSVC. The diagnosis should be confirmed by saline contrast echocardiography.
Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the middle...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:19
Veins of Thorax
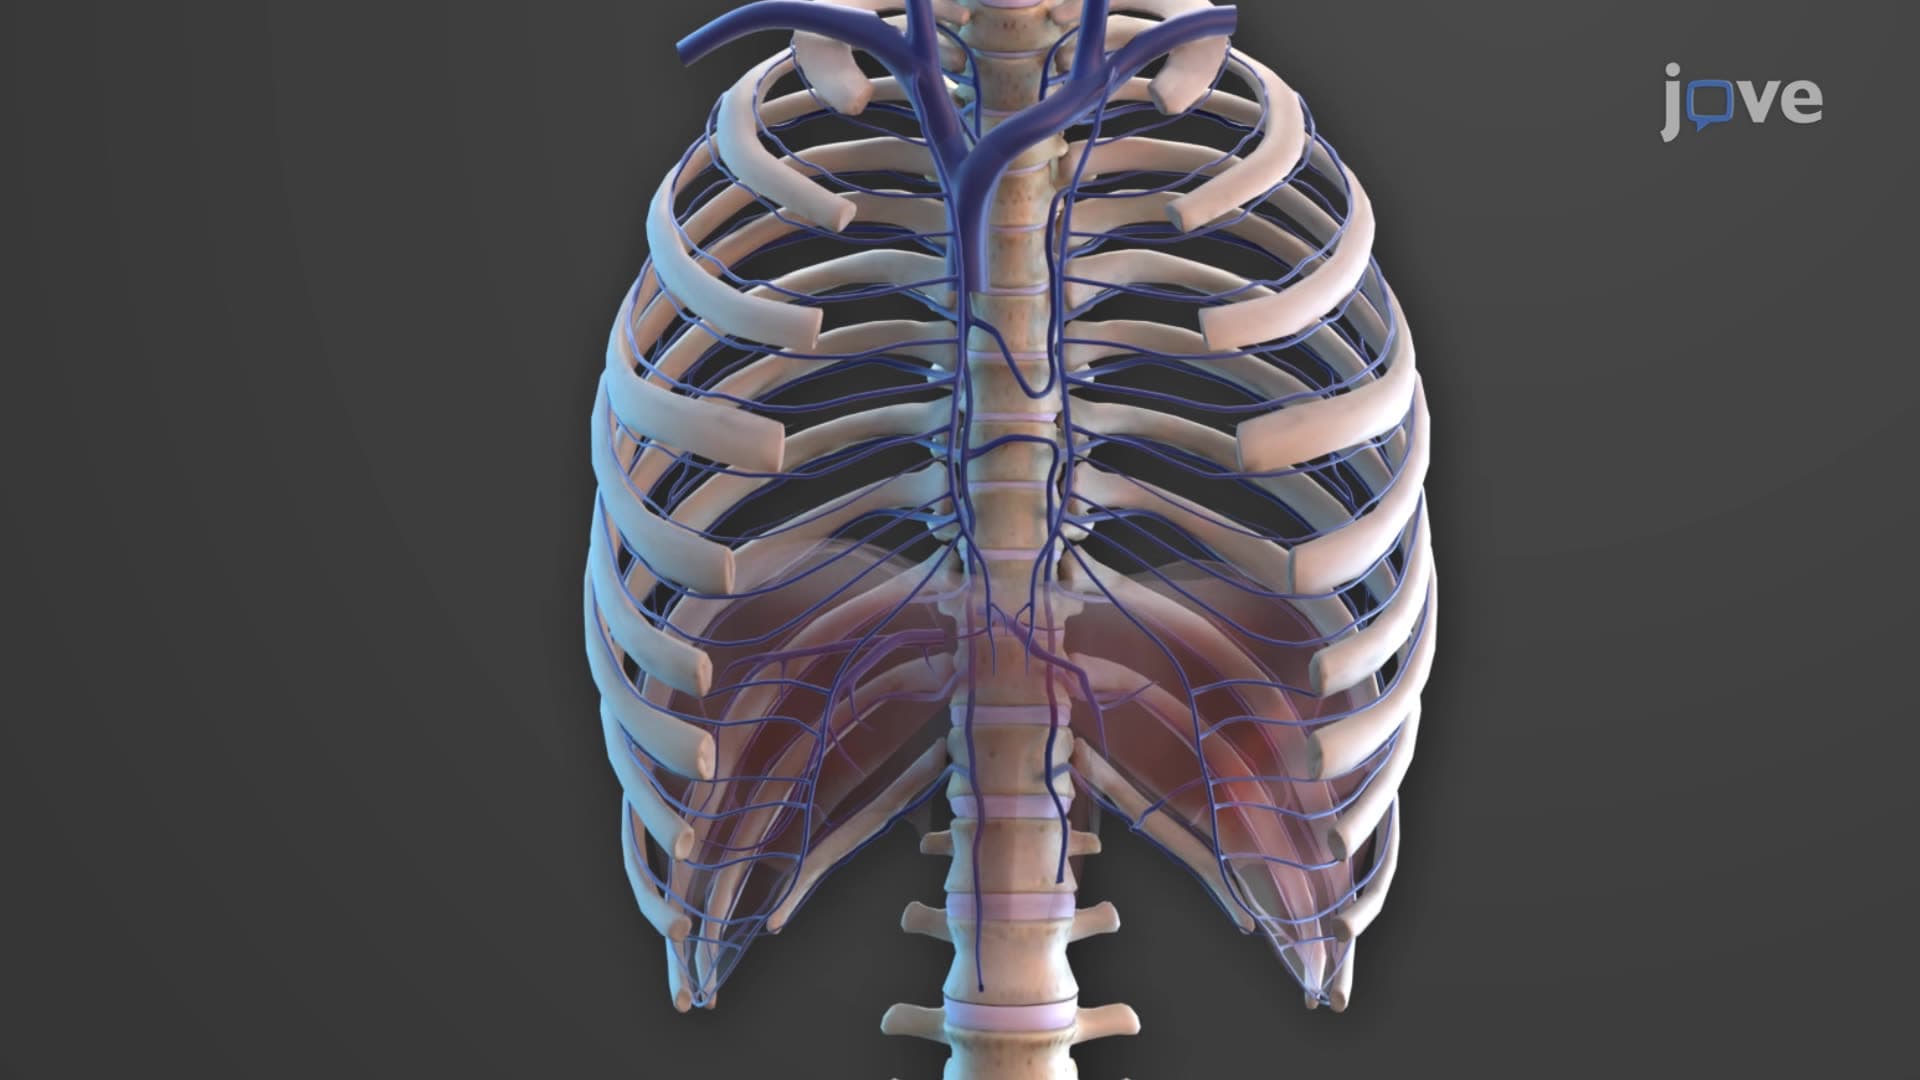
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care