Related Experiment Video
Updated: Jun 29, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
[Skeletal mineralization in a prepubertal female population affected by juvenile idiopathic arthritis]
A Lurati1, R Cimaz, M Gattinara
1Ospedale Fornaroli, Unità di Reumatologia, Magenta, Milano. alfredomaria.lurati@email.it

Background:
Puberty is an essential step in bone mass accrual. Growth failure and impairment of sexual maturation are frequent manifestations of chronic illnesses in the paediatric population, and chronic rheumatologic disorders such as juvenile idiopathic arthritis (JIA) are no exception to this.
Methods:
The aim of our study was to prospectively evaluate bone density in adolescent females with JIA, and to correlate the results with clinical variables, in particular with age at menarche. Lumbar spine (L2-L4) area bone mineral density (aBMD) (assessed by Dual X-ray Absorbiometry, DXA) was monitored every 6-12 months in a group of 38 girls with JIA. The evaluated bone density accrual during the peripubertal time as well as absolute and relative (Z-score) aBMD in relationship with age at menarche, JIA subset, disease activity (as evaluated by ESR and Hgb), corticosteroid and methotrexate treatment (mean pro kg daily dose, cumulative dose) was assessed. Height, body mass index (BMI), bone mass content (BMC) values were also collected. Volumetric BMD (vBMD) evaluated with a geometric correction formula has been calculated and compared to aBMD.
Results:
Patients were divided into two groups: - group I included girls with menarche age within normal limits for Italian standards; - group II included girls with delayed menarche. The BMD values and Z scores in group I were not significantly different to normal population. The BMD values and Z scores in group II were significantly decreased when compared to the normal population (p<0.001). With a multivariate analysis only age at menarche seemed independently related to peripubertal mineralization (p=0.025, r between -0.65 and -0.75). With a binary logistic analysis only disease activity (ESR and Hgb values) seems independently related to a menarche delay (1.24+/-0.4 for each mm/h).
Conclusion:
Our data show a critical role for disease activity in determination of a regular pubertal onset and an optimal bone density achievement.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:27
Growth of Cartilage and Bone Tissue
 01:24
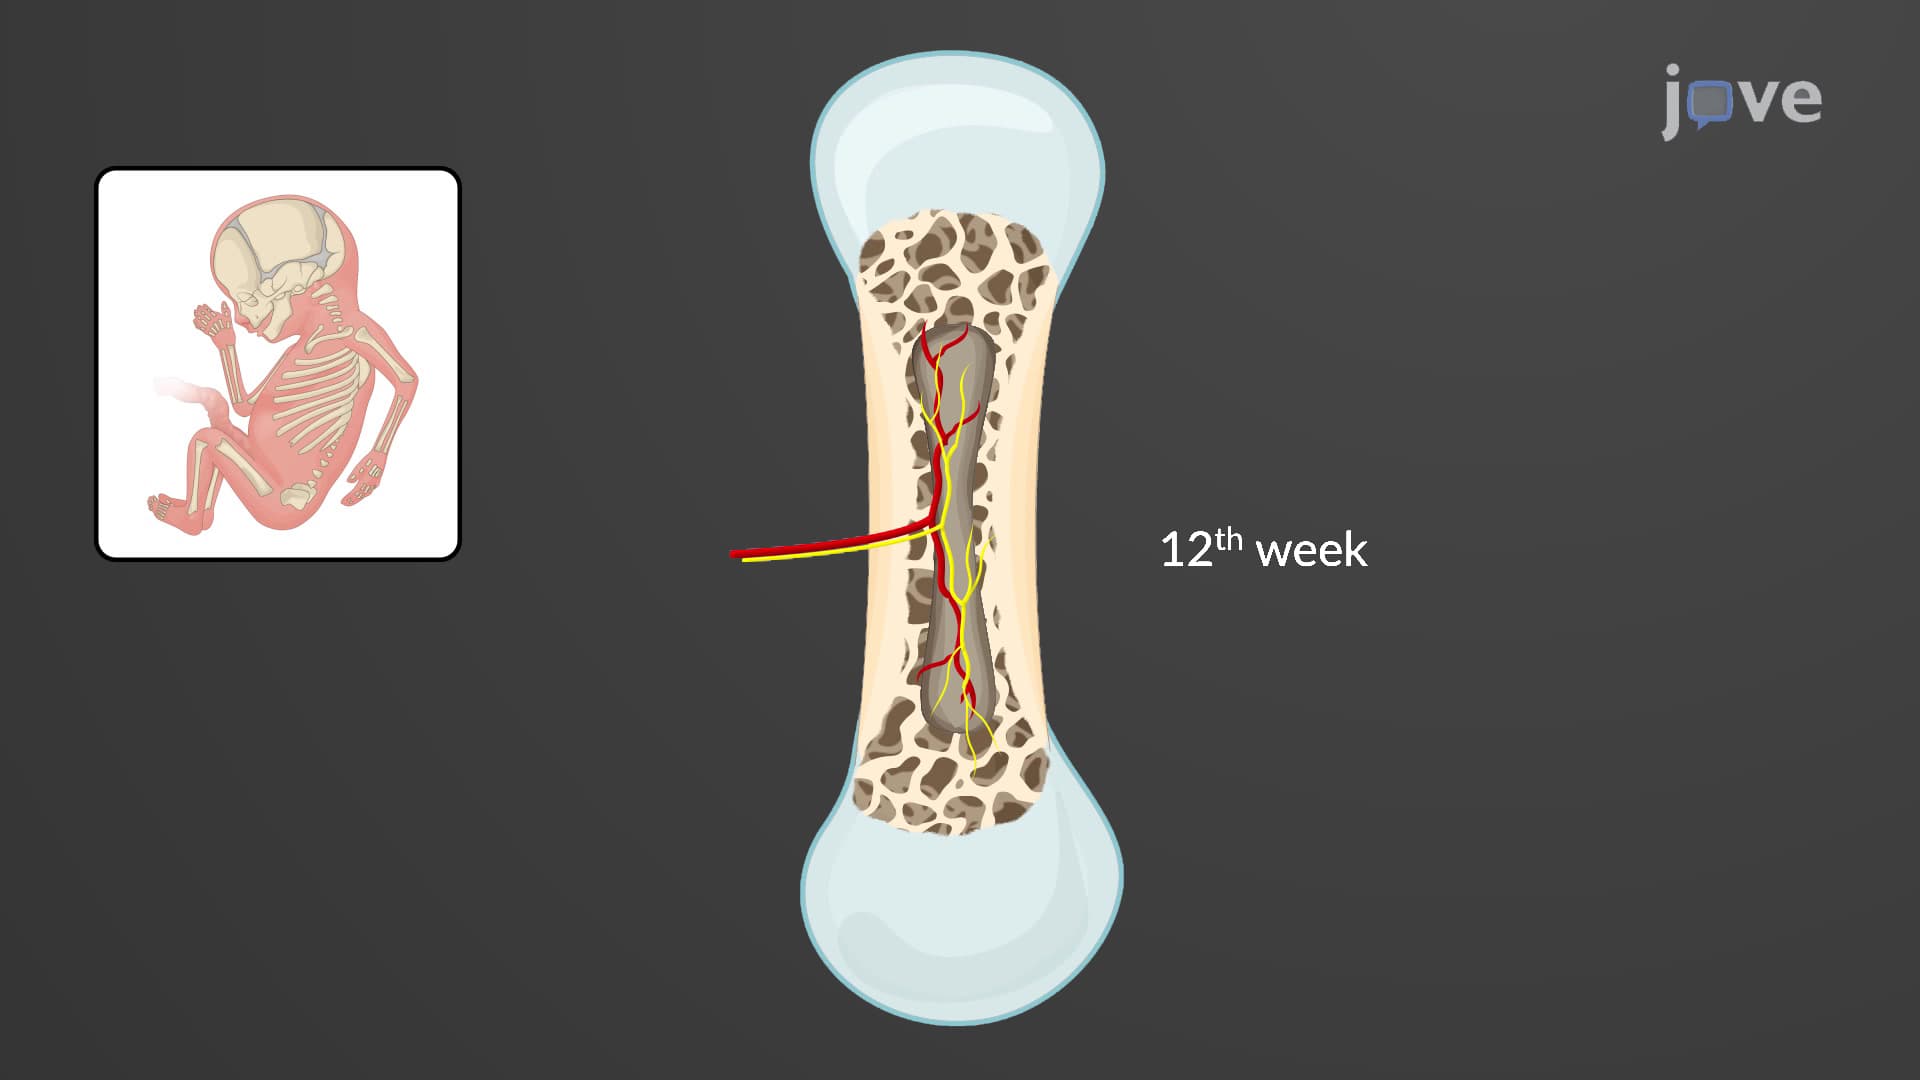
Bone Formation by Endochondral Ossification
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:02
What is the Skeletal System?