Related Experiment Video
Updated: Jun 28, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Synchronous and metachronous adenocarcinomas of the large intestine
N Tziris1, J Dokmetzioglou, K Giannoulis
1Third Surgical Department, Aristotle University of Thessaloniki, AHEPA University Hospital, Thessaloniki, Greece.

Background And Aim:
The synchronous and consecutive (metachronous) development of two or more primary adenocarcinomas accounts for 3 to 5% of cases of colorectal cancer. Aim of this study is to review our experience in the management of patients with synchronous and metachronous lesions, and reach conclusions regarding their optimal diagnosis, treatment and follow-up.
Patients And Methods:
Between 1987 and 2004, 12 patients (seven men and five women, mean age 67.5 years, range 47-83 years) with synchronous (three patients) and metachronous (nine patients) lesions were treated, comprising 4.3% of all patients submitted to surgery for colorectal cancer. The diagnosis lag for metachronous lesions ranged from 1.5 to 14 years. All three patients with synchronous cancers had two lesions.
Results:
Staging colonoscopy and abdominal CT was conducted in 10 patients while the remaining two underwent only abdominal CT due to their critical condition at presentation. Surgery had curative intent in 10 patients and palliative in two. The mean postoperative hospital stay was 21 days (10-49 days). The postoperative mortality was zero. Patients survival after curative procedures was 80% for the first year, 60% for the third and 50% for the fifth year. After palliative surgery, survival was 50% for the first year, and zero for the third.
Conclusions:
Patients with colorectal cancer must be followed up regularly after surgery. Follow up aims at early diagnosis and treatment of metachronous lesions that can appear many years after diagnosis of the primary lesion. Preoperative colonoscopy is an invaluable diagnostic (biopsy) and staging (exclusion of synchronous lesions, localization of the primary) modality, dictating the surgical approach. Additionally, it contributes to cancer prevention allowing the discovery and removal of small polyps before their transformation.

Related Concept Videos
 01:26
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:29
Intestinal Obstruction I: Introduction
 01:09
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:24
Cellular Adaptation IV: Dysplasia and Metaplasia
 02:30
Metastasis
Epithelial-to-Mesenchymal Transition
The epithelial-to-mesenchymal transition or EMT is a developmental process commonly observed in wound healing, embryogenesis, and cancer metastasis. EMT is induced by transforming growth factor-beta (TGF-β) or receptor tyrosine kinase (RTK) ligands, which further...
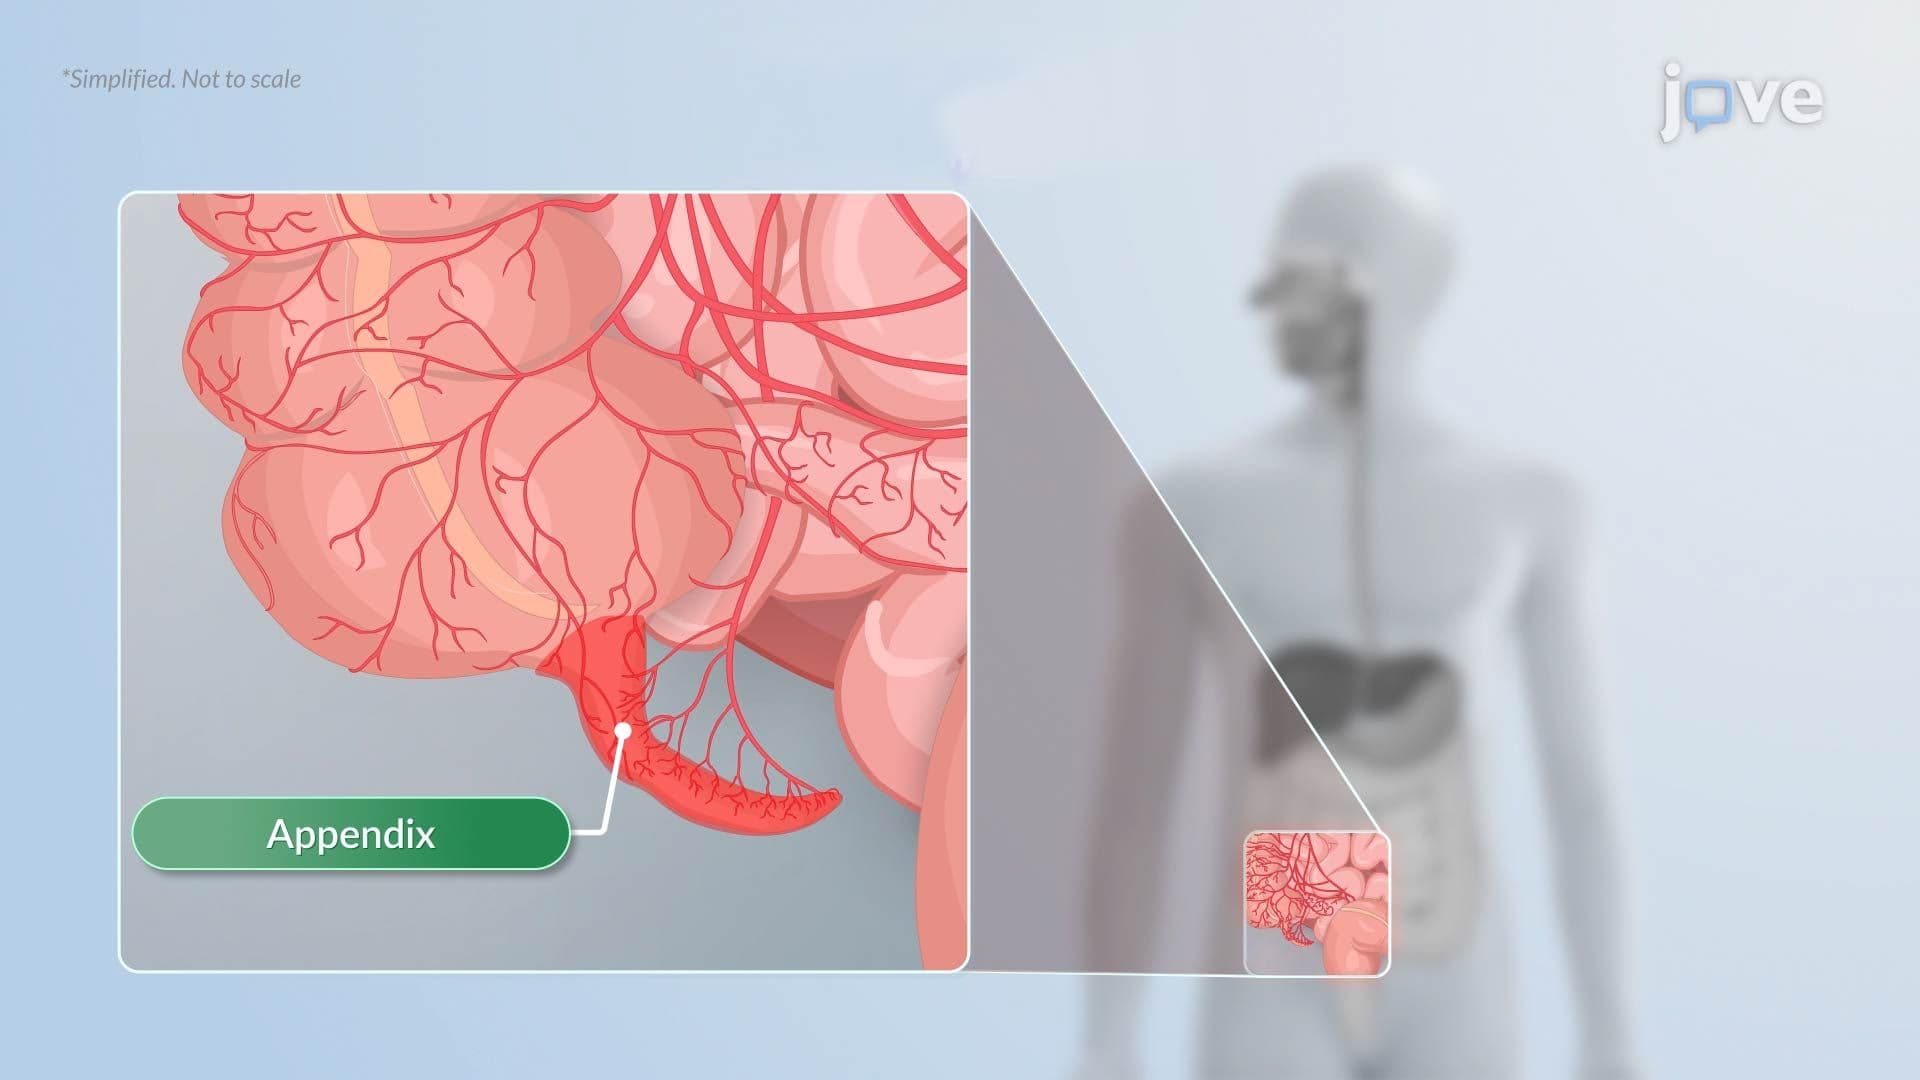 01:19
Appendicitis