Related Experiment Video
Updated: Jun 28, 2026


Auricular Point Acupressure Therapy: A Safe and Effective Treatment for Postsurgical Abortion Recovery
Published on: February 3, 2026
Scheduled and unscheduled bleeding patterns with two combined hormonal contraceptives: application of new
Raymond Moss Hampton1, Alan C Fisher, Susan Pagano
1Texas Tech University School of Medicine, Odessa, Texas, USA.

Objective:
To reassess and compare cycle control attained with two combined hormonal contraceptives, norgestimate (NGM)/ethinyl estradiol (EE) 25 microg and norethindrone acetate (NETA)/EE 20 microg, by new general criteria recommendations for all combined hormonal contraceptives.
Design:
Analysis of bleeding data for cycles 1-6 from a randomized, multicenter trial.
Setting:
221 North American centers.
Patient(S):
Healthy, sexually active women (18-45 years old).
Intervention(S):
NETA/EE: 1 mg NETA/20 microg EE, days 1-21 of each cycle and 75 mg of ferrous fumarate, days 22-28; NGM/EE: triphasic NGM in 7-day increments (days 1-7: 180 microg; days 8-14: 215 microg; days 15-21: 250 microg) and 25 microg EE, placebo on days 22-28.
Main Outcome Measure(S):
Cycle control evaluated from patients' daily diaries.
Result(S):
For cycles 1-6, there was a statistically significant lower incidence of unscheduled bleeding/spotting with NGM/EE 25 microg (range 21.0%-34.4%) than with NETA/EE 20 microg (range 33.0%-46.6%). Of the women who had unscheduled bleeding/spotting, the mean number of days per cycle of bleeding/spotting was comparable. A statistically significant higher incidence of scheduled bleeding was seen with NGM/EE 25 microg (95.2%-97.5%) than with NETA/EE 20 microg (78.5%-84.2%).
Conclusion(S):
The NGM/EE 25 microg has a lower incidence and comparable length of unscheduled bleeding and a higher incidence of scheduled bleeding than NETA/EE 20 microg in this post hoc analysis.
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:21
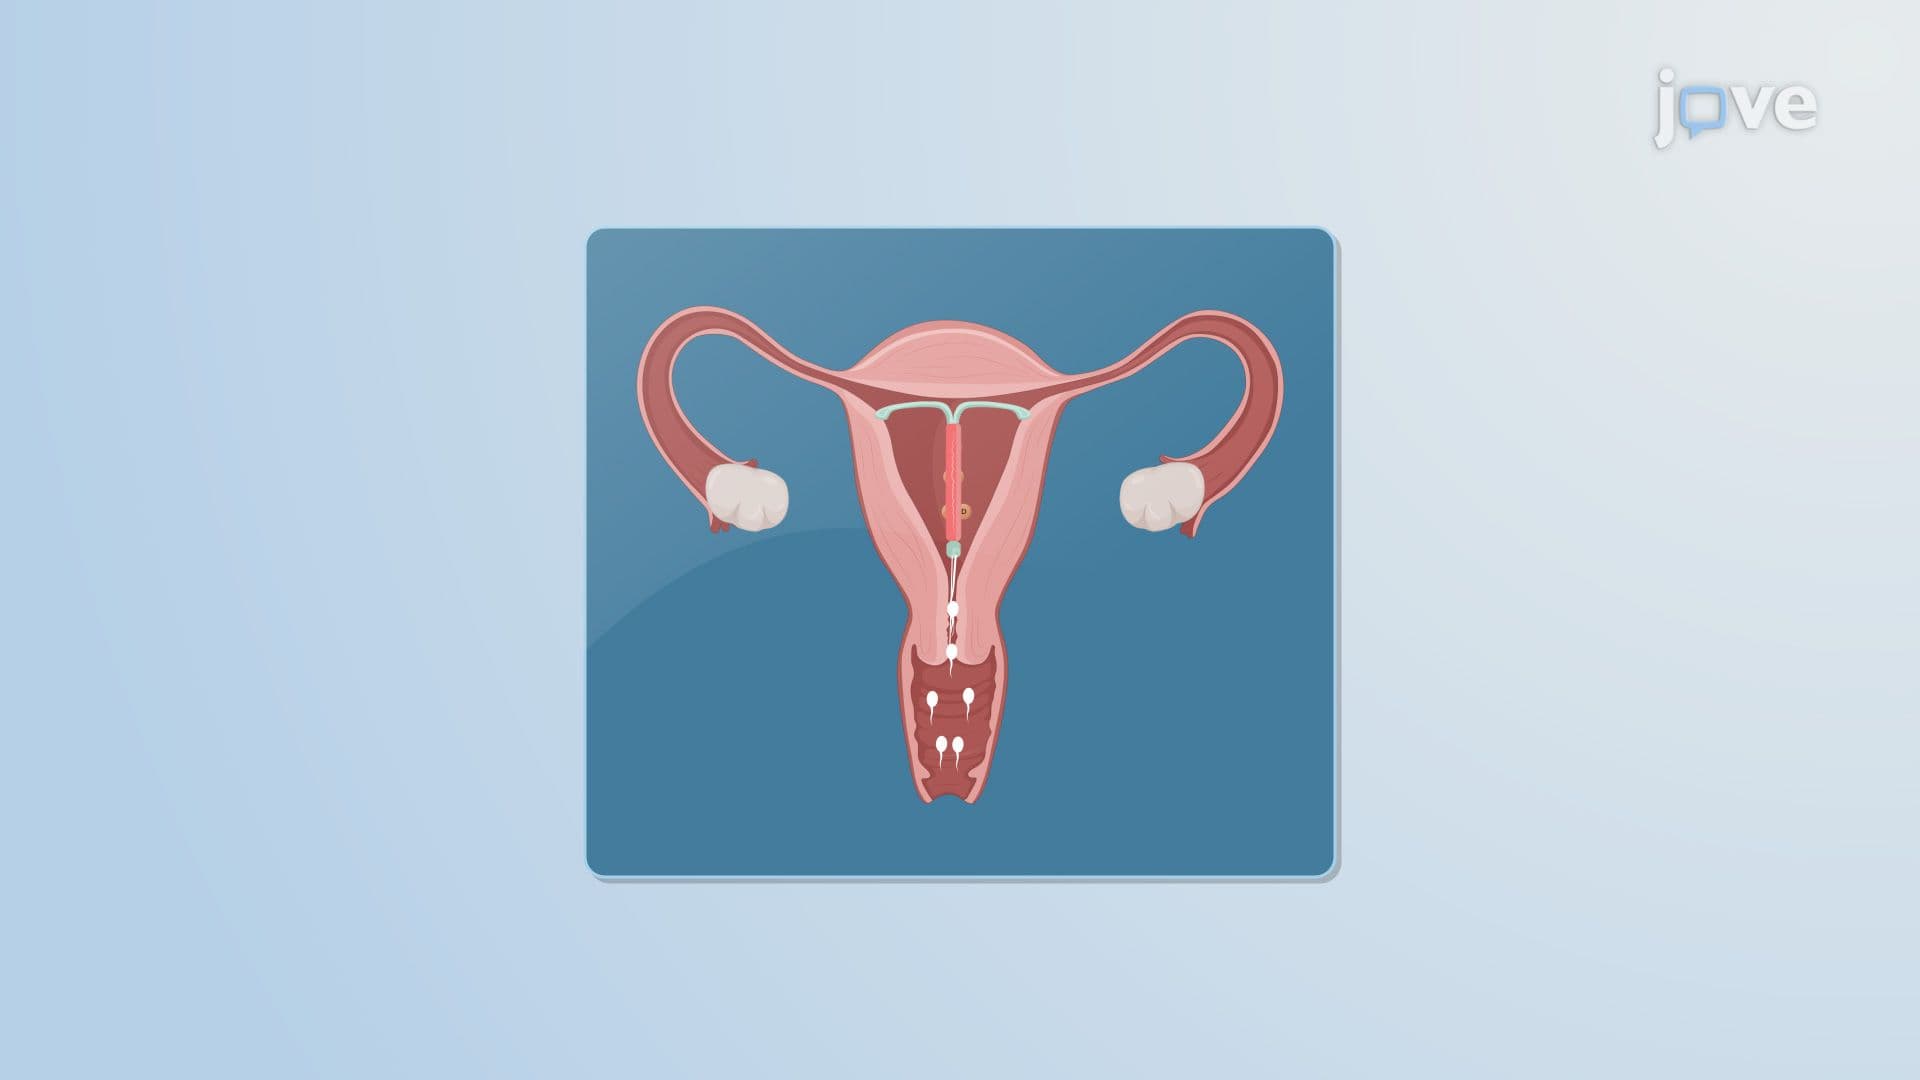
Intrauterine Drug Delivery Systems
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Birth Control Methods
 01:27
Ovarian Cycle
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.