Related Experiment Videos
Critical evaluation of diagnosing bacterial overgrowth in the proximal small intestine
Angèle P M Kerckhoffs1, Maarten R Visser, Melvin Samsom
1Gastrointestinal Research Unit, Department of Gastroenterology, University Medical Center Utrecht, Utrecht, The Netherlands. A.Kerckhoffs@umcutrecht.nl

Background:
Clinical small bowel bacterial overgrowth (SBBO) syndrome can be objectified by bacterial overgrowth tests. As direct culture of jejunal aspirates has disadvantages, noninvasive tests such as breath tests (BTs) are used. Major drawback of lactulose BT might be rapid lactulose transit to the colon. We evaluated diagnosing bacterial overgrowth using experimental and standard BT, and culture and molecular-based methods.
Study:
Bacterial overgrowth was analyzed in 11 controls and 15 SBBO predisposed subjects. During experimental breath testing, an occlusive balloon limited lactulose to the small intestine. Jejunal fluid was analyzed using culture and molecular-based methods. Bacterial overgrowth was diagnosed on the basis of 20 ppm hydrogen or methane increase above baseline within 90 minutes or more than 10 CFU/mL excluding lactobacilli and streptococci and furthermore using all published definitions.
Results:
Experimental and standard BT showed no changes in timing of hydrogen excretion between controls and SBBO subjects. Using standard BT, 3/11 controls and 8/15 SBBO subjects were bacterial overgrowth positive. Total counts showed no significant differences between controls and SBBO subjects using culture and molecular-based methods. Bacterial overgrowth was diagnosed in 0/9 controls and 4/12 SBBO subjects using culture-based methods. Other definitions used in literature revealed no significant differences between controls and SBBO subjects.
Conclusions:
In a small group of subjects, the experimental BT did not improve the ability of lactulose BT to diagnose bacterial overgrowth. Culturing showed less bacterial overgrowth in controls compared with BT. Remarkably, current diagnostic criteria do not seem to be accurate in discriminating between SBBO subjects and controls.
Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:18
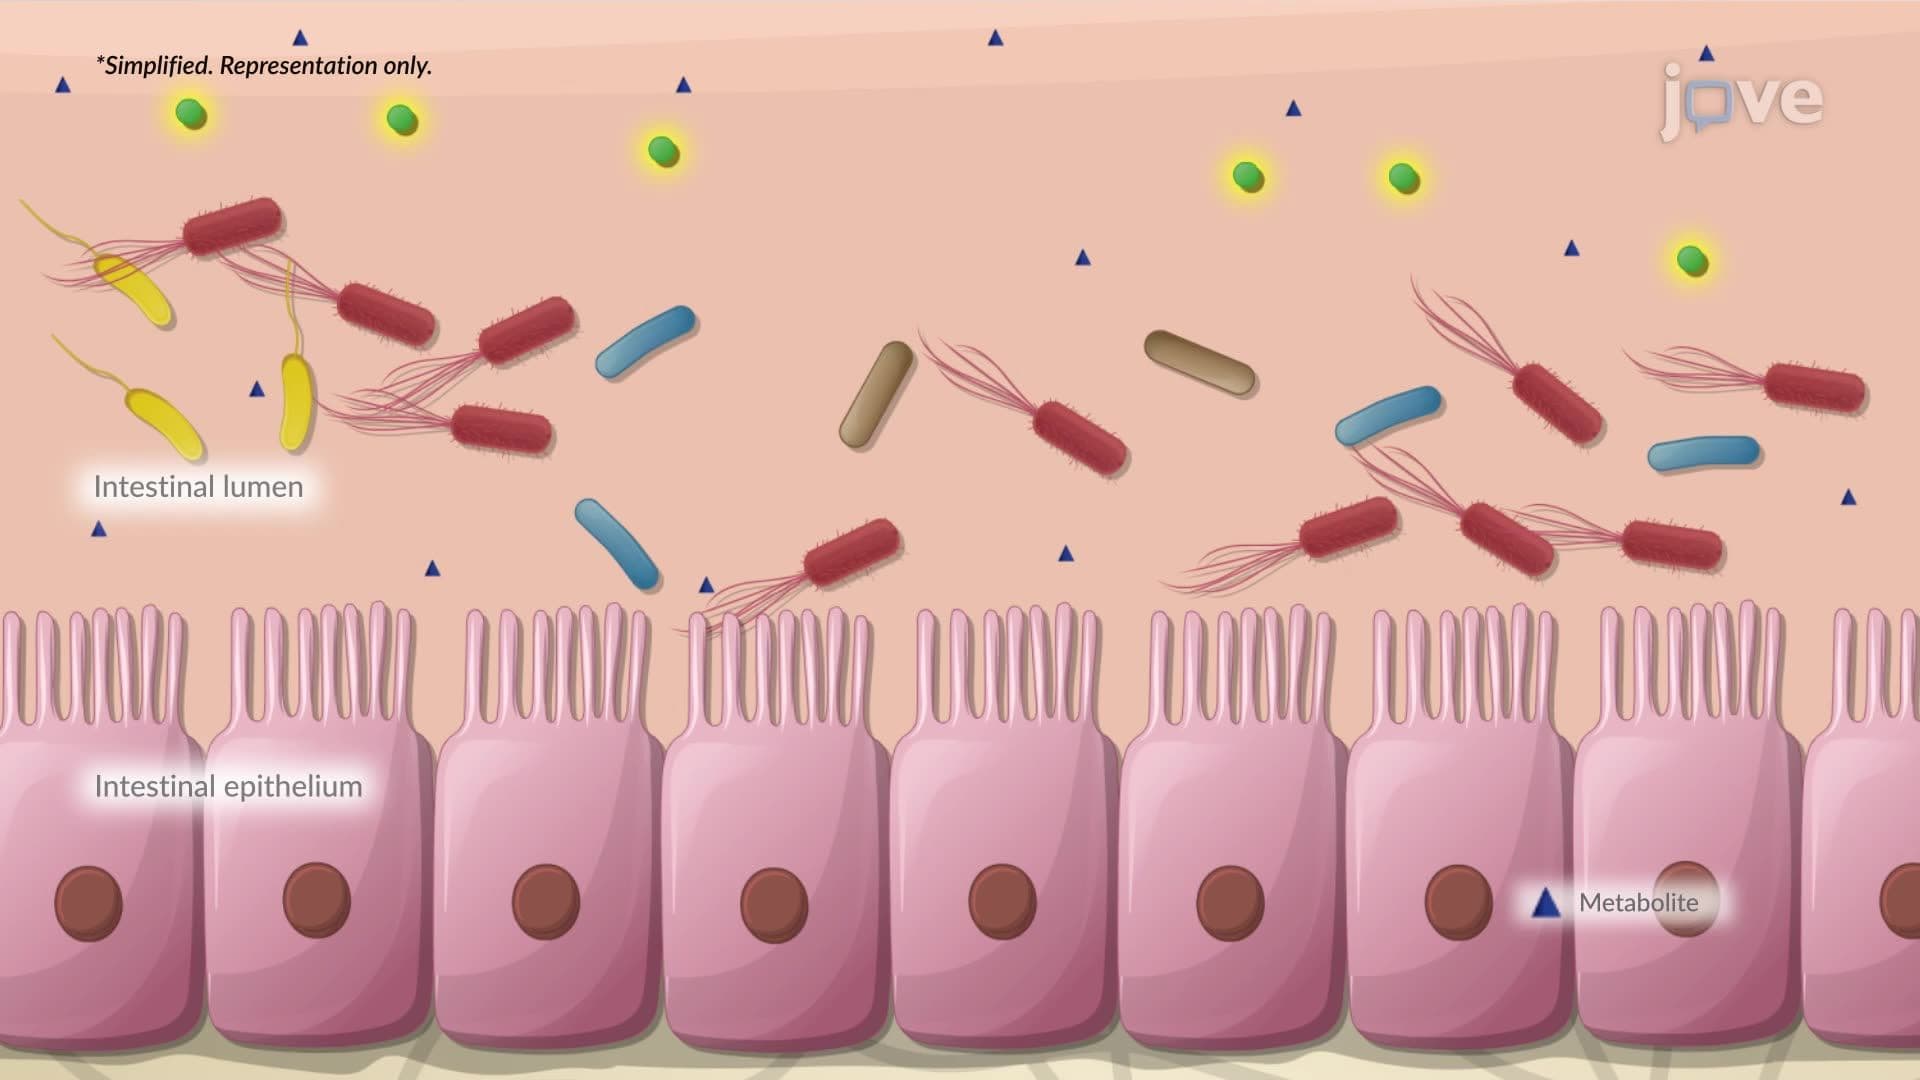
Dysbiosis of the Gut Microbiota
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:27
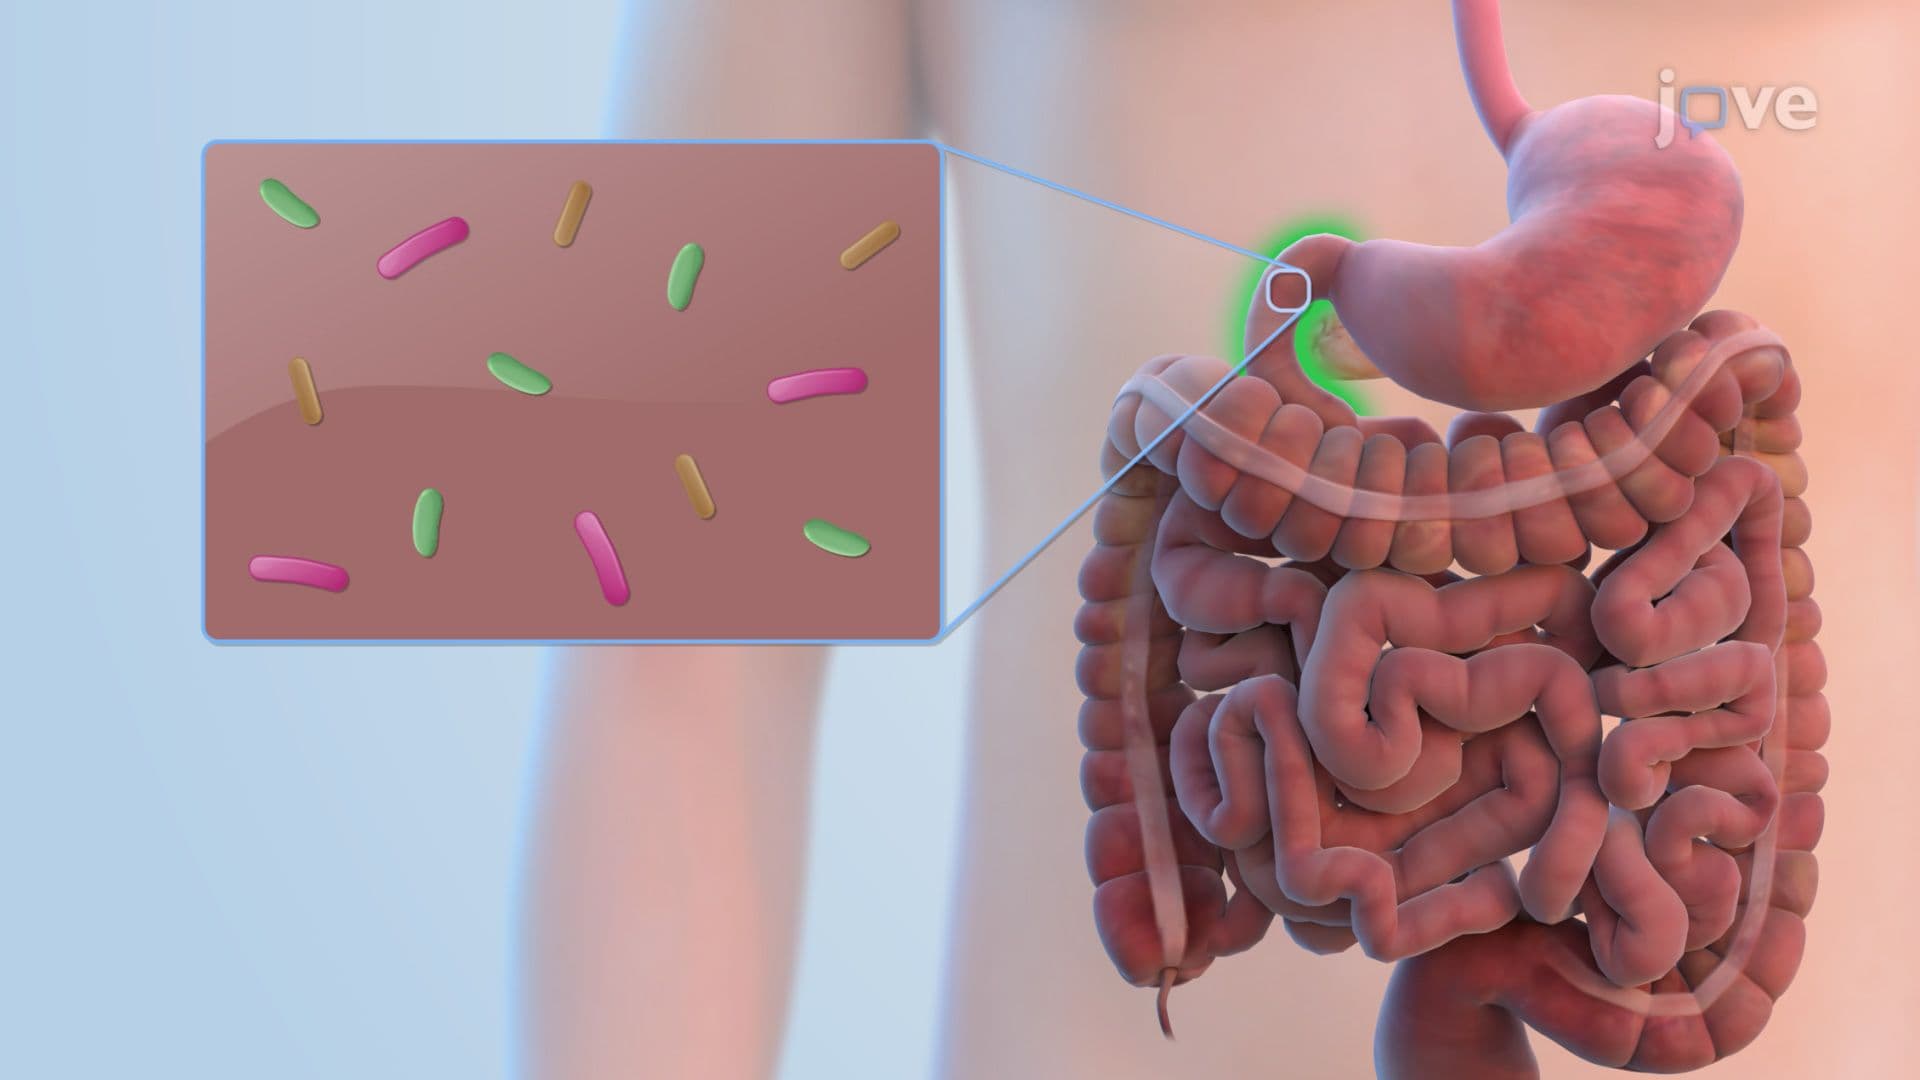
Microbiota of the Stomach and Small Intestine