Related Experiment Video
Updated: Jun 28, 2026
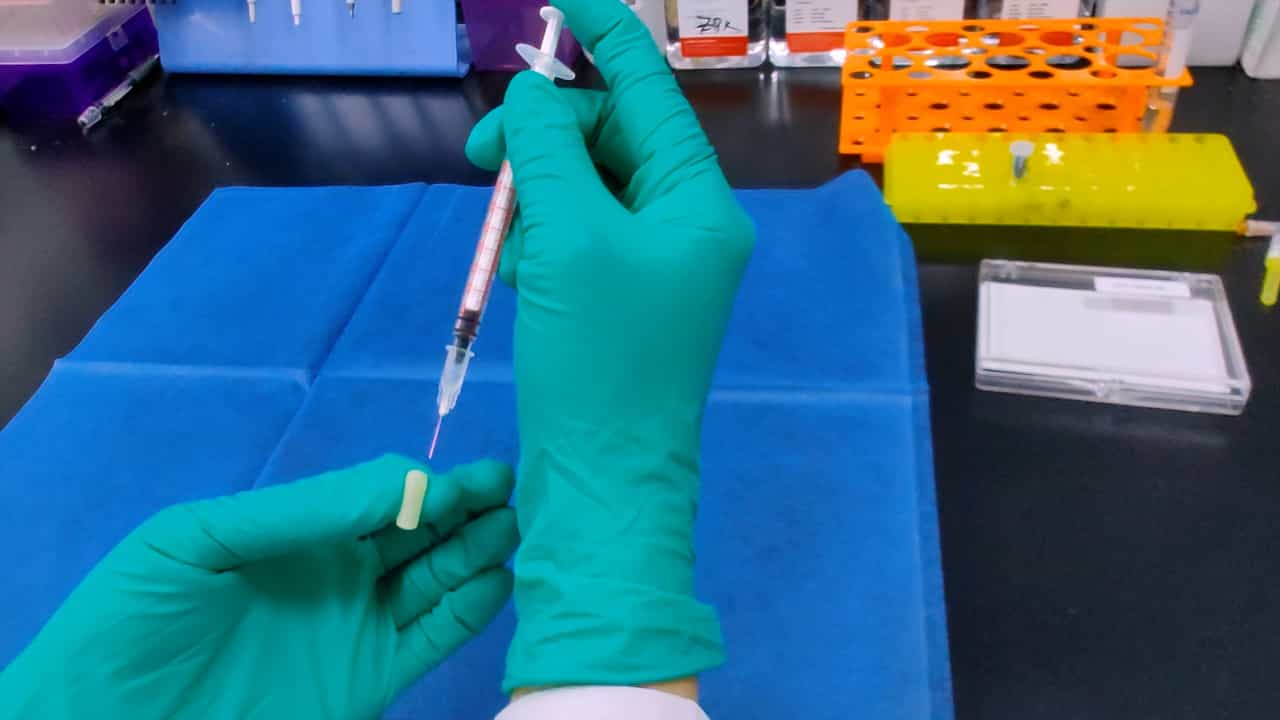
A Modified Technique for Inducing Polycystic Ovary Syndrome in Mice
Published on: July 5, 2024
The effect of atorvastatin in patients with polycystic ovary syndrome: a randomized double-blind placebo-controlled
Thozhukat Sathyapalan1, Eric S Kilpatrick, Anne-Marie Coady
1Department of Diabetes and Endocrinology , University of Hull, Hull HU6 7RX, United Kingdom. tsathyapal@rediffmail.com

Context:
Polycystic ovary syndrome (PCOS) is associated with increased risk of cardiovascular morbidity, whereas statins are proven to reduce cardiovascular mortality and morbidity through lipid-lowering and perhaps through their pleiotropic effects. Statins can also reduce testosterone in vitro by inhibiting ovarian theca-interstitial cell proliferation and steroidogenesis and reducing inflammation in vivo.
Objective:
Our objective was to assess the effect of atorvastatin on inflammatory markers, insulin resistance, and biochemical hyperandrogenemia in patients with PCOS.
Design And Setting:
We conducted a randomized, double-blind, placebo-controlled study at a tertiary care setting in United Kingdom.
Patients:
Patients included 40 medication-naive patients with PCOS and biochemical hyperandrogenemia.
Methods:
Patients were randomized to either atorvastatin 20 mg daily or placebo.
Main Outcome Measures:
The primary endpoint of the study was a change in the inflammatory marker high-sensitivity C-reactive protein. The secondary endpoints were a change in insulin resistance and total testosterone.
Results:
After 12 wk atorvastatin, there was a significant reduction (mean +/- sem) in total cholesterol (4.6 +/- 0.2 vs. 3.4 +/- 0.2 mmol/liter, P < 0.01), low-density lipoprotein cholesterol (2.9 +/- 0.2 vs. 1.8 +/- 0.2 mmol/liter, P < 0.01), triglycerides (1.34 +/- 0.08 vs. 1.08 +/- 0.13 mmol/liter, P <0.01), high-sensitivity C-reactive protein (4.9 +/- 1.4 vs. 3.4 +/- 1.1 mg/liter, P = 0.04), free androgen index (13.4 +/- 0.6 vs. 8.7 +/- 0.4, P < 0.01), testosterone (4.1 +/- 0.2 vs. 2.9 +/- 0.1 nmol/liter, P < 0.01) and insulin resistance as measured by homeostasis model assessment for insulin resistance (HOMA-IR) (3.3 +/- 0.4 vs. 2.7 +/- 0.4). There was a significant increase in SHBG (31.1 +/- 1.0 vs. 35.3 +/- 1.2 nmol/liter, P < 0.01). There was a positive correlation between the reduction in HOMA-IR in the atorvastatin group with the reduction in triglycerides and the reduction of free androgen index. There was a significant deterioration of HOMA-IR in the placebo group (3.0 +/- 0.4 vs. 3.8 +/- 0.5).
Conclusions:
This study suggests that atorvastatin is effective in reducing inflammation, biochemical hyperandrogenemia, and metabolic parameters in patients with PCOS after a 12-wk period.


Related Concept Videos
 01:20
Lipid-Lowering Drugs: Statins and Miscellaneous Agents
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:26
Atherosclerosis III: Management
 02:07
Oogenesis