Related Experiment Video
Updated: Jun 28, 2026
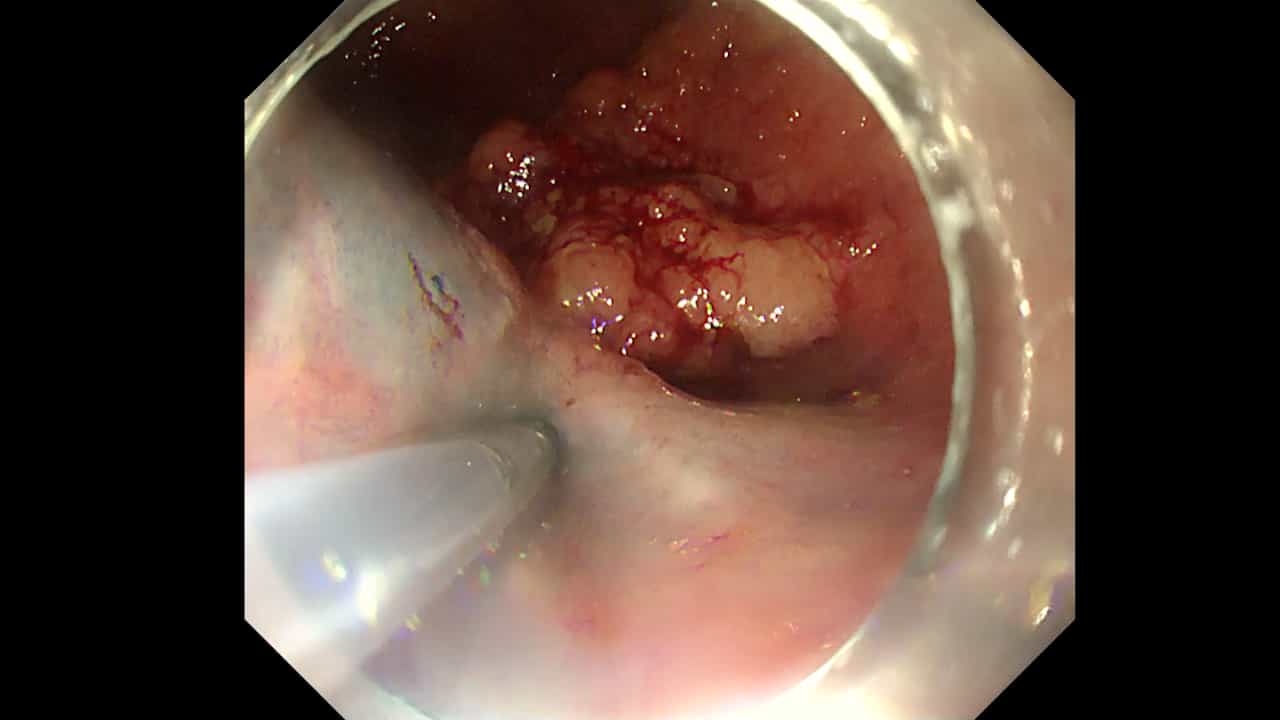
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Changing concepts in the pathogenesis, evaluation, and management of solitary rectal ulcer syndrome
Adrián E Ortega1, Nancy Klipfel, Rebecca Kelso
1Department of Surgery, Keck School of Medicine at the University of Southern California, Los Angeles, California 90033, USA. aortega@surgery.usc.edu

Abstract:
The purpose of this study was to assess the impact of new technology on both the understanding of the underlying pathophysiology and treatment of solitary rectal ulcer syndrome (SRUS). This study is a retrospective review of patients with a histologic diagnosis of SRUS (1993 to 2007) complimented with a prospective database of those patients studied with defecography and dynamic pelvic MRI. Thirty patients were available for evaluation. A polyp or mass was present in 74 per cent. Ulcers were found in only 23 per cent. All 12 patients undergoing defecography demonstrated rectorectal intussusception. Dynamic MRI of the pelvis revealed pronounced anorectal redundancy and lack of mesorectosacral fixation with mild to severe pelvic floor descent in all four patients studied. Fiber with or without stool softeners was the initial treatment in all patients with resolution of symptoms in 65 per cent. One patient with refractory symptoms underwent a stapled transanal rectal resection with complete resolution of symptoms. Occult rectorectal intussusception appears to be the operant anatomic pathology in SRUS. Anorectal redundancy with lack of mesorectosacral fixation may contribute to the process. All patients should be studied with defecography and dynamic MRI. Stapled transanal rectal resection may offer a promising surgical option.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...